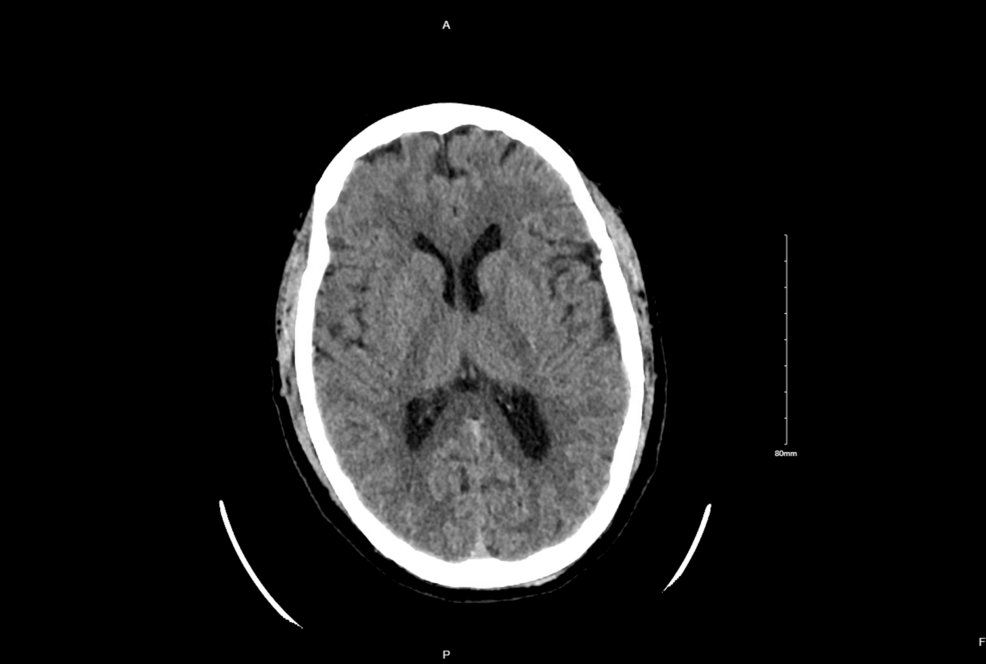
A 43-year-old man’s recent cocaine use initially masked a rare autoimmune condition, leading doctors to attribute his worsening neurological symptoms to substance-induced movement disorders.
The patient, who had experienced years of undiagnosed sleep disturbances, only received a definitive diagnosis of anti-IgLON5 disease after a serum antibody panel returned from the laboratory following his initial hospital discharge, according to a report in Cureus.
Anti-IgLON5 disease, first identified in 2014, occupies a complex medical space between autoimmune and neurodegenerative conditions. While patients carry specific autoantibodies, neuropathological examinations reveal a tauopathy affecting the brainstem and hypothalamus. The disorder’s clinical profile is notoriously heterogeneous, often mimicking multiple system atrophy (MSA) through symptoms like sleep-disordered breathing, autonomic dysfunction, and stridor.
The patient presented with transient left-sided numbness, dysarthria, and choreiform movements. Because he admitted to recent cocaine use, clinicians initially categorized his acute, nonrhythmic limb jerks as a substance-induced issue. However, the patient’s history included three years of progressive sleep problems and several months of nocturnal vocalizations, which are hallmark indicators of the disease.
| Symptom | Percentage of Patients |
|---|---|
| Sleep abnormalities | 76.5% |
| Bulbar dysfunction | 61.4% |
| Movement disorders | 56.1% |
"The patient’s abnormal facial and upper-extremity movements had been present for several months before the reported cocaine exposure," the report noted. While cocaine can exacerbate existing movement disorders, the longitudinal history suggested a deeper, underlying pathology that was not captured by initial toxicology screens.
Following the positive antibody result, the patient underwent lumbar puncture, which confirmed the presence of IgLON5 antibodies in the cerebrospinal fluid at a titer of 1:128. He received a three-day course of intravenous methylprednisolone followed by five days of intravenous immunoglobulin (IVIG).
Within days of starting immunotherapy, the patient reported the most restorative sleep he had experienced in years. His choreiform movements resolved, and family members observed a significant reduction in dream enactment behaviors. By his three-month follow-up, he remained in remission for movement, speech, and cognitive symptoms, although he continued to struggle with insomnia linked to secondary issues like nocturnal urinary urgency.
Despite the successful short-term response to immunotherapy, clinicians remain cautious about long-term outcomes. Because the patient received two different forms of treatment concurrently, it is difficult to isolate the exact efficacy of each intervention. The patient’s initial presentation included neurological deficits—such as transient dysarthria and numbness—that did not recur but remain unexplained by the final diagnosis.
Whether earlier recognition could have prevented the neuroaxonal injury reflected in his elevated serum neurofilament light chain levels remains a subject of ongoing clinical investigation. The specific trigger for his transient neurological event at the time of his first admission also remains unknown.
Keep reading