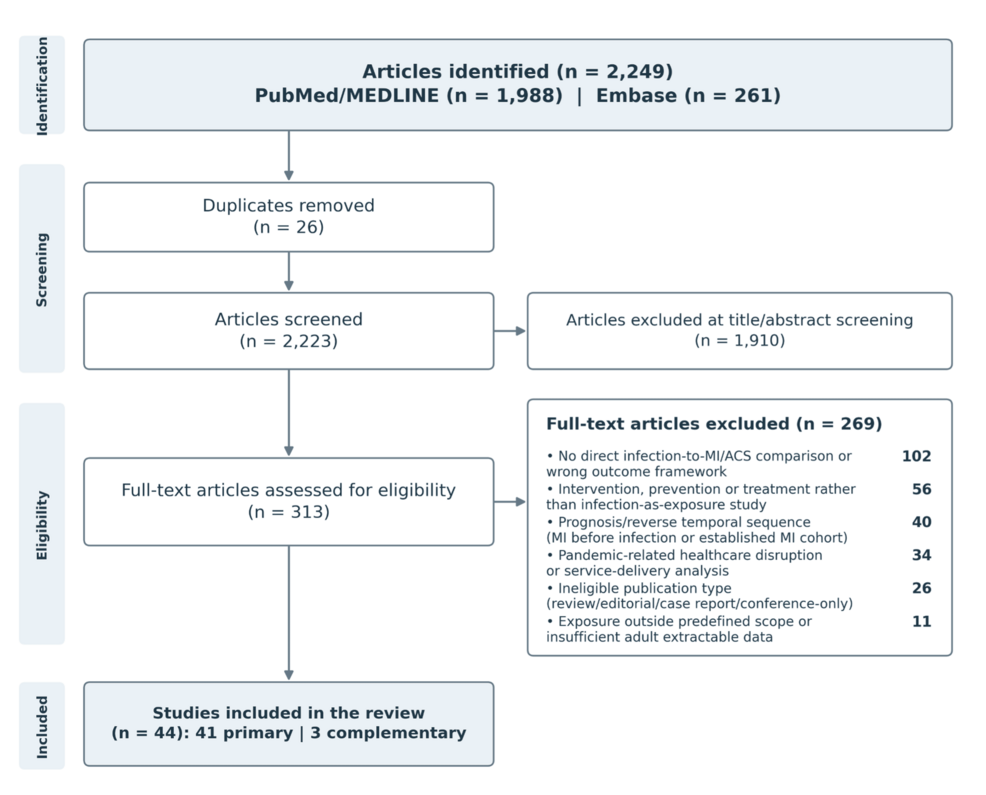
Acute myocardial infarction strikes frequently in the wake of respiratory illnesses, bloodstream infections, and viral pathogens, Cureus reported on October 6, 2026.
Traditional risk factors like smoking, diabetes, and hypertension fail to explain the exact timing of these sudden coronary events.
Infection induces systemic inflammation, hemodynamic stress, and prothrombotic responses that destabilize underlying coronary plaques. Type 1 myocardial infarction involves acute atherothrombosis, while type 2 events stem from an oxygen supply and demand mismatch. Elevated troponin levels during an active infection alone remain insufficient to confirm a myocardial infarction diagnosis without explicit evidence of ischemia.
Influenza and acute respiratory infections trigger sharp spikes in myocardial infarction incidence within the first week following illness. Kwong et al. documented an incidence ratio of 6.05 during the initial seven days after specimen collection, while de Boer et al. observed an adjusted relative incidence of 6.16 over the same early risk window.
Studies evaluating SARS-CoV-2 reveal a similar early surge in coronary events. Katsoularis et al. reported a first-week incidence rate ratio of 2.89 for myocardial infarction after excluding day-zero diagnoses. Suzuki et al. identified an incidence rate ratio of 6.65 during the first week of the Omicron wave in Japan.
| Pathogen Exposure | Risk Window | Reported Estimate |
|---|---|---|
| Influenza | Days 1 to 7 | IR 6.05 (Kwong et al.) |
| Bloodstream Infection | Days 1 to 7 | IRR 9.67 (Underwood et al.) |
| COVID-19 | First week (excl. day 0) | IRR 2.89 (Katsoularis et al.) |
Bacterial infections drive acute coronary risks in the days immediately following detection. Underwood et al. found an adjusted incidence rate ratio of 9.67 during the first week after a community-associated bloodstream infection. Pedersen et al. tracked hospitalized adults and recorded a 3.39 hazard ratio for myocardial infarction following pneumonia.
Longer-term cohorts evaluate chronic conditions like HIV and tuberculosis across multi-year follow-up periods. Freiberg et al. calculated an adjusted hazard ratio of 1.48 for myocardial infarction among participants in the Veterans Aging Cohort Study with HIV. Lee et al. reported an adjusted hazard ratio of 1.48 among tuberculosis survivors during a median follow-up of 3.9 years.
Differentiating between type 1 and type 2 myocardial infarction during acute illness requires careful clinical correlation. Persistent inflammation and immune history complicate long-term cardiovascular outcomes in chronic infection cohorts. Observational findings cannot establish that routine prophylactic treatments prevent infection-triggered events.
Cureus, founded in 2009 as PeerEMed and renamed in December 2012, publishes articles after rapid pre-publication peer review followed by an optional post-publication SIQ scoring system. The journal joined Springer Nature in December 2022 and was removed from the Web of Science in October 2025.
Randomized trials provide clearer insights into secondary prevention strategies. Fröbert et al. randomized participants in the IAMI trial to influenza vaccination or placebo following myocardial infarction.
Related reading
- Empower Pacific Urges Early Childhood Focus for Men’s Mental Health
- Doctors Name Omega-3, D3, K2, Magnesium for Healthy Aging
- Beer and Spirits Linked to Higher Risk of Acute Kidney Injury, Study Finds (archyde.com)
- Per Fly to Set ‘Peer Gynt’ in Arms-Dealing World for Nordic Co-Production, VG Reports (archynewsy.com)