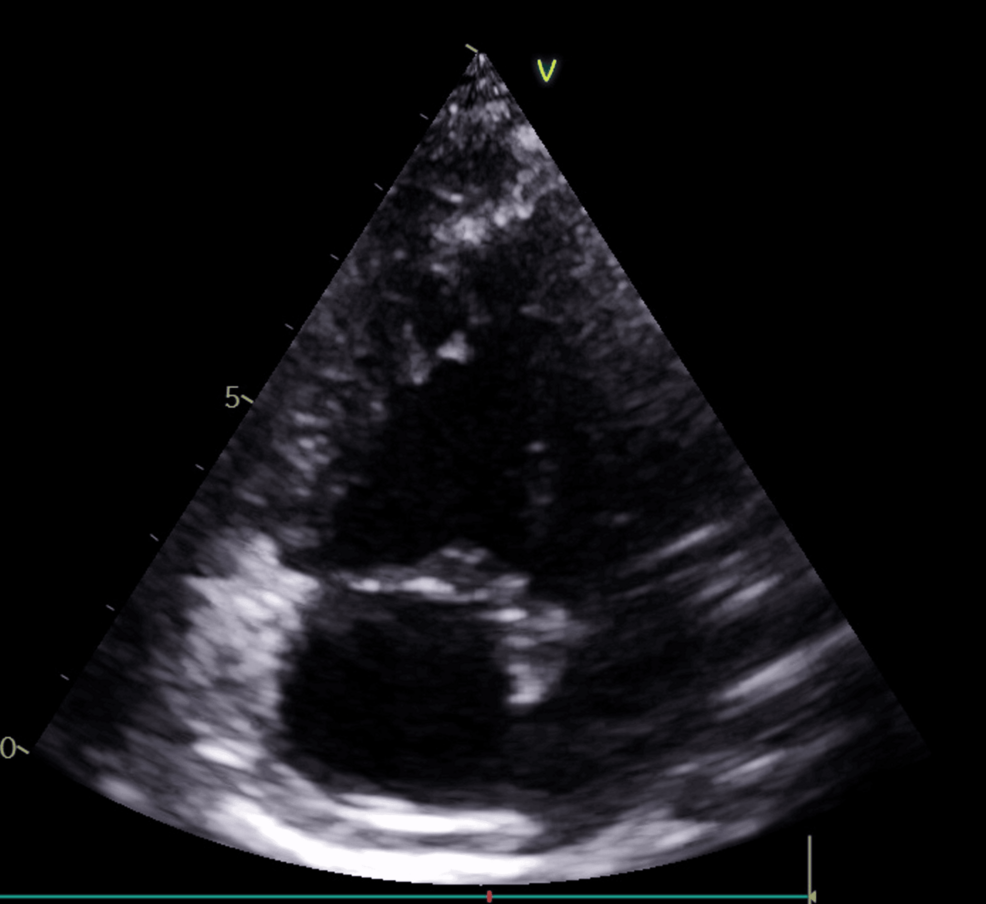
A 2-year-old girl born to first-cousin parents was diagnosed with Keutel syndrome after recurrent wheezing led doctors to find widespread cartilage calcification in her windpipe and bronchial tubes, Cureus reported.
The case, published in the peer-reviewed medical journal, adds to fewer than 50 documented instances worldwide of the autosomal recessive disorder caused by mutations in the matrix Gla protein (MGP) gene. The child, 2 years and 7 months old at admission, had a history that included an ischemic stroke at 7 months, acute pyelonephritis at 1 year, and recurrent ear infections. She had been treated for presumed asthma since age 1.
Dysmorphic features and severe pulmonary hypertension redirect diagnosis
Clinical examination revealed coarse facial features, hypertelorism, a broad nasal root, and midfacial hypoplasia. The child was in respiratory distress with intercostal retractions and bilateral wheezing. Oxygen saturation was 95% on room air.
A chest X-ray showed millimeter-sized calcified opacities along the tracheal wall, right main bronchus, and right lower lobe bronchus.
Echocardiography uncovered a dilated, hypertrophied right ventricle with preserved function and severe pulmonary hypertension estimated at 110 mmHg. It also showed hypoplasia of the left pulmonary artery and peripheral stenoses of the bilateral pulmonary arteries.
CT angiography confirms extensive tracheobronchial and vertebral calcification
Thoracic CT angiography confirmed extensive tracheobronchial calcifications and revealed a reduction in the height of the posterior wall of the thoracic vertebral bodies, predominantly at T9 and T10, with punctate calcifications of the vertebral endplates. Cardiac catheterization demonstrated multiple lobar and sublobar stenoses of both pulmonary arteries complicated by precapillary pulmonary hypertension with systemic-level pressures. Audiometry confirmed right-sided hearing loss and left-sided hypoacusis.
Genetic mechanism: loss of calcification inhibitor
Keutel syndrome results from homozygous mutations in the MGP gene at locus 12p13.1-p12.3. Matrix Gla protein is a vitamin K-dependent extracellular matrix protein produced by smooth muscle cells and chondrocytes. It inhibits tissue calcification by repressing bone morphogenetic protein 2 (BMP2).
Loss of MGP function leads to inappropriate mineralization of cartilage and soft tissues, particularly in the airways, ears, nose, and pulmonary arteries.
Laboratory tests in the patient, including calcium, phosphate, and parathyroid hormone levels, were normal. An immunodeficiency workup — HIV serology, immunoglobulin levels, and lymphocyte subpopulations — also returned normal results.
Symptomatic management yields rapid improvement; vitamin K ineffective
Emergency treatment for acute asthma exacerbation with inhaled beta-2 agonists and oral corticosteroids led to rapid clinical improvement. However, the recurrent episodes insufficiently controlled by standard asthma therapy pointed to a cardiogenic component driven by vascular stenoses and airway calcification.
The report notes that vitamin K supplementation has not demonstrated efficacy because the defect lies in the protein itself rather than in vitamin K availability. Management remains symptomatic and multidisciplinary, encompassing bronchodilators, antihypertensives, antibiotics, and surgical interventions such as angiographic dilation or endoscopic treatment for tracheal stenosis. A right cochlear implant was considered for the patient. Long-term follow-up is planned.
Family screening and genetic counseling urged in consanguineous families
Forty-two cases have been reported to date, with approximately half occurring in the Turkish population. The disorder is estimated to affect 1 in 1 million individuals. The authors emphasize that early diagnosis is essential to optimize management and prevent complications. Family screening and genetic counseling are strongly recommended, especially in cases of consanguinity.
FAQ: Keutel syndrome
What causes Keutel syndrome?
Keutel syndrome is caused by homozygous mutations in the MGP gene, which encodes matrix Gla protein, a vitamin K-dependent inhibitor of tissue calcification. Loss of this protein leads to abnormal calcification of cartilage and soft tissues.
What are the hallmark clinical features?
Classic features include brachytelephalangy (shortening of the fingertips), sensorineural hearing loss, peripheral pulmonary artery stenosis, and abnormal calcifications of the tracheobronchial tree, ears, nose, and ribs. Facial dysmorphism such as midfacial hypoplasia and a broad nasal root is common.
Is vitamin K supplementation effective?
No. The defect is structural — the MGP protein itself is nonfunctional — so providing more vitamin K cofactor does not restore inhibitory activity.
How is the diagnosis confirmed?
Diagnosis is suspected on clinical and radiological grounds — tracheobronchial calcifications on imaging, brachytelephalangy on hand X-ray, pulmonary artery stenosis on echocardiography — and confirmed by genetic testing identifying MGP mutations.
What is the prognosis?
The overall prognosis is generally favorable, but cardiac and respiratory complications — including pulmonary stenosis, recurrent infections, and hypoventilation — can be life-threatening. Early multidisciplinary management improves outcomes.
Keep reading