Diagnosis and Treatment of Streptococcus agalactiae Endogenous Endophthalmitis
An 82-year-old man with diabetes mellitus and a bladder tumor under evaluation developed sudden blurred vision and severe pain in his left eye, ultimately leading to a diagnosis of endogenous endophthalmitis caused by Streptococcus agalactiae, as documented in a case study published in Cureus. Initially treated for suspected uveitis at a referring hospital with topical steroids and levofloxacin, the patient experienced the appearance of hypopyon the following day. Clinicians administered intravitreal vancomycin 1.0 mg and ceftazidime 2.0 mg before transferring him for advanced surgical management.
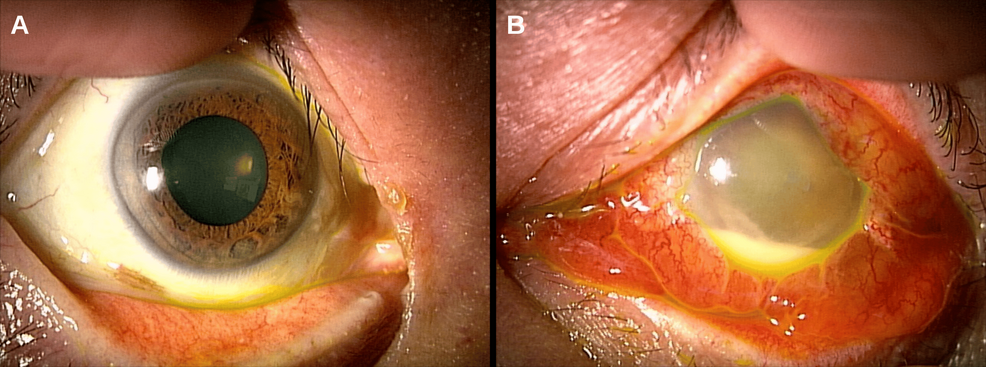
Upon presentation, the patient’s visual acuity in the affected eye had dropped to light perception, and intraocular pressure spiked to 48 mmHg. Examination revealed marked corneal opacity, hypopyon, and mild vitreous opacity on B-scan ultrasonography. Despite lacking systemic symptoms or urinary complaints initially, laboratory results indicated a pronounced systemic inflammatory response, with a white blood cell count of 12,600/µL, a C-reactive protein level of 7.75 mg/dL, and procalcitonin at 1.05 ng/mL. Shivering developed roughly 12 hours after admission.
Streptococcus agalactiae grows in aqueous humor and urine samples
Emergency lens extraction and pars plana vitrectomy were performed on day zero. Aqueous humor smears revealed phagocytosed chain-forming cocci, and cultures grew Streptococcus agalactiae. Conversely, an undiluted vitreous specimen collected about 24 hours after the prior intravitreal injection came back smear- and culture-negative. Midstream urine samples also grew Streptococcus agalactiae at concentrations exceeding 10⁵ CFU/mL alongside significant pyuria. Antimicrobial susceptibility testing across 11 agents showed that both the aqueous humor and urine isolates shared identical resistance and susceptibility profiles, exhibiting susceptibility to penicillin G, cefotaxime, ceftriaxone, imipenem/cilastatin, chloramphenicol, and trimethoprim-sulfamethoxazole, while showing resistance to clarithromycin, clindamycin, levofloxacin, tosufloxacin, and minocycline.
Pro Tip: When evaluating patients presenting with acute endogenous endophthalmitis and high intraocular pressure, clinicians should obtain blood cultures before initiating antimicrobial therapy to capture transient bacteremia windows, as noted in the Cureus findings.
Whole-body computed tomography revealed a rim-enhancing preseptal fluid collection near the left globe, a bladder tumor, bladder wall enhancement, benign prostatic hyperplasia, and focal areas of reduced parenchymal enhancement in the right kidney. Transthoracic and transesophageal echocardiograms showed no evidence of infective endocarditis. Because blood cultures were not obtained at the initial presentation, definitive proof of bacteremia remained unconfirmed, leaving the urinary tract as a presumed rather than proven source of hematogenous seeding.
Surgical Management and Clinical Outcomes
The patient underwent a comprehensive treatment regimen totaling 46 days of systemic antimicrobial therapy, concluding with oral amoxicillin. Because the lens, lens capsule, and vitreous were removed during the initial vitrectomy, the anterior chamber and vitreous cavity formed a single continuous space. To address persistent intraocular inflammation, clinicians administered two separate intracameral injections of vancomycin 1.0 mg and ceftazidime 2.0 mg on days three and seven via limbal paracentesis.
Two months post-treatment, the eye was free of pain and inflammation, but the retina remained detached under silicone oil, and visual acuity dropped to no light perception. A separate report published on PMC highlights a similar severe presentation of Streptococcus agalactiae endogenous endophthalmitis in a 37-year-old man who ultimately required evisceration and debridement surgery after presenting with a high fever, 61 mmHg intraocular pressure, and extensive corneal opacities with keratolysis.
Infectious agents cross the blood-ocular barrier from systemic sites
What is endogenous endophthalmitis?
Endogenous endophthalmitis occurs when circulating bacteria or fungi cross the blood-ocular barrier from a primary systemic infection elsewhere in the body, most commonly seeding the choroid before spreading into the vitreous and anterior chambers. It represents a small fraction of all endophthalmitis cases but carries a particularly poor visual prognosis.
Why was the vitreous culture negative in this patient?
The negative vitreous smear and culture were primarily attributed to the intravitreal antibiotics administered at the referring hospital approximately 24 hours prior to sample collection. In contrast, the aqueous humor remained culture-positive despite high intraocular antibiotic exposure.
Can urinary tract infections cause eye infections without urinary symptoms?
Yes, older adults frequently present with bacteremic urinary tract infections that lack localized urinary or systemic symptoms. In this patient, significant pyuria and high bacterial counts in the urine pointed toward the urinary tract as the likely source of dissemination, even in the absence of dysuria or fever.
What was the final visual outcome for the patient?
Although the infection was successfully controlled after a 46-day course of systemic and localized antimicrobials, an iatrogenic retinal break led to permanent retinal detachment. At the two-month follow-up, the patient had no pain or inflammation, but visual acuity was recorded as no light perception.
Keep reading