Two-Step Triage Pathway Shortens Wait Times for MASLD Care
A new triage model for metabolic dysfunction-associated steatotic liver disease (MASLD) has reduced the time from referral to specialist consultation by more than half, according to research presented at The Liver Meeting 2026. Data from the quasi-experimental study shows the pathway effectively filters low-risk patients, allowing hepatologists to prioritize those with advanced fibrosis.
Implementation of the Biomarker-Based Screening Model
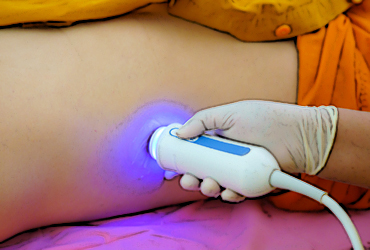
The triage strategy relies on a two-step process to determine which patients require a specialist. First, clinicians calculate an age-adjusted Fibrosis-4 (FIB-4) index. Patients under 65 are classified as low risk if their score is below 1.3, while those 65 and older are considered low risk if their score is below 2.0. If these scores indicate potential risk, the pathway triggers a second step involving transient elastography (TE) to confirm the presence of advanced fibrosis.
Dr. Giada Sebastiani of McGill University, who presented the findings, noted that the model prevents unnecessary hepatology referrals for patients who do not demonstrate clinical markers for advanced disease.
Impact on Clinical Workflow and Patient Access
The study analyzed 3,953 patient referrals between 2013 and 2025. Following the implementation of the two-step pathway, the mean time from referral to transient elastography dropped from 13.2 months to 5.5 months. Hepatology consultation wait times saw a similar decline, falling from 30 months to 13.2 months.
Efficiency gains extended beyond wait times. The proportion of patients managed without an in-person specialist visit increased from 45% to 80%, while the rate of patients failing to show up for scheduled hepatology appointments dropped from 23% to 15%. Despite the faster throughput, the detection of advanced fibrosis within 12 months of referral increased from 10% to 20%.
Clinical Management of MASLD in Primary Care
The research suggests that the majority of MASLD cases can be safely managed by primary care providers while patients await further assessment. Dr. Sebastiani emphasized that care should not be delayed during the waiting period for imaging or specialist input. Primary care teams can address cardiometabolic risk factors—including obesity, type 2 diabetes, dyslipidemia, and hypertension—through lifestyle interventions and weight management.
She advised that clinicians should initiate fibrosis risk stratification in patients with metabolic risk factors rather than waiting for abnormal liver enzymes to appear in blood work.
Screen Patients with Metabolic Risk Factors Early
Who should be screened for MASLD using this pathway?
The research focuses on patients with metabolic risk factors, specifically those with obesity or type 2 diabetes. Clinicians are encouraged to assess fibrosis risk in these populations early, rather than waiting for signs of liver enzyme elevation.
Does this pathway replace the need for hepatology consultations?
No, the pathway is designed to ensure the right patients are seen at the right time. By using blood-based tests and transient elastography, the system reserves specialist capacity for those at the highest risk of advanced disease, while keeping low-risk patients in primary care.
What is the primary barrier to MASLD care mentioned in the study?
The study identifies the growing burden of MASLD combined with limited access to fibrosis testing and specialist consultation as the primary obstacles to timely intervention.
Keep reading