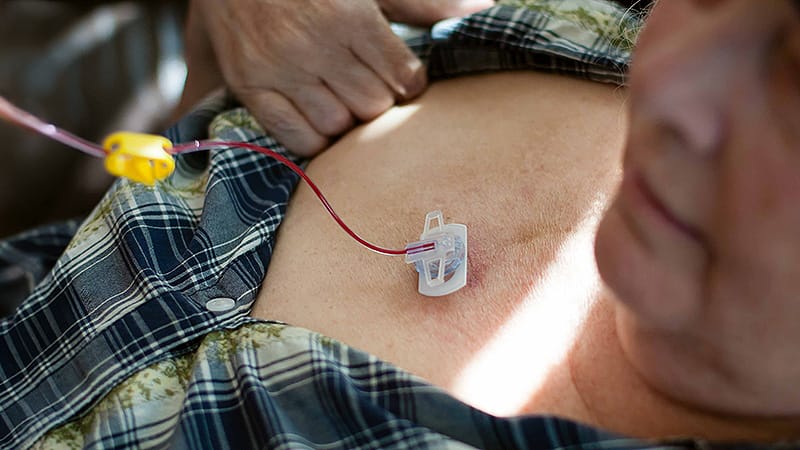
Chlorhexidine-coated central venous catheters can trigger anaphylaxis during surgery even when clinicians actively avoid the antiseptic, based on case reports presented at the American College of Allergy, Asthma, and Immunology 2026 Annual Meeting.
A 39-year-old woman undergoing surgery for an abdominal aortic aneurysm developed hypotension, hypoxemia, bronchospasm, and cardiac arrest within two minutes of a central venous catheter being placed.
Diagnostic testing confirmed chlorhexidine allergy after the patient received cardiopulmonary resuscitation and epinephrine. During a rescheduled surgery, clinicians used povidone-iodine for skin preparation and avoided chlorhexidine entirely, but hypotension, hypoxemia, and bronchospasm recurred immediately after placement of the central venous catheter.
The surgical team failed to recognize that the device itself contained a chlorhexidine coating, according to the report. The patient ultimately stabilized with epinephrine, corticosteroids, and antihistamines.
“Our findings suggest the need for awareness of chlorhexidine coating in medical devices,” said Nawshin Jamil, DO, of Lowell General Hospital in Lowell, Massachusetts, and colleagues, in their Abstract: Perioperative Anaphylactic Shock Due to Chlorhexidine.
Compounded Weight-Loss Drugs Cause Allergies
Patients tolerating one GLP-1 receptor agonist can still develop severe hypersensitivity reactions when switching to another, according to a case described by Victoria Hough, of the Mayo Clinic in Jacksonville, Florida, and colleagues in Abstract: Severe Tirzepatide-Associated Delayed Hypersensitivity in a Semaglutide-Tolerant Patient. A 38-year-old woman with obesity changed medications after a year because her weight loss had plateaued, but she experienced recurrent reactions to compounded tirzepatide, including injection-site urticaria.
A rechallenge with the drug caused escalating reactions over eight days. The patient developed progressive injection-site urticaria requiring emergency department treatment with intravenous corticosteroids, lip and periorbital angioedema requiring epinephrine, and facial and hand angioedema with voice changes and generalized urticaria requiring self-administered epinephrine.
High-dose corticosteroids utilizing a 6-week taper, combined with histamine-1 and histamine-2 receptor blockers, were administered by medical staff, leading to the resolution of symptoms inside of three days. The investigators pointed out that a patient’s earlier tolerance of a specific GLP-1 receptor agonist offers no guarantee against severe adverse reactions when transitioning to a different agent within the class, advising physicians to refrain from premature class-wide allergy labeling.
“Tirzepatide, excipients, or compounded formulation differences remain possible contributors,” Hough and her co-authors noted.
Menopause Disrupts Bee Sting Protection
Data detailed in Abstract: Menopause-Associated Loss of Honeybee Venom Immunotherapy Tolerance: A Case for Hormonal Mast Cell Modulation and co-authored by Houston’s David Engler, MD, for presentation at the ACAAI gathering, indicate that menopausal changes can trigger the breakdown of previously established tolerance to allergen immunotherapy. A 51-year-old woman who successfully maintained honeybee venom immunotherapy for several years developed anaphylaxis with maintenance injections following the onset of menopause.
Subsequent attempts to continue venom immunotherapy with the addition of high-dose antihistamine therapy failed. The patient experienced three episodes of grade 4 anaphylaxe accompanied by a complete loss of consciousness during each event.
Each episode required treatment with epinephrine, and clinicians eventually discontinued the venom immunotherapy. Hormonal modulation of immune responses might explain this sudden shift in patient tolerance.
“Postmenopausal status may alter mast cell activation thresholds, providing a biologically plausible mechanism,” the authors stated.
Common Questions About Perioperative and Drug Allergies
Why did the surgical patient react twice if doctors changed antiseptics?
While clinicians switched to povidone-iodine for skin preparation during the second operation, the surgical team did not realize that the central venous catheter itself featured a chlorhexidine coating.
What specific treatments resolved the severe reaction to tirzepatide?
Medical staff administered high-dose corticosteroids paired with a 6-week taper, alongside histamine-1 and histamine-2 receptor blockers, which cleared the patient’s symptoms within three days.
Mayo Clinic is a nonprofit academic medical center with three major campuses in Rochester, Minnesota; Jacksonville, Florida; and Phoenix/Scottsdale, Arizona. It originated from a sole proprietorship opened by William Worrall Mayo in Rochester in 1864, which evolved under his sons and partners into a multispecialty group practice. The institution employs over 7,300 physicians and scientists and spends more than $1 billion annually on research.
How severe were the postmenopausal reactions to honeybee venom immunotherapy?
“Prior tolerance to one GLP-1 receptor agonist does not preclude severe reactions to another,” Hough and her co-authors noted.
Worth a look