A new retrospective hospital study reveals that patients undergoing breast-conserving surgery for pure ductal carcinoma in situ face significantly higher rates of residual disease and second re-excision procedures compared to those with invasive breast cancer, Cureus reported.
Evaluating Residual Disease Rates After Breast-Conserving Surgery
Breast-conserving surgery remains a primary treatment option for early-stage breast malignancies. However, incomplete tumor removal requires subsequent operations to achieve clear margins. A university teaching hospital analyzed 1,779 patients who underwent breast-conserving procedures between July 2013 and November 2018 to track these outcomes.
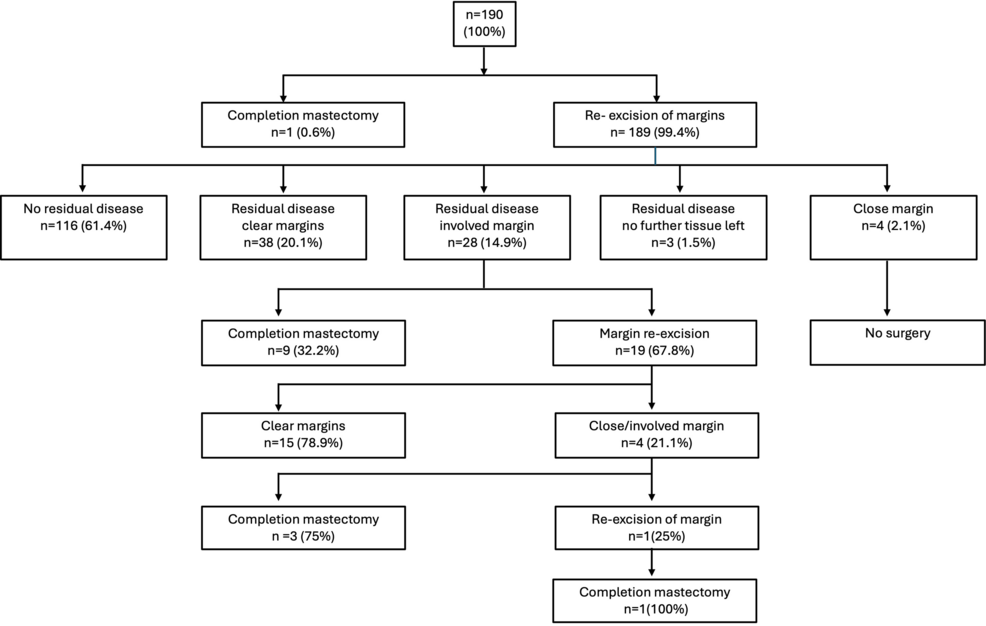
Out of that total cohort, 190 patients presented with involved or close margins. Subsequent re-excision procedures identified residual disease in 38.6% of those cases. The rate climbed sharply when researchers separated the diagnoses.
Pure ductal carcinoma in situ yielded residual disease in 73.5% of re-excised specimens. Invasive cancer cases showed residual disease in only 26.4% of specimens. That difference registered as statistically significant in the data.
Ductal Carcinoma Tumors Measure Larger than Invasive Tumors
The median tumor size for ductal carcinoma in situ patients in this cohort measured 36 millimeters, while invasive tumors had a median size of 21 millimeters.
Persistent Positive Margins Force Additional Surgeries and Mastectomies
Positive margins after a first re-excision forced additional surgical decisions for dozens of patients in the study. Out of 189 patients who underwent initial margin re-excision, 32 individuals required a second procedure due to remaining positive margins.
Patients with pure ductal carcinoma in situ required second re-excisions more frequently than those with invasive carcinoma. To clear margins or manage persistent disease, 14 patients across the entire 190-person study ultimately underwent completion mastectomies, bringing the overall mastectomy rate to 7.3%.
Adjuvant treatments followed standard UK guidelines. Whole breast or chest wall radiotherapy was administered to 88.4% of the cohort, while 87.9% of invasive cancer patients received hormone therapy.
Nipple-Directed Margins Test Positive Frequently in Carcinoma Cases
Radial margin involvement oriented toward the nipple emerged as a critical factor in repeat surgeries. Across the entire study group, the radial margin toward the nipple tested positive for malignancy in 63.2% of patients.
For patients with pure ductal carcinoma in situ, the incidence of a positive margin toward the nipple reached 77.5%. Invasive carcinoma cases showed nipple-directed margin positivity in 58.2% of patients.
Measuring Long-Term Recurrence Rates Across Patient Groups
Over a median follow-up period of 47 months, researchers recorded 13 total recurrences among the 190 patients. Seven patients experienced local recurrence, one suffered a regional recurrence, and five developed distant metastases.
Local recurrence rates varied starkly between diagnoses. Patients with pure ductal carcinoma in situ faced a 10.2% local recurrence rate, compared to 1.4% for those with invasive cancer.
Frequently Asked Questions About Breast-Conserving Surgery Margins
What defines a positive versus a close surgical margin?
Margin involvement is defined as the presence of in situ or invasive carcinoma directly at the inked edge of the resected tissue. Margins are classified as close when tumor cells are present within 1 millimetre of the resection edge, according to Association of Breast Surgery guidelines in the UK.
What was the overall local recurrence rate found in the study?
During the 47-month median follow-up, 3.7% of the total cohort experienced local recurrence. The rate was significantly higher among patients with pure ductal carcinoma in situ at 10.2%, versus 1.4% for invasive cancer patients.
Related reading