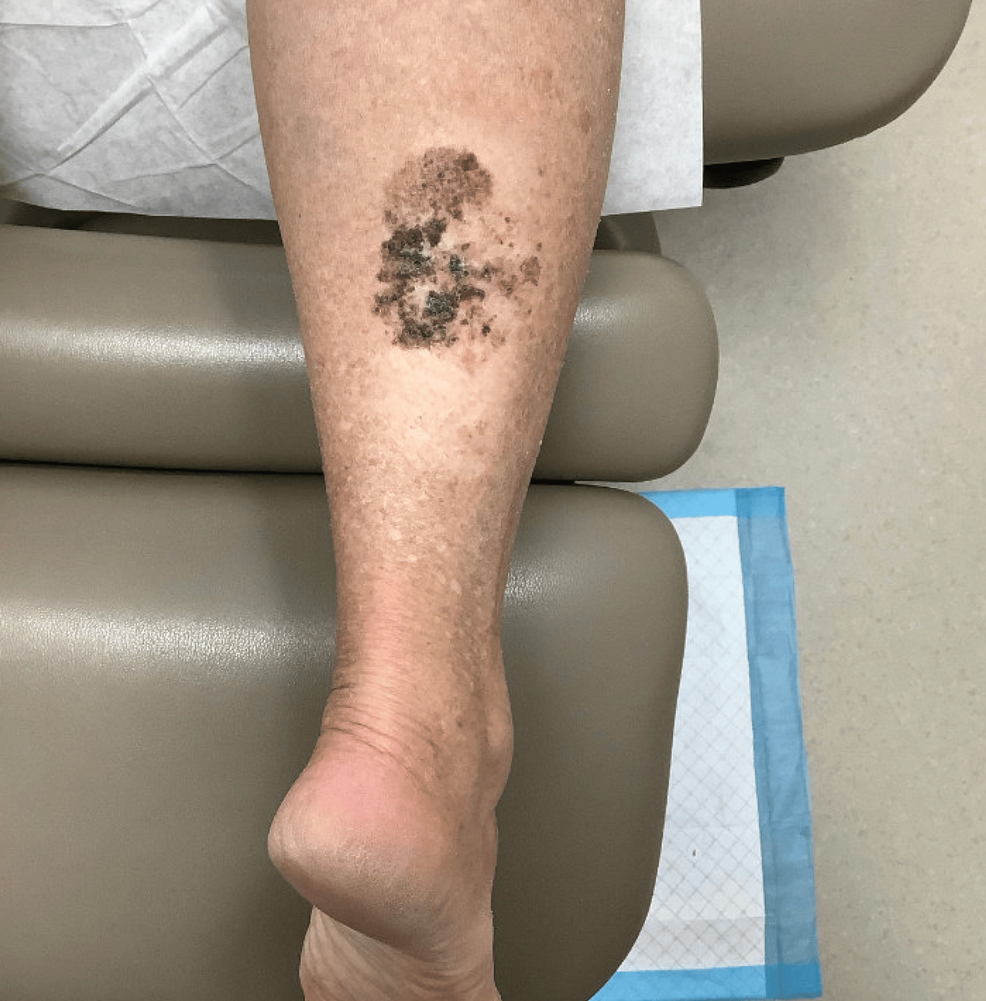
A patient in her 60s with a history of lentigo maligna presented for a routine skin examination at a dermatology clinic, where clinicians discovered a nearly 7 cm variegated brown plaque on her right calf that ultimately required broader re-biopsy to diagnose invasive melanoma, cureus.com reported.
Right Calf Lesion Followed for Years Before Invasive Melanoma Diagnosis
The patient’s dermatologic history included a lentigo maligna on her left cheek diagnosed over 30 years prior and treated successfully with Mohs micrographic surgery. Examination of her right lower extremity revealed a 6.8 cm irregular, variegated brown plaque with indistinct borders on the posterior calf. The lesion had been monitored clinically for years. Seventeen years prior, clinicians noted a 1 cm presumed seborrheic keratosis at the site. Over the subsequent 14 years, the lesion evolved into a 3 cm asymmetric brown patch, prompting two separate partial scouting shave biopsies that both returned diagnoses of benign lentigo without melanocytic atypia.
Broader Re-Biopsy Exposes Invasive Melanoma After Prior Partial Shaves
Because the lesion continued to show clinical atypia and progressive enlargement, a dermatologic surgeon performed a broader re-biopsy. Histopathologic examination of the larger specimen revealed invasive melanoma arising within a background of florid melanoma in situ with focal regression. The Breslow thickness measured at least 1.0 mm, with lesional cells extending to the biopsy edges alongside background dermal fibrosis and stasis change.
Did you know? Partial biopsy techniques can substantially underestimate or fail to identify melanoma in large or heterogeneous lesions. In a studied series of 1,783 melanoma patients, incisional biopsy left substantial clinical lesion behind, increasing mean Breslow thickness from 0.66 mm on initial biopsy to 1.07 mm upon excision, with upstaging occurring in 21% of patients, according to cureus.com.
Surgeons Perform Wide Local Excision and Lymph Node Biopsy
One month after the diagnosis, the patient underwent wide local excision of the right calf lesion with 1.5 cm clinical margins, followed by a split-thickness skin graft. Surgeons also performed a selective right deep inguinal sentinel lymph node biopsy using preoperative lymphoscintigraphy. The sentinel lymph node measured 2.3 x 2.0 x 1.0 cm. Histopathologic examination identified approximately 14 cells that stained positively with Melanoma Antigen Recognized by T-cells 1 (MART-1) centrally within the node, though these cells were not apparent on hematoxylin and eosin staining. Subsequent staining attempts with SOX10 and tyrosinase failed to highlight the same focus, leading pathologists to report the findings as suspicious for, but not diagnostic of, metastatic melanoma.
Diagnostic Challenges in Atypical Lower Extremity Pigmented Lesions
The case highlights well-documented hurdles in evaluating broad pigmented lesions, particularly on the lower extremities of older patients where chronic venous stasis and photodamage cause dermal melanophages, pigment incontinence, and fibrosis that can mimic or obscure melanocytic neoplasia. Focal regression—identified in this patient's diagnostic biopsy and present in 10% to 35% of cutaneous melanomas—can complicate staging by thinning previously deeper tumors.
Common Questions Regarding Atypical Lesion Biopsies
Why do partial biopsies sometimes miss melanoma in large lesions?
Partial or incisional biopsies sample only a fraction of a heterogeneous lesion, which can miss invasive components. Research cited by cureus.com indicates that punch biopsies carry a significantly increased odds of histopathologic misdiagnosis compared with complete excisional biopsies.
What is the preferred biopsy method for suspicious pigmented lesions?
The American Academy of Dermatology recommends excisional or complete biopsy as the preferred approach to preserve lesional architecture. Partial biopsies are generally reserved for large lesions or difficult anatomic sites and should target the clinically thickest or most atypical area.
What did the sentinel lymph node biopsy reveal in this patient?
The biopsy identified about 14 cells staining positively for MART-1 in the center of a 2.3 cm lymph node, but these cells did not appear on routine H&E stains or secondary SOX10 and tyrosinase stains, resulting in an interpretation of indeterminate significance rather than definitive metastasis.
Worth a look