
Genomic researchers analyzing archival blood samples have uncovered epigenetic signatures associated with breast and prostate cancer up to nine years before clinical diagnosis. Published in Cell Genomics, the study by Nicholas Cheng, Tom W. Ouellette, Kimberly Skead, and colleagues examined genome-wide cell-free DNA methylation patterns from 491 plasma samples, finding that regulatory-element modifications provide subtle clues about future disease risk long before tumors become apparent by standard screening.
Genomic Methylation Patterns Detected in Archived Plasma
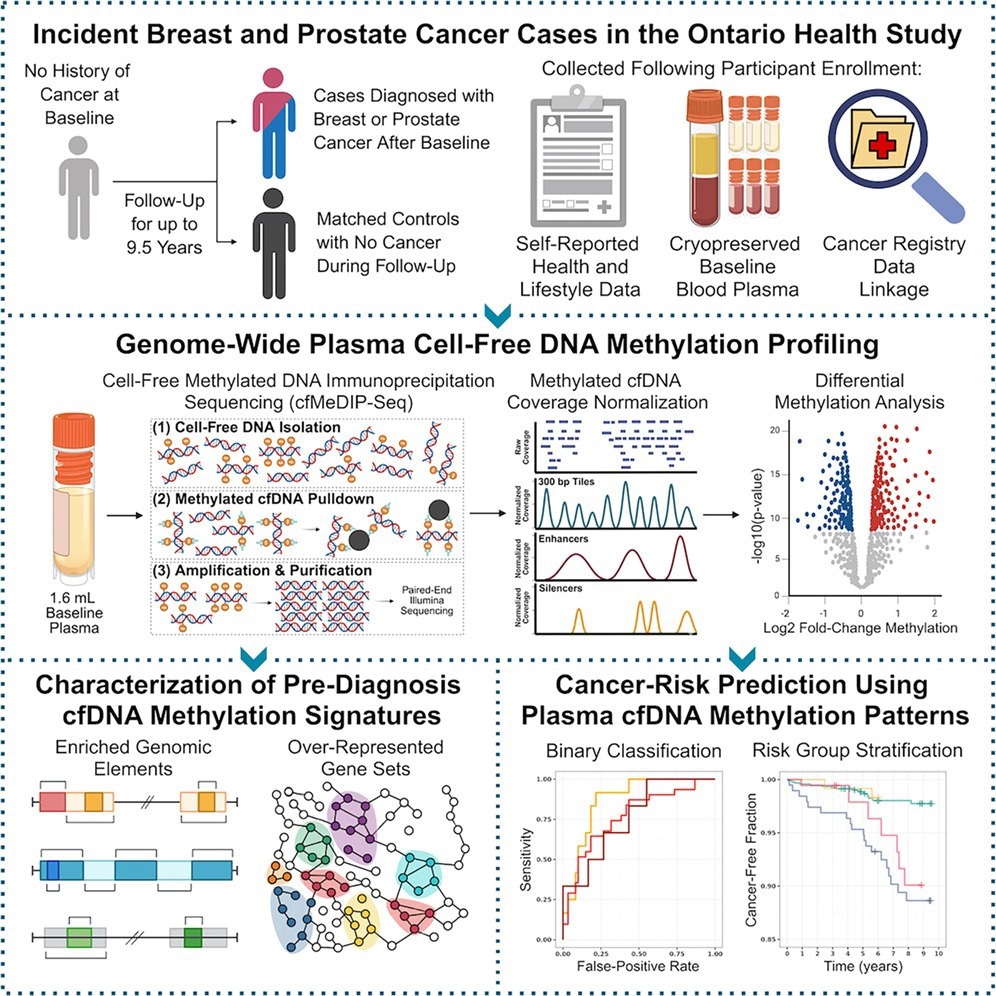
The research team utilized biospecimens from the Ontario Health Study, a prospective population cohort that gathered biological samples and health data from more than 40,000 participants. By linking this cohort with the Canadian Cancer Registry, investigators identified individuals who were cancer-free at blood collection but subsequently developed breast or prostate cancer up to nine years later. Matched cancer-free controls were selected based on factors such as age, sample timing, smoking, and alcohol consumption.
To examine the methylome, investigators used cell-free methylated DNA immunoprecipitation sequencing, known as cfMeDIP-seq. Following quality control, the final analysis included 171 incident breast cancer cases, 93 incident prostate cancer cases, and 227 cancer-free controls. For breast cancer, 67.8% of the incident cases were stage I, and nearly 89% of participants had undergone mammography before providing blood. This focus on early-stage disease is critical because localized tumors typically shed very little tumor-derived DNA into the bloodstream.
Regulatory Regions and Biological Pathways Preceding Diagnosis
Instead of restricting their focus to individual cancer-associated genes, the authors analyzed genome-wide methylation patterns. Differentially methylated regions identified prior to diagnosis mapped heavily to promoters, enhancers, silencers, and repetitive elements, with approximately 37.5% to 51.2% of leading regions located in these regulatory zones. According to the study, these regions associated with DNA repair, hypoxia, P53 signaling, hormonal regulation, cell growth, and immune processes.
The investigators interpret these findings as evidence that pre-diagnosis plasma cfDNA contains signals originating not solely from emerging tumor cells, but also from systemic host and immune changes. Because tiny early-stage tumors release minimal direct DNA, successful blood-based detection may require capturing both tumor-specific and host-derived biological shifts.
Modest Predictive Performance in Breast Cancer Risk Stratification
For breast cancer, hypermethylated enhancer regions yielded the strongest predictive signals. A penalized logistic-regression classifier built on the top 90 hypermethylated enhancer regions achieved a cross-validated AUROC of 0.62 and a C-index of 0.61 in a discovery cohort of 99 breast cancer cases and 99 controls. Performance dipped in the independent held-out cohort of 72 cases and 44 controls. Consequently, the authors explicitly acknowledge that the assay lacks sufficient stand-alone diagnostic utility to replace mammography.
Despite limited individual discrimination, the methylation score separated groups with varying future breast cancer incidence. Using a prespecified threshold, women classified as high risk in the discovery set experienced a 3.6% five-year breast cancer incidence compared to 1.2% in the low-risk group. In the held-out cohort, the eight-year incidence reached 6.2% for high-risk participants versus 1.8% for low-risk participants. Risk curves began separating roughly 1.5 years before diagnosis, with an estimated hazard ratio of 2.3 in the held-out cohort, though the confidence interval ranged from 0.9 to 6.0 and was not statistically significant at P=0.09.
Did you know? The study demonstrated that classifier performance jumped significantly when tested on an external cohort of patients with established late-stage breast cancer from the OCTANE study, yielding an AUROC of 0.87 compared to Ontario Health Study controls and 0.94 against external non-breast cancer samples.
Influence of Subtype, Age, and Mammography Timing
Classifier performance varied across clinical and demographic subgroups. Receiver information suggested that pre-diagnosis performance appeared higher in triple-negative and HR-positive/HER2-positive breast cancer subtypes, yielding C-index values of approximately 0.73 and 0.78 in the test dataset. However, these estimates relied on only three cases in each subgroup, producing wide confidence intervals that require validation in larger cohorts.
Age also affected the model. In the held-out pre-diagnosis cohort, the highest C-index of 0.67 occurred among women diagnosed between ages 30 and 50, dropping to 0.49 for those diagnosed after age 70. Classifier performance tracked with the timing of the most recent mammogram before blood draw. Performance was lowest when mammography occurred within six months of blood collection, but increased when the last scan happened one to two years earlier, or more than two years prior. This pattern points toward the potential for blood-based biomarkers to act as a complementary tool alongside imaging rather than a direct substitute.
Technical Standardization and Study Limitations
Laboratory parameters proved crucial to the assay’s success. Variations in immunoprecipitation efficiency and sequencing complexity shifted risk scores, emphasizing that analytical standardization is mandatory before population-scale implementation.
Blood test cannot yet replace mammogram screenings
Can this blood test replace a mammogram for breast cancer screening?
No. The study authors emphasize that current sensitivity in early-stage breast cancer is insufficient for stand-alone diagnostic use. The tool is envisioned as a potential future method for risk-adapted screening rather than a replacement for imaging.
How far in advance can these epigenetic signals be detected?
Genome-wide cell-free DNA methylation signatures were detected in plasma samples collected anywhere from two weeks to as long as nine years before clinical diagnosis of breast or prostate cancer.
What biological regions provided the strongest predictive signals?
For breast cancer, hypermethylated enhancer regions produced the strongest predictive performance.
Did cancer subtype or patient age affect test performance?
Yes. Preliminary analysis indicated variations in performance across tumor subtypes and patient ages, with higher C-indices observed among younger women aged 30 to 50 compared to those diagnosed after age 70.
Keep reading