Six-Year-Old Boy Diagnosed With Craniopharyngioma After Influenza a Admission
A six-year-old boy admitted to the hospital with influenza A, fever, vomiting, diarrhoea, and drowsiness was subsequently diagnosed with a large craniopharyngioma. The patient experienced profound hypoglycaemia and hyponatraemia during his admission, leading medical staff to initiate a hypoglycaemia screen that revealed an inadequate random serum cortisol level of 207 nmol/L.
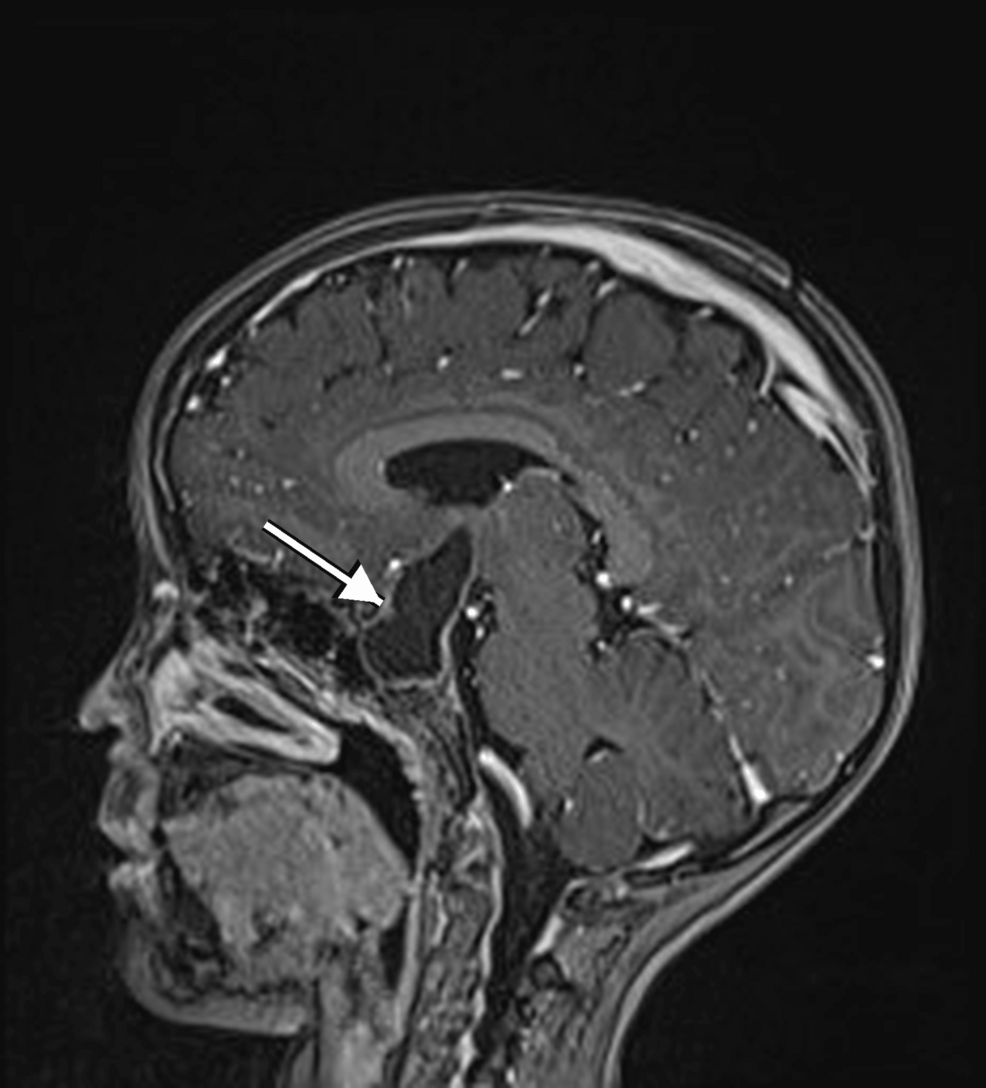
Further endocrine evaluations confirmed central adrenal insufficiency alongside additional pituitary hormone deficiencies. Magnetic resonance imaging of the head identified a 43 by 28 by 22 millimetre cystic sellar and suprasellar lesion causing compression of the optic chiasm.
Clinical Findings and Endocrine Evaluations
During the acute illness, the patient’s serum sodium dropped to 127 mmol/L while capillary blood glucose became unrecordable. An urgent short Synacthen test demonstrated adrenal insufficiency, showing a baseline cortisol of 27 nmol/L that rose only to 105 nmol/L after 30 minutes and 143 nmol/L after 60 minutes. Thyroid function tests indicated a free T4 level of 3.4 pmol/L with a TSH of 0.8 mU/L, consistent with central hypothyroidism.
Before the MRI scan, clinicians diagnosed diabetes insipidus and commenced treatment with desmopressin. The patient’s mother reported a long-standing history of polyuria and polydipsia with a daily fluid intake of 2.5 to 3 litres, alongside low energy levels, lethargy, recurrent infections, and slowed growth.
Did you know? Growth hormone deficiency is the most common deficit at diagnosis in pediatric craniopharyngioma cases, affecting roughly 75% of patients.
Surgical Decompression and Histology Results
The patient was transferred to a pediatric neurosurgical unit and underwent endoscopic trans-sphenoidal decompression of the lesion. Histological analysis confirmed the diagnosis of an adamantinomatous craniopharyngioma. Post-operative imaging showed the cystic component was decompressed and optic chiasm distortion improved.
At follow-up appointments, the patient remained on hydrocortisone, levothyroxine, and desmopressin replacement therapy, accompanied by ongoing endocrine surveillance. The report highlights that while infections frequently trigger hypoglycaemia in children, recurrent or severe episodes accompanied by hyponatraemia warrant thorough investigation for underlying endocrine causes.
Common symptoms and tumor details in this case
What common symptoms delayed the diagnosis in this case?
The patient experienced long-standing polyuria and polydipsia, low energy, lethargy, and slowed growth that went uninvestigated before his hospital admission for influenza A.
How large was the tumor identified on the MRI scan?
Magnetic resonance imaging revealed a large cystic sellar and suprasellar mass measuring approximately 43 by 28 by 22 millimetres that distorted the optic chiasm.
What hormone deficiencies were confirmed prior to surgery?
Further endocrine evaluations confirmed central adrenal insufficiency, central hypothyroidism, and diabetes insipidus.
What surgical procedure did the patient undergo?
The patient underwent endoscopic trans-sphenoidal decompression at a pediatric neurosurgical unit, which successfully relieved compression on the optic chiasm.