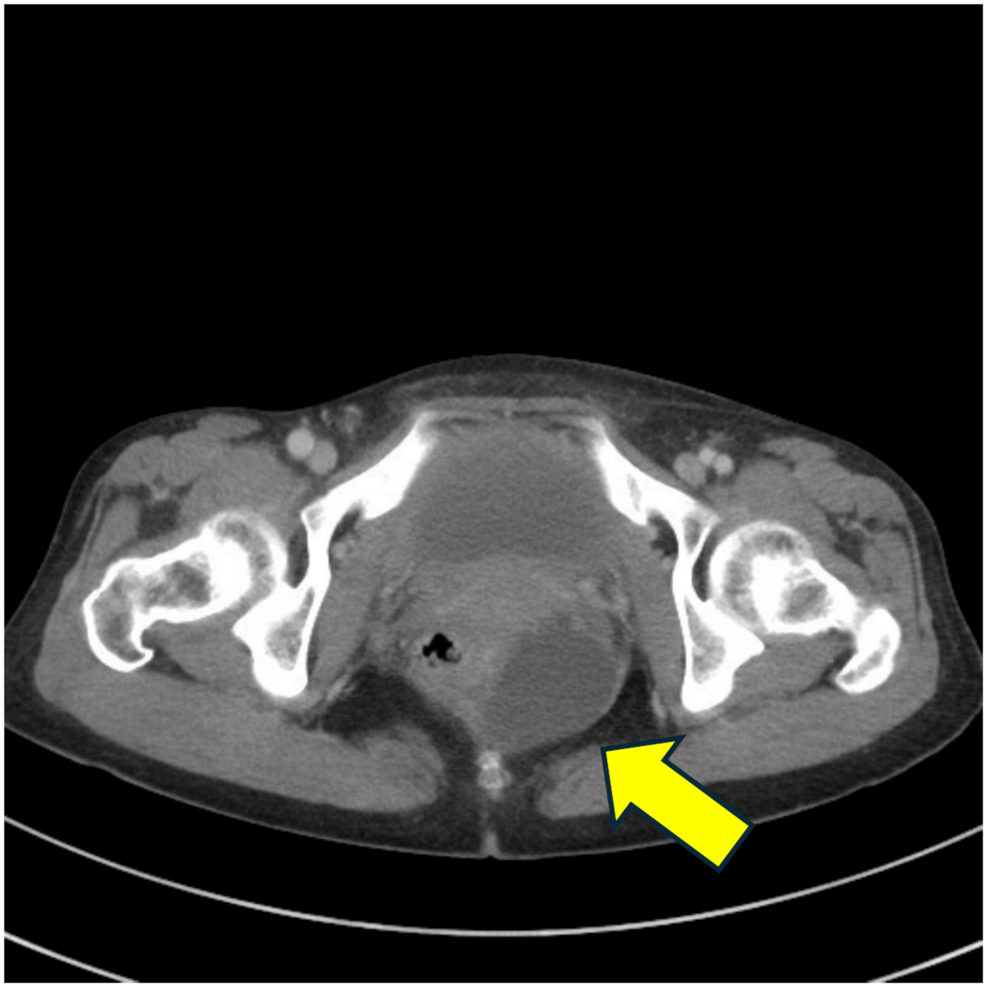
A 49-millimeter presacral epidermoid cyst—measuring below the conventional 5-centimeter threshold typically requiring a combined surgical approach—was successfully removed via a laparoscopic-assisted transabdominal-transsacral procedure at an unnamed institution, Cureus reported. Medical teams determined that the tumor’s intimate anatomical relationship to the lower rectum, coccyx, and pelvic splanchnic nerves necessitated a dual approach rather than relying on size criteria alone.
Anatomical Complexity Overrides Tumor Size in Presacral Tumor Resection
Pelvic magnetic resonance imaging revealed the mass sat in close contact with the lower rectum and coccyx.
While the tumor’s upper border lay below the third sacral vertebra—the anatomical threshold where a posterior-only approach is often considered sufficient—surgeons opted for the combined technique. This decision ensured reliable preservation of the S4 pelvic splanchnic nerves and established a clear dissection plane away from the rectal wall. Pathological examination of the resected specimen, which contained a gray, porridge-like substance, confirmed a benign epidermoid cyst with negative resection margins after en bloc excision with the coccyx.
Laparoscopic Synergy and Surgical Technique
The operation combined a five-port laparoscopic phase with a subsequent gluteal transsacral approach. During the initial abdominal phase, surgeons mobilized the rectosigmoid colon and performed circumferential rectal mobilization down to the level of the upper anal canal. This magnified visualization allowed precise dissection between the posterior rectal wall and the anterior tumor surface, alongside safe separation from the bilateral pelvic splanchnic nerves. Once adequate working space was secured laparoscopically, the patient was repositioned to the jackknife position. An 8-centimeter oblique gluteal incision replaced a traditional midline parasacrococcygeal approach to better distribute wound tension and reduce contamination risks from the anal region.
Clinical Insight: A review of the Japanese literature identified 57 total cases of presacral epidermoid cysts, showing a mean patient age of 49 years and a distinct female predominance of 39 women to 18 men. Incidental discovery accounted for 28 percent of presentations, while pain-related symptoms occurred in 26.3 percent of cases.
Malignancy Risks and Recurrence Monitoring
Presacral developmental cysts carry a rare but significant risk of malignant transformation into squamous cell carcinoma. Because preoperative fine-needle aspiration biopsies carry distinct risks of tumor dissemination and local infection, definitive tissue diagnoses are frequently delayed until complete surgical excision is performed. Local recurrence has been documented following incomplete resections even in histologically benign cases. Although the exact pathogenesis of malignant transformation remains unclear, chronic epithelial irritation driven by cyst inflammation serves as a proposed contributing mechanism in medical literature.
Frequently Asked Questions
Why was a combined surgical approach chosen for a tumor under 5 centimeters?
Surgeons selected the combined laparoscopic-assisted transabdominal-transsacral approach because the 49-millimeter mass maintained an intimate anatomical relationship with the lower rectum, coccyx, and pelvic splanchnic nerves, making a posterior-only excision unsafe.
How long was the patient hospitalized following the surgery?
The patient experienced an uneventful postoperative recovery, had her drain removed on postoperative day 6, and was discharged on postoperative day 8 without any complications or bowel and bladder dysfunction.
What are the primary diagnostic challenges of presacral epidermoid cysts?
Most epidermoid cysts are discovered incidentally on computed tomography or magnetic resonance imaging, and preoperative imaging is generally insufficient to differentiate them from tailgut cysts or dermoid cysts without pathological examination.
Keep reading