Wernicke’s encephalopathy (WE) can occur in pregnant women experiencing prolonged vomiting, even when severe preeclampsia is present. A case report published by Cureus describes a 19-year-old primigravida at 24 weeks’ gestation who showed favorable neurological progress after receiving urgent thiamine supplementation for a neurological emergency.
Preeclampsia masked thiamine deficiency in 19-year-old patient
A 19-year-old pregnant woman was admitted to the intensive care unit with altered consciousness, cerebellar ataxia, and oculomotor abnormalities following several weeks of prolonged vomiting and epigastric pain, Cureus reported. The patient presented with a Glasgow Coma Scale score of 12/15, confusion, and agitation.
Clinical findings included severe hypertension at 161/95 mmHg, tachycardia at 126 beats per minute, and 3+ proteinuria. Laboratory tests showed significant metabolic disturbances, including a serum creatinine of 11.31 mg/L, potassium at 3 mmol/L, and sodium at 132 mmol/L. These markers, combined with hypertension and proteinuria, indicated severe preeclampsia.
Did you know? The classic diagnostic triad for Wernicke’s encephalopathy consists of impaired consciousness, oculomotor abnormalities, and cerebellar ataxia, though not all patients exhibit all three signs.
MRI revealed brain lesions after CT scan showed no abnormalities
Initial diagnostic efforts focused on the patient’s hypertensive state. A brain computed tomography (CT) scan with contrast was unremarkable and failed to explain the patient’s neurological symptoms. Because the neurological condition worsened, doctors performed an emergency cesarean section to terminate the pregnancy.
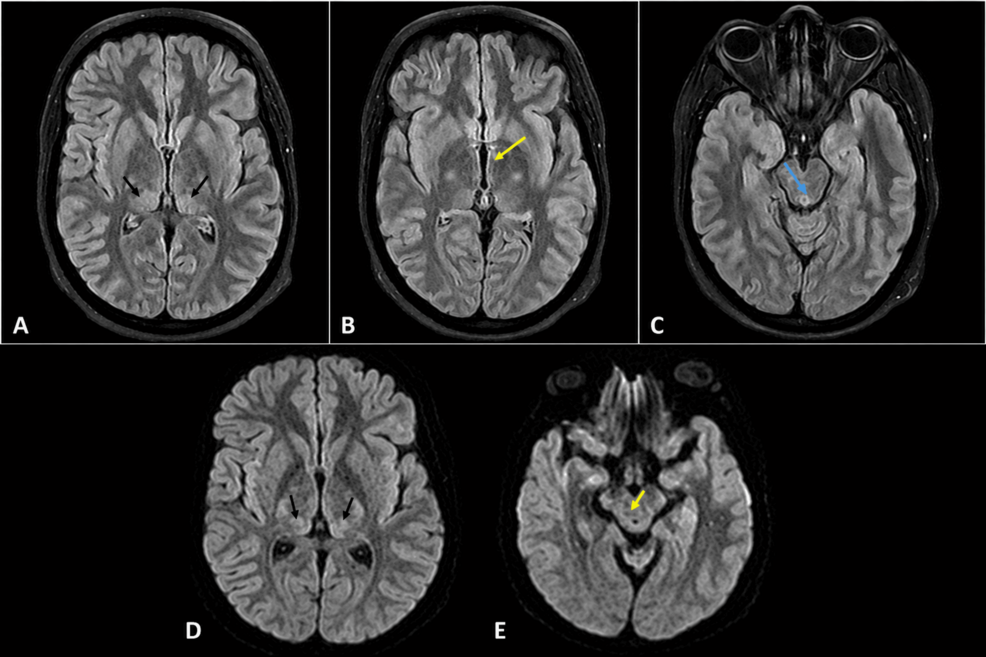
Subsequent brain magnetic resonance imaging (MRI) identified symmetrical lesions. These abnormalities were located in the mammillary bodies, the periaqueductal region, the thalami, and periventricular areas. The MRI findings were consistent with WE, which is caused by a deficiency of thiamine (vitamin B1) essential for cerebral energy metabolism.
| Parameter | Patient Value | Reference Range |
|---|---|---|
| AST | 322 U/L | 10-40 U/L |
| ALT | 287 U/L | 7-56 U/L |
| P/C ratio | 120 mg/mmol | <30 mg/mmol |
Thiamine administration led to complete clinical recovery
Medical staff initiated urgent thiamine supplementation at a dose of 200-500 mg three times daily for three to five days, followed by oral doses of 250-1000 mg daily. This treatment was paired with nutritional support and the correction of hydro-electrolytic and metabolic disorders.
The patient’s neurological status improved progressively. Her level of consciousness returned to normal, and laboratory abnormalities normalized. She was discharged from the hospital five days after treatment began.
Pro tip: European Federation of Neurological Societies (EFNS) guidelines recommend administering 200 mg of IV thiamine three times a day for suspected WE before the patient receives any carbohydrate intake.
Vomiting and malnutrition create diagnostic pitfalls in pregnancy
While WE is frequently linked to chronic alcoholism, it can occur in any setting of malnutrition that depletes thiamine reserves, which typically last two to three weeks. In pregnant women, hyperemesis gravidarum is a primary risk factor. Because pregnancy increases the body’s need for thiamine, symptoms can emerge as early as the sixth week of gestation.
The coexistence of preeclampsia creates a diagnostic challenge because its neurological complications overlap with WE. In hypertensive patients, clinicians often first investigate for eclampsia or posterior reversible encephalopathy syndrome (PRES). However, the presence of persistent nystagmus and ataxia alongside malnutrition should prompt a search for thiamine deficiency.
MRI is a critical tool for early diagnosis, with a reported sensitivity of 92-93% and specificity near 100%. The case highlights that treatment should begin immediately upon clinical suspicion, as waiting for laboratory confirmation can lead to irreversible neurological sequelae, Korsakoff’s syndrome, coma, or death.
Common questions about thiamine deficiency in pregnancy
Can a normal CT scan rule out Wernicke’s encephalopathy?
No. As shown in the reported case, brain CT scans may remain normal even when a patient is suffering from WE; MRI is required for higher sensitivity in detecting symmetrical lesions.
What is the mortality rate for untreated Wernicke’s encephalopathy?
The reported mortality rate for the condition is between 20% and 30%.
Why does hyperemesis gravidarum lead to this condition?
Prolonged vomiting leads to the rapid depletion of thiamine reserves, which is compounded by the increased metabolic demand for vitamin B1 during pregnancy.
Related reading