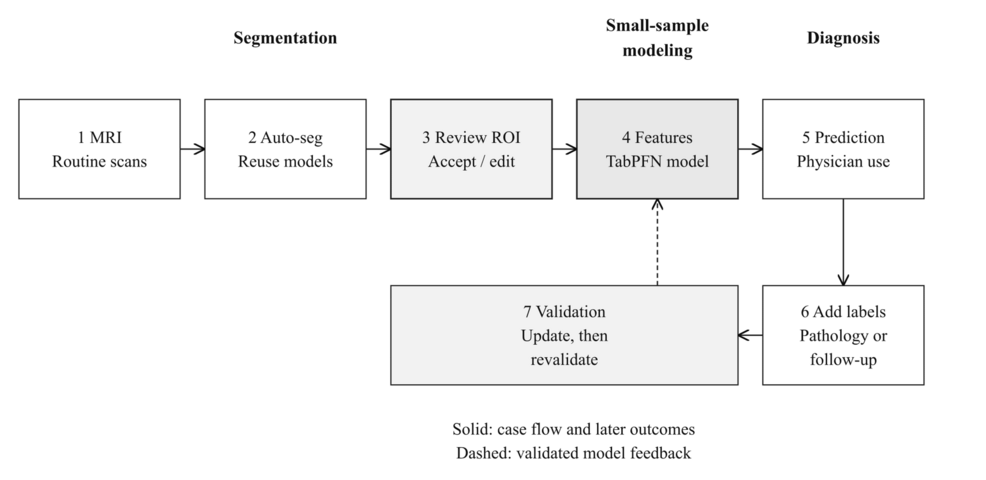
Automated deep learning models are transforming neuro-oncology by delivering precise volumetric measurements for intracranial tumors on preoperative scans.
Meningiomas represent roughly 37 percent of all primary brain neoplasms, making them the most frequently encountered primary intracranial tumors in clinical practice, according to data from pmc.ncbi.nlm.nih.gov.
Because these slow-growing lesions often require long-term surveillance, clinicians rely heavily on neuroimaging for initial detection, longitudinal monitoring, and surgical planning. Traditional assessments depend largely on manual linear measurements. However, these linear approaches can fail to capture true tumor burden accurately.
Volumetric analysis offers a more reliable metric for monitoring tumor growth, yet manual segmentation remains labor-intensive and susceptible to interrater variability. To address these bottlenecks, researchers published a [new study in Neuroradiology on Aug. 20, 2026] evaluating an automated deep learning framework for meningioma assessment. De Wilde, Zanier, Alakmeh et al. trained their algorithm on contrast-enhanced T1-weighted and FLAIR MRI scans gathered from 100 patients at the University Hospital Zurich.
External Validation Results Across Multicenter Datasets
The Zurich research team tested their nnU-Net deep learning model against independent datasets to measure real-world performance consistency.
During internal cross-validation, the model achieved mean Dice similarity coefficient scores of 0.87 plus or minus 0.23 for meningioma segmentation. For associated peritumoral edema, the internal cross-validation yielded a mean Dice score of 0.63 plus or minus 0.38. When evaluated on an external validation set comprising 88 cases from the meningioma SEG-Class dataset via the Cancer Imaging Archive, the algorithm maintained high accuracy for tumor delineation while showing reduced performance on edema boundaries.
On the external validation cohort, the model scored 0.86 plus or minus 0.17 for meningioma segmentation and 0.31 plus or minus 0.35 for edema. These findings indicate that while core tumor boundaries translate reliably across different clinical environments, peritumoral fluid dynamics remain challenging for automated boundary detection.
Expanding Public Data Repositories
Beyond single-institution architectures, international research groups are actively expanding public data repositories and multi-institutional segmentation tools to refine predictive workflows.
LaBella et al. released 1,141 preoperative MRI examinations with World Health Organization grades available for 800 cases, Cureus reported. Their background data showed that approximately 80 percent of meningiomas are classified as grade 1. Skull-stripping techniques within these public frameworks exclude extracranial tumor components, helping standardize preprocessing for invasive or skull-base lesions.
Further methodological investigations have evaluated tabular prior-data fitted networks to connect imaging features with clinical variables. Huryol et al. studied 455 cases, including an external cohort of 109, utilizing TabPFN for radiomics and clinical feature analysis, Cureus noted. Their external area under the curve results reached 0.628 for radiomics alone, 0.645 for clinical variables, and 0.732 for the nnU-Net pathway, while the best combined model achieved 0.742.
Common Questions Regarding Neuroimaging Segmentation
What is the primary advantage of automated meningioma segmentation?
Automated tools cut the time needed for volumetric assessment and reduce the differences between reviewers that manual contouring causes.
How do researchers evaluate segmentation accuracy?
Performance is typically measured using the Dice similarity coefficient, Jaccard index, and the 95th percentile Hausdorff distance against expert reference annotations.
Why does peritumoral edema score lower in external validation?
Edema boundaries feature diffuse, gradual transitions in signal intensity compared to distinct tumor margins, making consistent automated contouring more difficult across different scanner protocols.
Future work should focus on validating model performance across larger multi-center datasets.
Worth a look