Medical reports describe an uncommon case of epidural Ewing sarcoma in a 20-year-old male patient who presented with severe spinal cord compression and lower flaccid paraparesis, requiring emergency surgical decompression followed by adjuvant chemotherapy and radiotherapy.
Thoracic Spinal Cord Compression as the Initial Presentation
Ewing sarcoma typically arises in the diaphyses of long tubular bones in the lower extremities and predominantly affects children and adolescents in their second decade of life, with the average onset occurring around age 20. Primary spinal involvement remains exceedingly rare, accounting for an estimated 3.5 to 14.9% of all bone involvement. When the tumor localizes to the epidural space of the thoracic spine rather than the more common sacral region, it presents distinct diagnostic challenges due to nonspecific radiological findings and unusual anatomical positioning.
Medical documentation highlights the case of a 20-year-old male admitted to a neurology department after experiencing two days of gradually progressive symmetrical muscle weakness and numbness that began in the feet and ascended to the torso. The patient developed complete immobility and difficulty urinating for 16 to 17 hours before receiving a catheter. Clinical examination revealed severe lower flaccid paraparesis, graded as III in both lower limbs, alongside muscle hypotonia, markedly diminished knee reflexes, absent Achilles reflexes bilaterally, and positive Babinski signs.
Patient Undergoes Emergency Neurosurgery for Spinal Cord Decompression
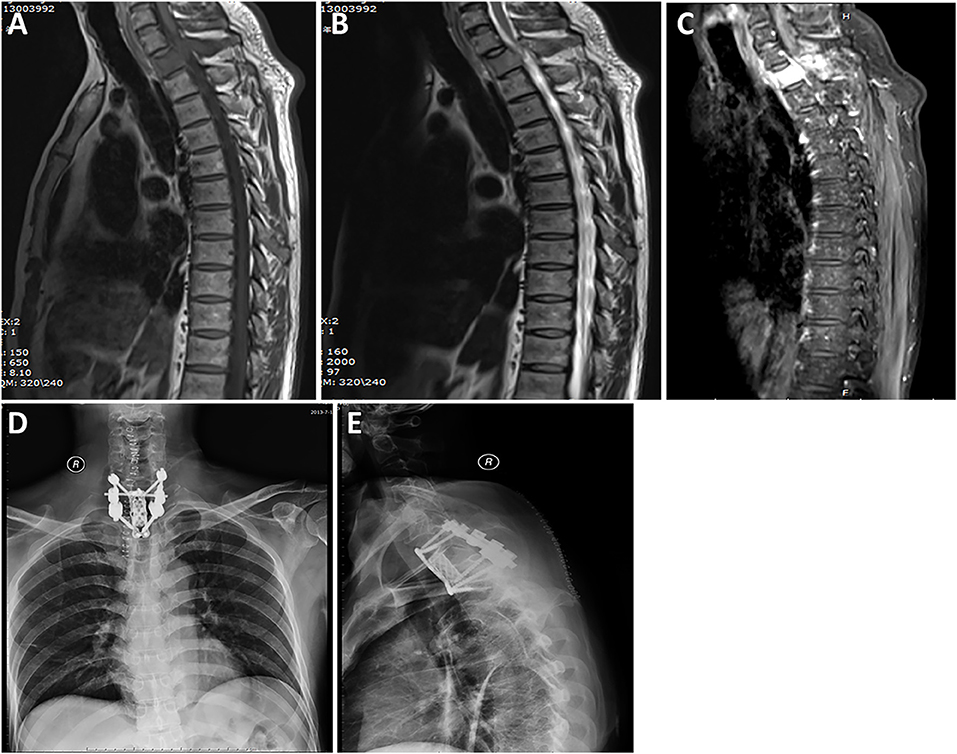
Magnetic resonance imaging of the spine revealed an epidural tumor spanning TH5-TH7 vertebral levels. Computed tomography of the chest identified a soft tissue formation along the middle axillary line at the sixth rib on the left side, featuring rib destruction, lung invasion, and a small reactive pleural effusion.
Because of critical neurological symptoms and progressive medullary compression, the patient underwent emergency neurosurgical treatment. The procedure involved thoracic laminectomies and maximal possible tumor resection to achieve effective spinal cord decompression. Subsequent histopathological examination of the surgical specimen confirmed the diagnosis, revealing a malignant tumor consisting of undifferentiated small cells characteristic of Ewing sarcoma.
Adjuvant Treatment Protocols and Postoperative Monitoring
Following the uneventful postoperative recovery, the management plan incorporated multidisciplinary oncological care. The patient received adjuvant chemotherapy and radiotherapy. Medical literature notes that therapeutic approaches for Ewing sarcoma typically involve diagnostic biopsy, chemotherapy, surgical resection, and local radiation therapy.
Six months into the follow-up period, clinical evaluations showed a satisfactory overall condition with significant improvement in gait.
James Ewing Introduced Diffuse Malignant Bone Endothelioma
Historical records show that James Ewing first introduced the term diffuse malignant bone endothelioma in 1921 as a primary malignant tumor striking young patients, particularly during their second decade of life. These neoplasms belong to a family of tumors united by shared histological and immunohistochemical properties, alongside the presence of the t(11;22) chromosomal translocation.