Severe Hypernatremic Dehydration Triggers Rare Neonatal NEC
Necrotizing enterocolitis struck a previously healthy term neonate who suffered profound dehydration from inadequate breastfeeding.
Medical literature documents only one prior instance of necrotizing enterocolitis linked to severe hypernatremic dehydration, described by Clarke and Sibert in 1985. While necrotizing enterocolitis predominantly affects preterm infants at rates of 5% to 10% in very low birth weight babies, roughly 9% to 17% of cases occur in term neonates.
The condition represents the most common gastrointestinal emergency in neonates. Mortality reaches approximately 23.5% overall and climbs to 34.5% for surgical cases.
Breastfeeding-associated hypernatremic dehydration impacts 1.9% to 4.9% of hospitalized term neonates. Risk factors include primiparity, delayed breastfeeding initiation, and inadequate milk transfer.
Clinical Presentation and Emergency Admission
A two-week-old female infant weighing 2.625 kg arrived at a community hospital with fever, lethargy, and a 30% weight loss from her 3,750-g birth weight. Her mother reported poor feeding, excessive crying, and two to three wet diapers daily for several days. Physical examination revealed a sunken anterior fontanelle, dry mucous membranes, and a distended abdomen.
Initial laboratory work showed a serum sodium level of 176 mmol/L, a white blood cell count of 30.8 ×10³/µL, and a C-reactive protein of 330 mg/L. Additional findings included blood urea nitrogen at 120 mg/dL and creatinine at 2.93 mg/dL, indicating acute kidney injury. Medical staff administered three normal saline boluses, placed a nasogastric tube, and started empiric intravenous ampicillin, ceftazidime, and acyclovir.
Surgical Intervention in the Pediatric Intensive Care Unit
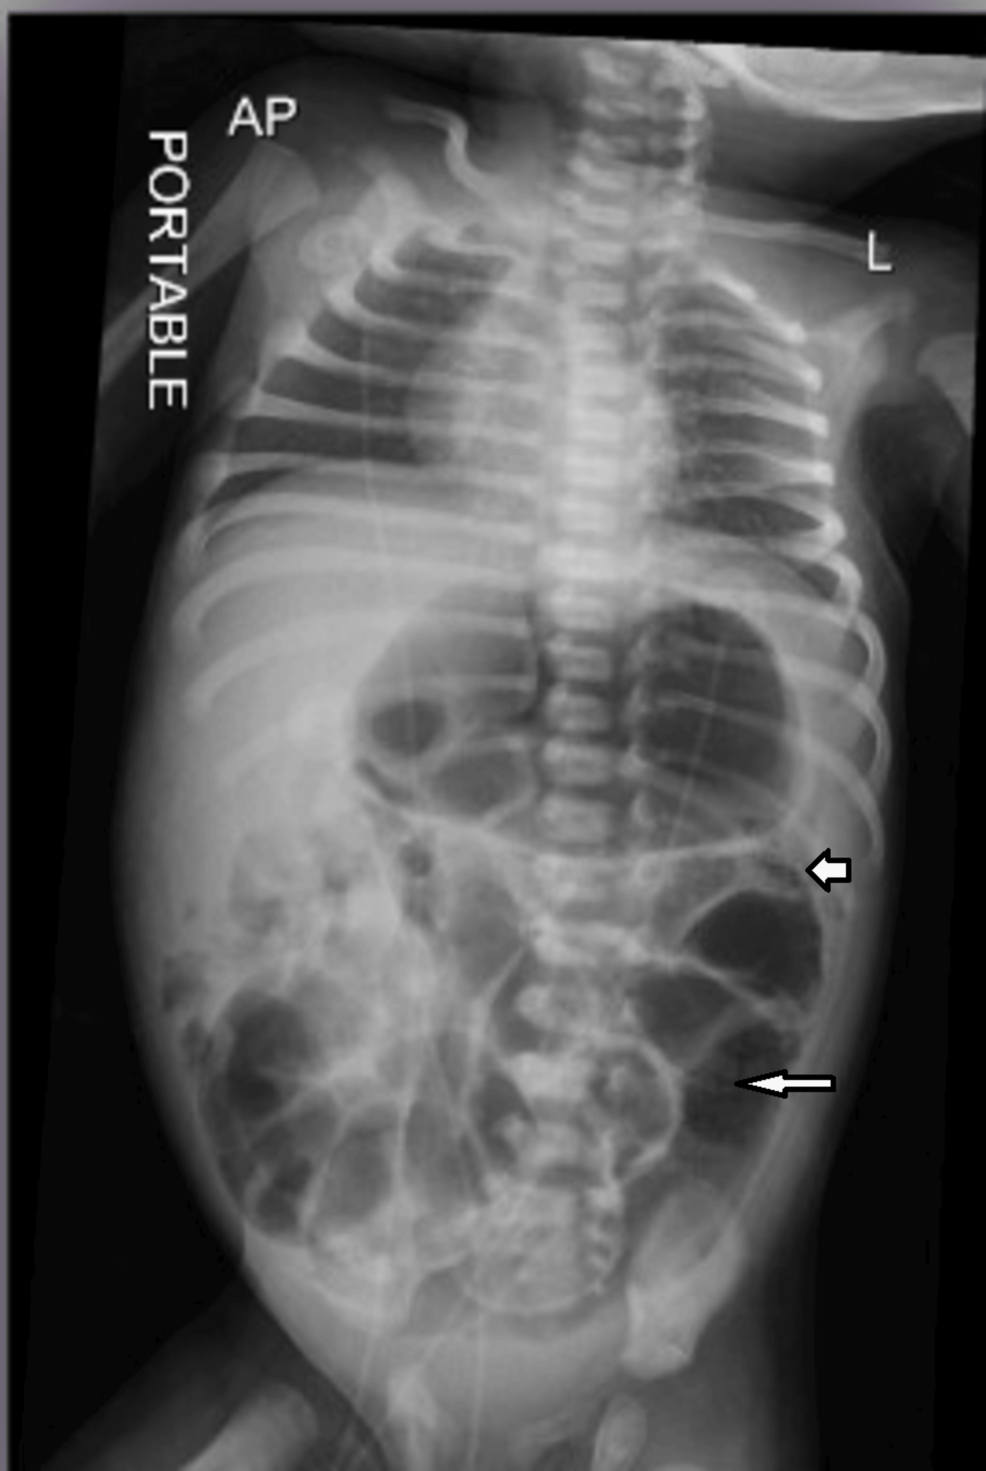
Transferred to a tertiary pediatric intensive care unit, the infant developed worsening abdominal distension with bloody stools. Abdominal imaging revealed pneumatosis intestinalis and pneumoperitoneum, pointing to bowel perforation.
Pediatric surgery performed an emergent exploratory laparotomy. The procedure uncovered copious purulent material, extensive peritonitis, and a right upper quadrant bowel perforation. Surgeons performed an end-ileostomy in the left lower quadrant and created a mucous fistula in the right lower quadrant.
Postoperative Recovery and Subsequent Readmission
Postoperative care involved mechanical ventilation, targeted sedation, and a gradual sodium correction rate using D5 ½ normal saline. Intraoperative cultures grew pan-sensitive Escherichia coli and Staphylococcus lugdunensis, treated with a 14-day course of piperacillin-tazobactam. An eight-day postoperative leukocytosis prompted interventional radiology to drain a large intra-abdominal fluid collection.
After a 53-day hospital stay, the infant left for home tolerating full oral breast milk feeds with a serum sodium level of 138 mEq/L. One day later, she returned with fever, non-bilious emesis, and recurrent hypernatremia at 153 mmol/L. Four months later, she underwent successful ileostomy reversal and the resection of a Meckel’s diverticulum.
Frequently Asked Questions About Neonatal Hypernatremia and NEC
What caused the infant’s severe hypernatremic dehydration?
The infant experienced severe dehydration due to breastfeeding-associated inadequate intake during her first two weeks of life. Her mother reported poor feeding and low urine output, resulting in a 30% drop from birth weight.
How does hypernatremia trigger necrotizing enterocolitis?
Profound volume depletion leads to systemic hypovolemia and impaired intestinal microcirculation. This ischemic injury compromises the intestinal mucosa, facilitating bacterial translocation and inflammation.
What surgical procedures were required during treatment?
Surgeons performed an exploratory laparotomy to drain an intra-abdominal infection, created an end-ileostomy in the left lower quadrant, and formed a mucous fistula. She later underwent an ileostomy reversal and resection of a Meckel’s diverticulum.
What complications followed the initial surgery?
Her recovery included anemia, coagulopathy, a high-output ileostomy, functional short bowel syndrome, and an intra-abdominal fluid collection drained by interventional radiology. She also experienced recurrent hypernatremia one day after hospital discharge.
Worth a look