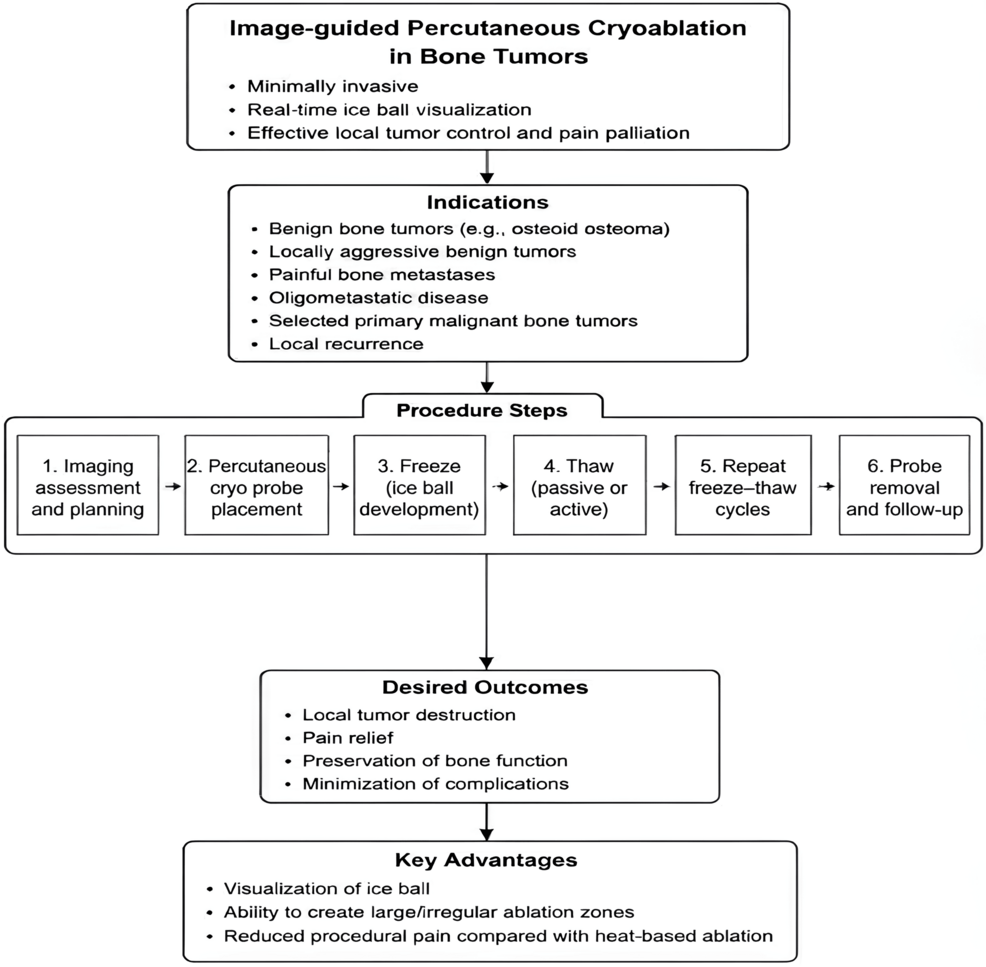
Percutaneous cryoablation has emerged as a minimally invasive, image-guided option for treating bone tumors, offering a way to destroy pathological tissue through controlled freezing. By utilizing specialized probes to form an ice ball, clinicians can manage benign, locally aggressive, and metastatic bone lesions while often reducing post-procedural pain compared to heat-based therapies.
How does the procedure work?
Cryoablation destroys tumor cells by applying temperatures substantially below −100°C, typically using argon gas expansion. According to Cureus, this rapid cooling induces cellular injury through multiple mechanisms, including the formation of intracellular and extracellular ice crystals, which damage membranes and organelles.
The process also creates microvascular injury, leading to platelet aggregation and secondary ischemic necrosis. Because the ice ball’s visible boundary does not always correspond to the lethal isotherm, clinicians must ensure an adequate safety margin of 5–8 mm beyond the tumor to achieve effective local control.
When is cryoablation used?
Physicians select patients based on tumor histology, lesion size, and anatomical location. While surgical resection remains a standard approach, cryoablation serves as a complementary method for patients who are poor surgical candidates or have recurrent disease.
How are healthy tissues protected?
Protecting adjacent structures like nerves, blood vessels, and organs is a critical safety component. Because unintended freezing can cause thermal injury, clinicians often employ techniques such as hydrodissection, where saline or dextrose is injected to physically separate the tumor from vulnerable structures.
| Modality | Mechanism | Monitoring |
|---|---|---|
| Cryoablation | Freeze-induced injury | Visible ice ball |
| Radiofrequency ablation | Thermal coagulation | Indirect |
| Microwave ablation | Dielectric heating | Indirect |
Additional methods, such as pneumodissection or temperature monitoring with sensors, help maintain safety margins in complex areas like the spine or pelvis. Despite these protections, patients remain at risk for complications including pathological fractures, particularly in weight-bearing bones where tumor destruction may further compromise structural integrity.
What is the future of the technique?
The role of cryoablation continues to expand into the management of oligometastatic disease and selected primary malignant tumors. Researchers are increasingly interested in the potential for cryoablation to trigger an antitumor immune response, which could eventually lead to combined therapies involving immune checkpoint inhibitors.
“The available evidence remains heterogeneous, and the optimal indications depend on tumor biology, lesion size, anatomical location, skeletal stability, and therapeutic objectives,” the report said. Future prospective studies are expected to clarify long-term recurrence rates and refine how this modality is integrated into broader oncological care.
Worth a look