Robotic exoskeleton training delivers modest improvements in upper limb motor recovery after a stroke compared with conventional therapy, according to a systematic review and meta-analysis published in Cureus.
Stroke remains a leading cause of long-term disability worldwide, with upper limb dysfunction persisting in up to 66% of survivors after six months. While traditional physical and occupational therapy often struggles to provide the high repetition rates needed to drive neuroplasticity, robotic devices can administer hundreds of guided movements per session.
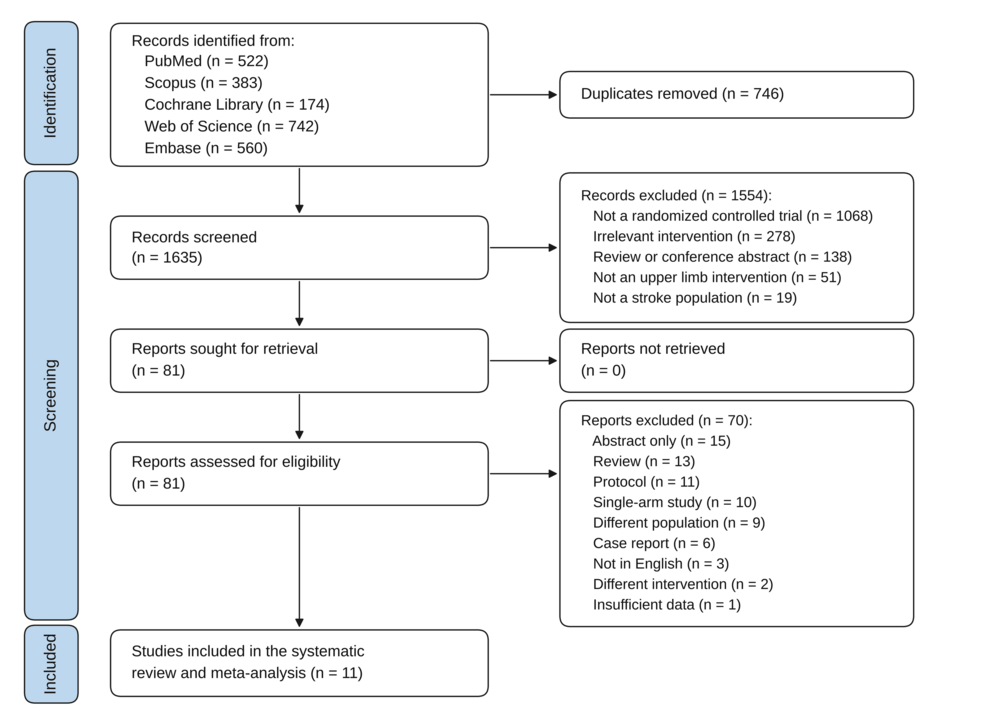
Researchers analyzed 11 randomized controlled trials published between 2009 and 2024, encompassing 338 patients. The pooled data showed a clear overall advantage for exoskeleton-assisted training over conventional methods on the Fugl-Meyer Assessment for Upper Extremity, though the effect size varied depending on recovery stage and the specific limb segment treated.
The timing of the intervention emerged as a major factor in patient outcomes. Four trials enrolling subacute stroke patients showed a pooled mean difference of 5.31 points favoring exoskeleton training, while seven trials involving chronic stroke patients yielded a smaller gain of 1.46 points.

This disparity likely reflects the biological window of heightened neuroplasticity immediately following a brain injury. Peri-infarct and contralesional brain regions show increased responsiveness to task practice during the initial months post-stroke before compensatory patterns solidify.
Beyond timeline differences, physical improvements varied widely across different parts of the arm. The shoulder and elbow musculature demonstrated homogeneous and precise improvements, whereas wrist and hand dexterity showed smaller and more variable changes across the evaluated devices.
Unlike previous broad reviews that grouped various robotic systems together, this study strictly examined wearable exoskeletons that align with and actuate individual joints. The pooled results matched the modest two- to three-point advantages reported by broader robotic syntheses, confirming that device class alone does not overcome the limitations of chronic injury stages.
Functional measures like the Action Research Arm Test also showed clear overall gains, yet spasticity measurements evaluated via the Modified Ashworth Scale revealed no consistent difference between robotic intervention and standard therapy. Investigators said that prediction intervals included no net benefit for future settings, meaning clinicians must interpret average trial gains cautiously when treating individual patients.
Exoskeletons align directly with the patient’s arm and actuate individual joints like the elbow or wrist. End-effector devices guide the limb from a single distal contact point, such as a handgrip, within a restricted workspace.
Dose and effect were not directly correlated in the analysis. Protocols delivering higher training volumes did not automatically yield larger Fugl-Meyer score improvements compared to shorter or less intensive interventions.
Investigators used the Cochrane risk-of-bias tool version 2 to evaluate all 11 randomized controlled trials, rating four studies at low risk of bias, six with some concerns, and one at high risk.