Saturnino Lora Provincial Hospital Tracks 141 STEMI Patients
Timely reperfusion remains a central hurdle in acute myocardial infarction management, particularly where resources are constrained, according to a prospective observational study evaluating 141 consecutive patients diagnosed with ST-segment elevation myocardial infarction (STEMI) at Saturnino Lora Provincial Hospital in Santiago de Cuba. While diagnostic electrocardiogram assessments frequently occurred within standard timeframes, subsequent treatment intervals revealed substantial delays in initiating fibrinolytic therapy and performing percutaneous coronary interventions.
The investigation spanned from January 1, 2018, through January 1, 2019, examining clinical characteristics and specific time intervals across the hospital’s cardiac care pathway. Investigators recorded that 113 patients, or 80.2 percent, were older than 55 years, and 96 patients were male. Typical ischemic chest pain appeared in 137 cases, with anterior wall infarctions identified in 46.8 percent of the study population.
Initial Medical Contact Delays
Initial medical evaluation occurred within 60 minutes of symptom onset for 68 patients, while 67 patients sought medical attention more than 120 minutes after symptoms began. Once patients arrived at a medical facility, staff obtained a diagnostic electrocardiogram within 10 minutes for 102 individuals.
Diagnostic ECG to Fibrinolysis and Reperfusion Strategy Breakdown
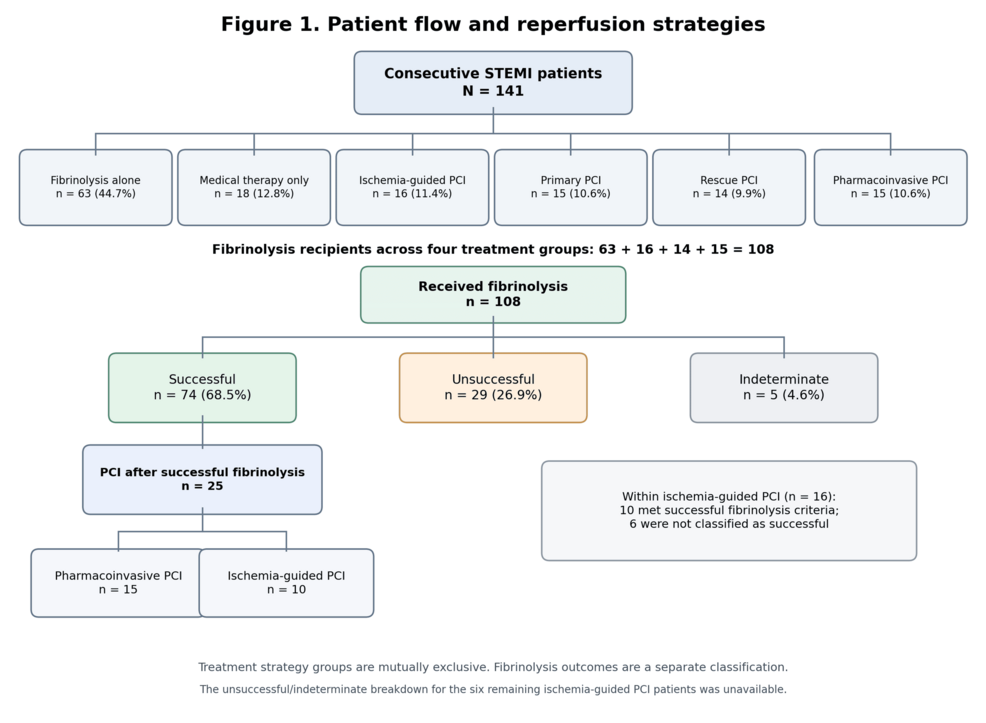
Streptokinase served as the fibrinolytic agent administered intravenously at 1.5 million international units over 60 minutes. Among 108 patients receiving fibrinolysis, 105 had complete timing documentation for analysis. Of those, 65 patients waited more than 30 minutes after their diagnostic ECG to receive the drug, with a median ECG-to-fibrinolysis interval of 60 minutes. Successful fibrinolysis, defined as at least a 50 percent reduction in ST-segment elevation, was documented in 68.5 percent of treated patients.
Patients underwent various reperfusion pathways depending on clinical indications and resource availability:
- Fibrinolysis only: 63 patients (44.7%)
- Ischemia-guided PCI: 16 patients
- Primary PCI: 15 patients
- Rescue PCI: 14 patients
- Pharmacoinvasive PCI: 15 patients
Total Ischemic Time Reaches Median of 225 Minutes
Total ischemic time, measured from symptom onset to initial fibrinolytic administration or primary PCI guidewire crossing, reached a median of 225 minutes among 120 evaluable patients. Eighteen patients who received no reperfusion therapy and three patients with incomplete timing records were excluded from this specific metric.
For the 60 patients who ultimately underwent percutaneous coronary intervention across all strategies, the pooled median diagnostic ECG-to-PCI interval was 16.00 hours. Strategy-specific medians varied widely: primary PCI required a median of 1.60 hours, rescue PCI took 12.75 hours, pharmacoinvasive PCI required 18.61 hours, and ischemia-guided PCI reached a median of 61.85 hours.
Frequently Asked Questions About the Santiago de Cuba STEMI Study
What was the primary reperfusion strategy used at Saturnino Lora Provincial Hospital?
Fibrinolytic therapy without immediate coronary intervention was the most frequent strategy, administered to 63 of the 141 patients, due to limited 24-hour catheterization laboratory availability and intermittent procedural supply shortages.
How many patients received primary percutaneous coronary intervention?
Primary PCI was performed in 15 patients.
What percentage of patients achieved successful fibrinolysis?
Out of 108 patients treated with fibrinolytic therapy, 74 patients, or 68.5 percent, met the criteria for successful reperfusion based on follow-up electrocardiography.
Keep reading