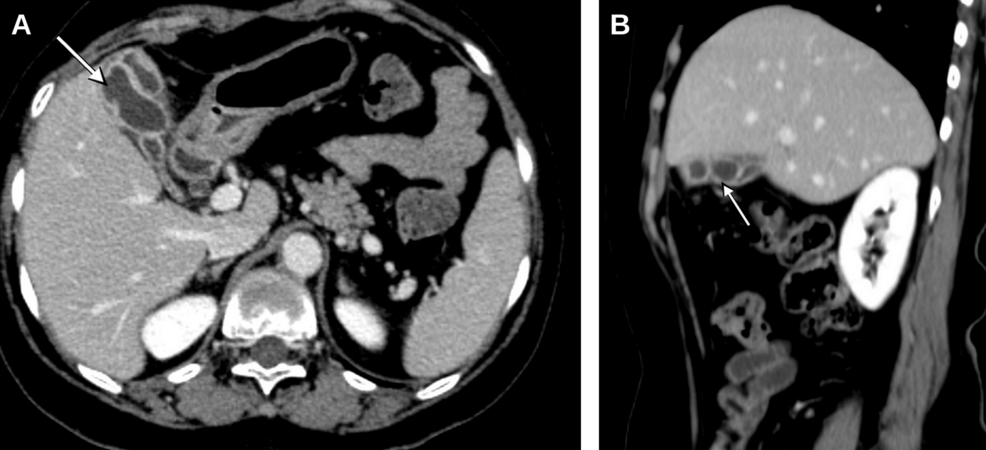
Xanthogranulomatous cholecystitis mimics gallbladder carcinoma, leading doctors to mistake dense tissue adhesions for invasive malignancy during surgery, Cureus reported.
The case involved a 78-year-old woman who sought treatment for right upper-quadrant pain lasting one month. She had previously undergone endoscopic retrograde cholangiopancreatography and common bile duct stenting for choledocholithiasis at another facility.
Contrast-enhanced computed tomography showed acute cholecystitis with a thick-walled, septated gallbladder. Scans revealed pericholecystic changes suggesting a possible contained perforation, but doctors found no discrete mass, hepatic invasion, or regional lymphadenopathy.
Goodman and Ishak first characterized xanthogranulomatous cholecystitis as a distinct clinicopathological entity in 1981. Reported prevalence ranges from under 1% to 8.8% of cholecystectomy specimens, with the highest frequencies documented in South Asia.
Dense Adhesions Confuse Surgical Team
Surgeons performed an open cholecystectomy through a right Kocher’s subcostal incision under general anesthesia. Intraoperative inspection revealed dense adhesions between the gallbladder, omentum, and transverse colon.
These severe adhesions complicated the dissection and initially raised strong concern for a locally invasive gallbladder carcinoma. Given the patient’s age and medical history, the surgical team opted for careful adhesiolysis rather than an extended radical resection.
Admission laboratory results showed a hemoglobin level of 12.8 g/dL and a total leukocyte count of 5,920 per cubic millimeter. Total bilirubin measured 0.70 mg/dL, while direct bilirubin registered 0.60 mg/dL.
| Test | Result | Reference Range |
|---|---|---|
| Hemoglobin | 12.8 g/dL | 12.0–15.0 g/dL |
| Total Bilirubin | 0.70 mg/dL | 0.3–1.2 mg/dL |
| Direct Bilirubin | 0.60 mg/dL | 0.0–0.3 mg/dL |
| Alkaline Phosphatase | 128 U/L | 40–129 U/L |
Histopathology Confirms Benign Inflammatory Condition
Gross examination of the resected specimen showed a thick-walled and fibrotic gallbladder. Histopathological analysis confirmed sheets of lipid-laden foamy histiocytes, multinucleated giant cells, and dense collagenous fibrosis.
Tests showed no evidence of dysplasia or invasive carcinoma within the tissue samples. The patient recovered uneventfully following the operation.
She was discharged on her seventh postoperative day taking ursodeoxycholic acid and supportive medication. At her two-month follow-up visit, she remained completely asymptomatic with normalized liver function tests.
Diagnostic Queries on Gallbladder Pathology
How do doctors differentiate the disease from cancer?
Cross-sectional imaging features favoring xanthogranulomatous cholecystitis include diffuse wall thickening, intramural hypoattenuating nodules, and an intact mucosal line. However, definitive diagnosis relies heavily on postoperative histopathological examination of the resected specimen.
At the two-month follow-up, total bilirubin dropped to 0.3 mg/dL, direct bilirubin reached 0.1 mg/dL, and alkaline phosphatase measured 48 U/L.
Keep reading