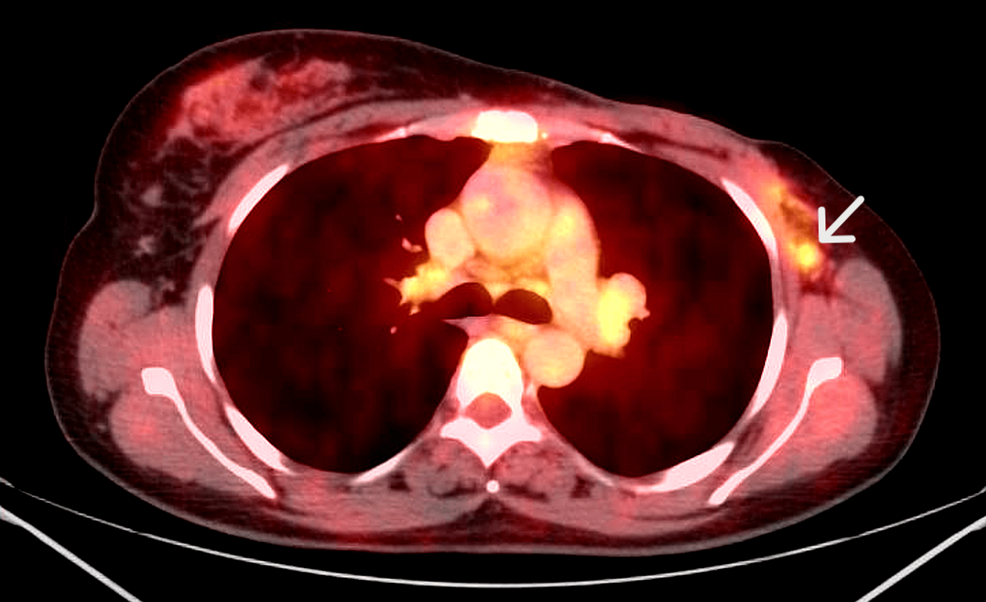
A 46-year-old female patient with invasive ductal carcinoma of the left breast underwent a completion axillary lymph node dissection (cALND) after presenting with bulky residual axillary nodes two months following a modified radical mastectomy (MRM), cureus.com reported.
The patient, whose cancer was biopsy-proven as estrogen receptor (ER)- and progesterone receptor (PR)-negative and human epidermal growth factor receptor 2 (HER2)-positive, had previously undergone an MRM at an outside center for cT3N1Mx disease.
Surgeons Perform cALND After PET-CT Scan Reveals Metastasis
A PET-CT scan revealed nodes that were metabolically active and suspicious for metastasis.
Following a multidisciplinary tumor board discussion, surgeons performed the cALND. The procedure yielded six lymph nodes, two of which were found to be metastatic. The patient’s postoperative course was uneventful, allowing her to proceed to systemic therapy.
Management of Residual Nodal Disease
The case highlights a management challenge regarding residual axillary disease following an incomplete axillary lymph node dissection. While some literature suggests that systemic therapy is the optimum approach for such patients—providing comparable overall survival and local recurrence rates—cALND is not routinely described in the literature for this scenario.
The report suggests that the decision for surgical clearance may be justified in cases of bulky disease to ensure local control and accurate staging. Conversely, for limited residual disease, systemic therapy combined with regional nodal irradiation may achieve similar local control while reducing morbidity. In this specific instance, the decision to perform cALND was driven by the patient’s young age and the significant burden of the residual nodal disease.