Clinical Hemorrhage Following Percutaneous Nephrostomy Tube Removal
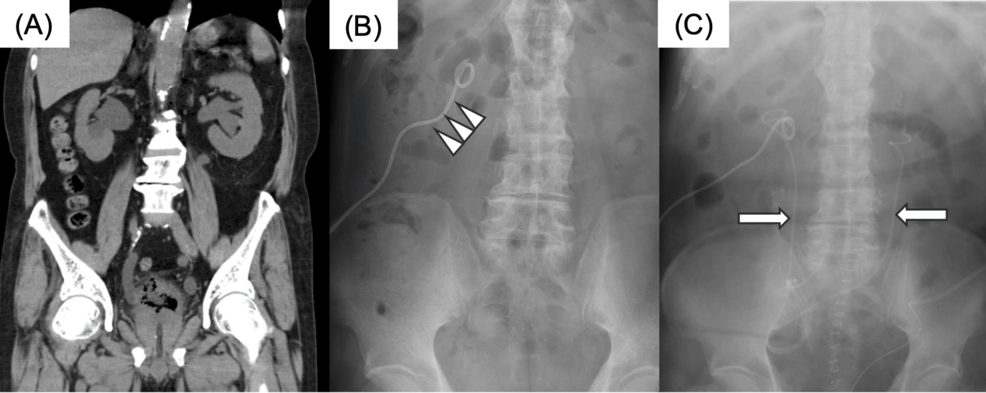
A 76-year-old man experienced substantial bleeding immediately after the removal of a percutaneous nephrostomy tube, as reported by cureus.com. The patient, who had muscle-invasive bladder cancer and bilateral hydronephrosis, underwent right-sided percutaneous nephrostomy using an 8.3-Fr JINRO nephrostomy catheter from Boston Scientific prior to radical cystectomy and ileal conduit urinary diversion.
Patient presents with gross hematuria and grade 3 urothelial carcinoma
The patient presented with asymptomatic gross hematuria, a serum creatinine level of 1.41 mg/dL, and a hemoglobin level of 12.7 g/dL. Magnetic resonance imaging indicated cT3a bladder cancer, while computed tomography confirmed cN0M0 disease with bilateral hydronephrosis. Following transurethral resection of the bladder tumor, which revealed grade 3 urothelial carcinoma invading the muscularis propria, the patient developed right obstructive pyelonephritis. Pathological examination used the 1973 World Health Organization grading system and noted the cancer was at least pT2 according to the TNM classification. This prompted the placement of the right percutaneous nephrostomy catheter under ultrasound and fluoroscopic guidance without Doppler imaging. A small amount of bleeding was observed through the puncture needle during access. Five days later, the patient underwent a radical cystectomy, pelvic lymph node dissection, and ileal conduit urinary diversion during a 261-minute procedure with an estimated blood loss of 610 mL, according to cureus.com.
Nephrostomy tube removal triggers substantial bleeding and blood pressure drop
The nephrostomy tube was clamped after cystectomy and removed on postoperative day 5, which was 10 days after its initial placement. Immediately upon removal, substantial bleeding erupted from the nephrostomy tract along with bloody output and clots through the ileal conduit. Although the patient’s blood pressure dropped from 159/75 mmHg to 124/65 mmHg and his heart rate rose from 82 to 96 beats per minute, he remained hemodynamically stable while appearing pale. His hemoglobin decreased from a postoperative level of 10.4 g/dL to a nadir of 9.4 g/dL. Medical staff inserted a Foley catheter into the ileal conduit and inflated the balloon with 60 mL to temporarily occlude the outlet.
Alternative Presentation of Vascular Complications
In a separate case reported by pmc.ncbi.nlm.nih.gov, an 85-year-old female patient experienced life-threatening pulsatile bleeding immediately upon the insertion of a nephrostomy tube for massive hydronephrosis caused by a papillary mass in the right ureteral ostium. A subsequent computed tomography angiography and renal arteriography revealed active bleeding from the main and unique right renal artery, requiring prompt endovascular embolization with a 2.4F coaxial Direxion microcatheter from Boston Scientific. The arteriography used a 5F nonhydrophilic cobra catheter from Cordis. That patient was later diagnosed with high-grade pTa transitional cell carcinoma following transurethral resection of the bladder and subsequently underwent a right nephroureterectomy, contrasting with the bleeding complications observed during tube removal in the male patient described by cureus.com.
Frequently Asked Questions
What caused the bleeding after nephrostomy tube removal in the primary case?
The patient experienced substantial bleeding from the nephrostomy tract and ileal conduit immediately following the removal of the catheter, with imaging identifying a hematoma within the right renal pelvis.
How did the clinical presentation differ in the comparative case?
As detailed by pmc.ncbi.nlm.nih.gov, an 85-year-old female patient suffered life-threatening arterial bleeding immediately upon nephrostomy tube insertion rather than removal, which necessitated immediate renal angiography and emergency endovascular embolization.
Worth a look