Non-bacterial thrombotic endocarditis linked to cholangiocarcinoma caused a fatal coronary embolism in a 44-year-old South African woman receiving rivaroxaban, Cureus reported. The case documents the first known instance where an initial presentation of cardiogenic shock led directly to diagnosing both conditions through autopsy findings.
Emergency Presentation of ST-Elevation Myocardial Infarction
Emergency medical services brought the patient to the hospital thirty minutes after she reported typical chest pain. Initial vital signs recorded a pulse of 56 beats per minute, a blood pressure of 77 over 31 millimeters of mercury, and an oxygen saturation of 97 percent on room air.
Medical history included human immunodeficiency virus infection with an undetectable viral load while taking emtricitabine, tenofovir, and dolutegravir. Two months prior to admission, clinicians started her on rivaroxaban 20 milligrams daily for a pulmonary embolism stemming from deep-vein thrombosis after a long-haul flight.
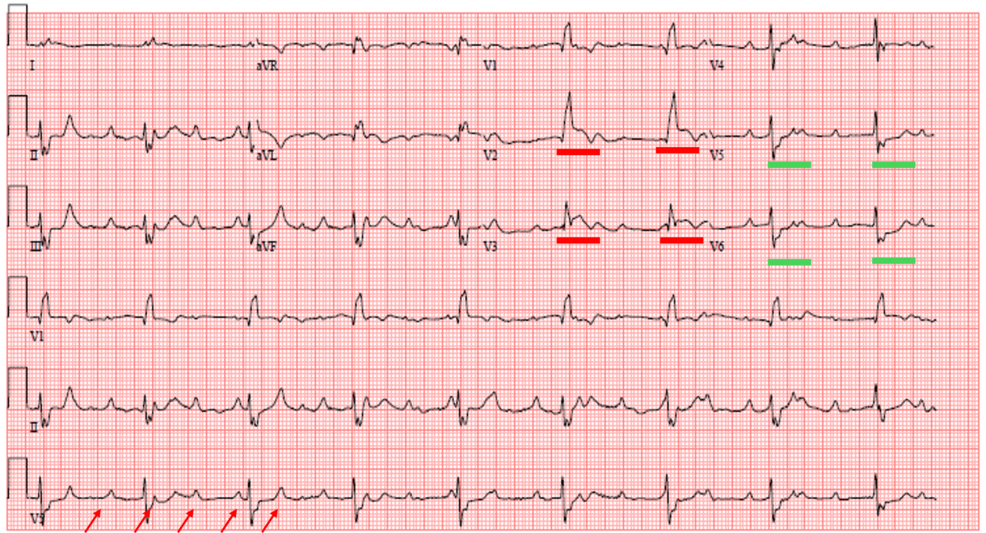
The electrocardiogram in the emergency department demonstrated complete atrioventricular block with an infra-Hisian escape rhythm at 52 beats per minute. ST-segment elevation appeared in leads I, aVL, and V2 through V3, alongside ST-segment depression in V5 through V6. Arterial blood gas analysis showed a pH of 7.05, a partial pressure of carbon dioxide of 16 millimeters of mercury, bicarbonate at 4 milliequivalents per liter, and lactate at 20 millimoles per liter. High-sensitivity troponin T was elevated at 132 nanograms per liter.
Point-of-Care Echocardiography Findings
An atypical clinical presentation prompted point-of-care transthoracic echocardiography to rule out aortic dissection. The imaging revealed extensive apical akinesia, marked thickening of both the mitral and aortic valves, and a mobile echodensity attached to the atrial side of the anterior mitral leaflet consistent with vegetation. Visual assessment also showed severe, central mitral regurgitation.
Medical staff initially suspected infective endocarditis complicated by coronary and left-lower-limb embolization. Despite prompt treatment, the patient’s condition deteriorated rapidly into severe bradycardia. Non-invasive transcutaneous pacing achieved electrical capture but failed to restore the arterial pulse.
Autopsy Reveals Thrombi in Small Myocardial Vessels
Autopsy examination revealed a normal heart weight and completely unremarkable epicardial coronary arteries upon dissection. A granular thrombus-like material indicative of vegetations appeared on the leaflets of both the mitral and aortic valves. Histopathological examination of myocardial tissue showed no myocyte necrosis or hemorrhagic changes, which researchers attribute to the short interval of under four hours between symptom onset and death.
Numerous thrombi were identified within the small-caliber blood vessels of the myocardium. Microscopic analysis of the valvular vegetations showed acellular material consisting essentially of fibrinoid material paired with scattered blood elements adherent to the valve leaflets. Abdominal examination uncovered multiple firm hepatic nodules, with the largest measuring 16 centimeters in diameter.
Histopathology of the liver nodules displayed glandular structures lined by cells with marked cytonuclear atypia extending along and infiltrating the bile duct. Immunohistochemistry demonstrated cytoplasmic cytokeratin 7 positivity in the tumor cells, confirming cholangiocarcinoma. Multiple whitish, firm nodules identified on the peritoneum revealed similar histopathological findings consistent with peritoneal carcinomatosis.
Divergent Responses to Anticoagulation Regimes
Non-bacterial thrombotic endocarditis involves sterile fibrin and platelet deposition on cardiac valves without active infection, with advanced malignancy serving as the leading cause. Clinically silent until systemic embolization occurs, it is frequently misdiagnosed as infective endocarditis due to overlapping fevers or elevated inflammatory markers. Management typically requires therapeutic anticoagulation combined with treatment for the underlying cancer.
Medical literature contains only ten reported cases of cholangiocarcinoma-associated non-bacterial thrombotic endocarditis, with only one involving coronary embolism. While low-molecular-weight or unfractionated heparin is the preferred anticoagulant regimen to minimize embolic risk, the patient in this case received rivaroxaban. Treatment failures with vitamin K antagonists and direct oral anticoagulants are documented in such cases, and the procoagulant state induced by human immunodeficiency virus infection may have further contributed to the direct oral anticoagulant’s ineffectiveness.
Questions About Non-Bacterial Thrombotic Endocarditis
What is non-bacterial thrombotic endocarditis?
Non-bacterial thrombotic endocarditis is a rare condition characterized by sterile fibrin and platelet deposits forming vegetations on cardiac valves without any active infection. It is most commonly triggered by advanced malignancies, which create a hypercoagulable state.
Why did the patient experience a heart attack without blocked major coronary arteries?
Autopsy results showed normal epicardial coronary arteries without major obstruction, but multiple thrombi were discovered within the small-caliber blood vessels of the myocardium. Researchers concluded that friable vegetations from the heart valves traveled into the microcirculation as coronary emboli.
How does HIV infection affect thrombosis risk?
Human immunodeficiency virus infection is a well-established risk factor that increases venous thromboembolism risk two- to ten-fold. This elevated risk stems from endothelial dysfunction, platelet activation, and coagulation activation, even when the patient maintains an undetectable viral load.
Keep reading