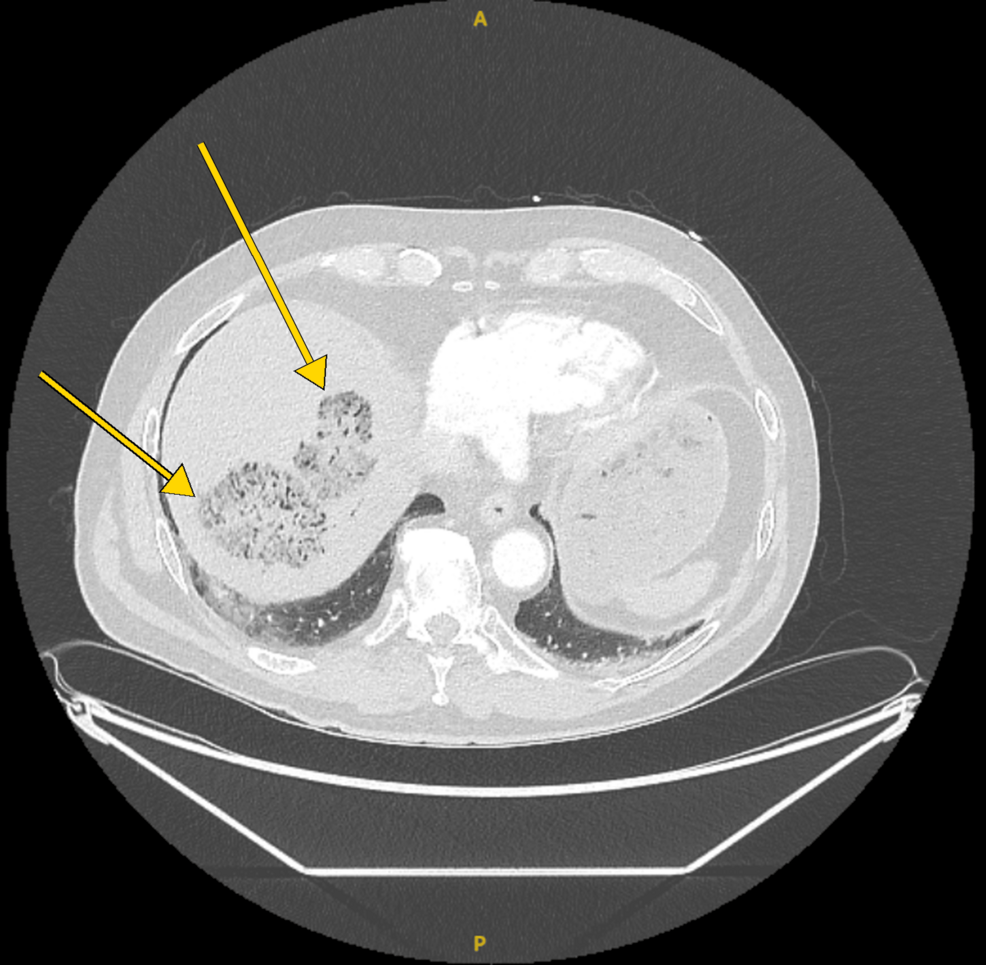
Clostridium perfringens septicemia carries a mortality rate of at least 60%, with deaths occurring within hours of hospital presentation when massive intravascular hemolysis develops. A man died after entering an emergency department with this fulminant infection, Cureus reported. The case highlights a critical diagnostic gap where imaging may appear normal while the patient rapidly decompensates.
Patient dies from emphysematous hepatic abscesses
The patient presented with acute epigastric pain radiating to the back, fever, and a rigid abdomen. Initial blood work revealed a deep high anion gap metabolic acidosis with a lactate level of 13.7 mmol/L and hyperkalemia. A triple-phase CT scan identified two air-filled nodular zones in the liver, measuring 6.7 cm and 5 cm, which were consistent with emphysematous hepatic abscesses.
Despite the liver findings, the patient’s gallbladder appeared normal on the initial CT, showing no wall thickening or pericholecystic fluid. He suffered a cardiac arrest and died shortly after arrival. Post-mortem examination later identified the gallbladder as the primary source of the infection, showing that structural signs of cholecystitis may not have time to develop in such rapid cases.
Did you know? Clostridium perfringens produces an alpha-toxin (phospholipase C) that destroys red blood cell membranes, leading to the massive intravascular hemolysis seen in these fatal cases.
Hemolysis vs. recovery outcomes
The clinical trajectory of C. perfringens varies sharply based on the presence of hemolysis and the speed of source control. While the patient in the Cureus report died in just over two hours, other clinical data shows different outcomes when interventions are successful.
| Clinical Feature | Fulminant Case (Cureus) | Recovered Case (Clin Ultrasound) |
|---|---|---|
| Primary Outcome | Death (2h 11m after admission) | Successful Recovery |
| Imaging/Monitoring | Initial CT / Post-mortem | Serial Ultrasonography |
| Source Control | Precluded by instability | Monitored via ultrasound |
Clin Ultrasound reported a separate instance of hepatic gas gangrene caused by C. perfringens where the patient achieved a successful recovery.
The failure of microbiological confirmation
A critical challenge in treating clostridial sepsis is that the bacteria often outpace the lab. In the reported fatality, blood cultures only flagged positive 9.6 hours after collection—long after the patient had died. Post-mortem anaerobic cultures of the liver were negative despite the presence of gram-positive rods on direct microscopy.
Because of this lag, the Cureus report suggests that management must be driven by radiological clues—specifically the combination of gas-forming hepatic lesions and unexplained hemolysis—rather than waiting for microbiological confirmation.
C. perfringens diagnostic questions
Can a normal gallbladder scan rule out the infection source?
No. As shown in the Cureus case, the gallbladder appeared normal on CT but was later confirmed as the primary source of infection via post-mortem biopsy.
Why is the 30-day mortality higher for cancer patients?
Cureus notes that 30-day mortality for C. perfringens bacteremia is roughly 30%, but this figure rises to 43% in patients with cancer, as immunosuppression is a consistent comorbidity.
Which antibiotics provide antitoxin effects?
Whether the addition of clindamycin or earlier empirical hemostatic resuscitation—such as the immediate administration of plasma and fibrinogen—would have altered the outcome for this patient remains unknown.