A 21-Year-Old Man Develops Propofol Infusion Syndrome Following Four Days of Sedation
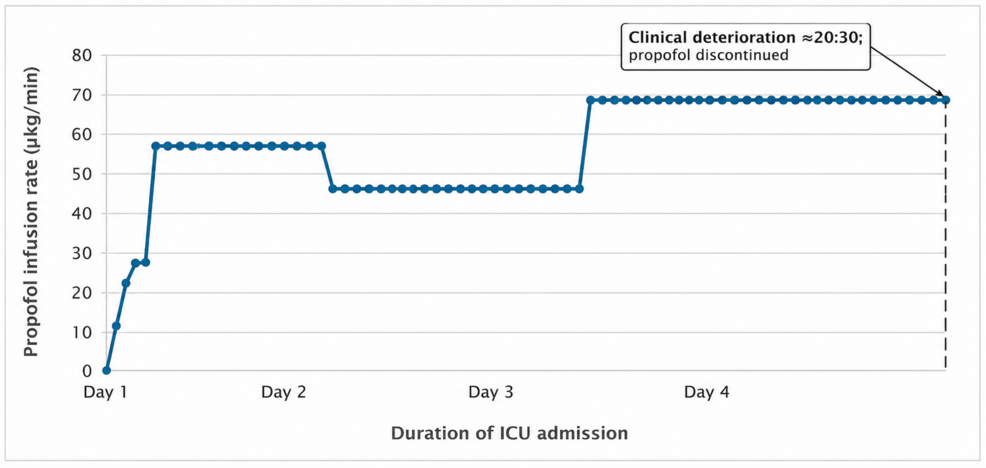
A 21-year-old man with a previous traumatic brain injury developed severe propofol infusion syndrome, or PRIS, after receiving four days of mechanical ventilation and continuous sedation for refractory status epilepticus. The patient experienced acute cardiovascular collapse, profound rhabdomyolysis, and severe metabolic derangement. The infusion rate culminated in a final dose of 68.5 micrograms per kilogram per minute for the 35 hours preceding his clinical decline on intensive care unit day four.
Rapid Clinical Deterioration and Multi-Organ Failure on Unit Day Four
Laboratory evaluations revealed blood tests showing an initial creatine kinase measurement of 62,600 International Units per liter when his condition worsened, which later reached its highest point of 931,000 International Units per liter by unit day six. Other noted abnormalities included hypertriglyceridemia at 11.5 millimoles per liter, hyperkalemia at 6.7 millimoles per liter, and acute kidney injury with serum creatinine rising sharply from 89 to 497 micromoles per liter. Transthoracic echocardiograms performed at the bedside established generalized left ventricular dysfunction showing an ejection fraction calculated at 20 percent, while sequential ECGs monitored rapid electrical decline that displayed QRS complex widening, T-wave alterations, and a corrected QT duration surpassing 500 milliseconds.
Physicians Stop Sedation to Stabilize Patient Metabolic Function
To combat multi-organ failure, physicians deployed a multimodal critical care strategy. Oral L-carnitine was given via the enteral route at a dose of 500 milligrams three times a day to combat suspected mitochondrial impairment aggravated by concurrent valproate use, while high-dose euglycemic insulin was also administered. Hemodynamic and metabolic stabilization became evident roughly six hours after propofol cessation, allowing the clinical team to avoid extracorporeal membrane oxygenation or plasma exchange.
Recovery
Following initial stabilization, the patient continued to improve over the subsequent two to three days despite his creatine kinase continuing to rise toward its peak on ICU day six.
Clinical Parameters at Admission and Acute Deterioration
At ICU admission, the patient exhibited an arterial blood gas pH of 7.25, an arterial bicarbonate level of 21 millimoles per liter, an anion gap of 16 millimoles per liter, and a serum potassium level of 3.9 millimoles per liter, alongside a serum lactate level of 5.4 millimoles per liter. By the day four deterioration, the arterial blood gas pH dropped to 7.17, arterial bicarbonate fell to 12 millimoles per liter, the anion gap widened to 26 millimoles per liter, serum potassium climbed to 6.7 millimoles per liter, and serum lactate increased to 10.3 millimoles per liter.
Frequently Asked Questions About the 21-Year-Old Patient’s Case
What triggered the propofol infusion syndrome in this patient?
The syndrome developed after four days of continuous propofol infusion for refractory status epilepticus, following an unwitnessed fall and hospitalization for a patient with a previous traumatic brain injury.
What peak level did the patient’s creatine kinase reach?
The creatine kinase level initially measured 62,600 International Units per liter at the time of acute deterioration on ICU day four and ultimately peaked at 931,000 International Units per liter on unit day six.
How was the severe metabolic derangement managed?
Physicians deployed a multimodal critical care strategy that included aggressive hemodynamic support with noradrenaline, adrenaline, dobutamine, and vasopressin, as well as the administration of enteral L-carnitine and high-dose euglycemic insulin.
When did hemodynamic improvement become apparent after propofol cessation?
Hemodynamic and metabolic improvement became apparent approximately six hours after propofol cessation and the initiation of multimodal supportive therapy.