Mediastinal Mass Discovery
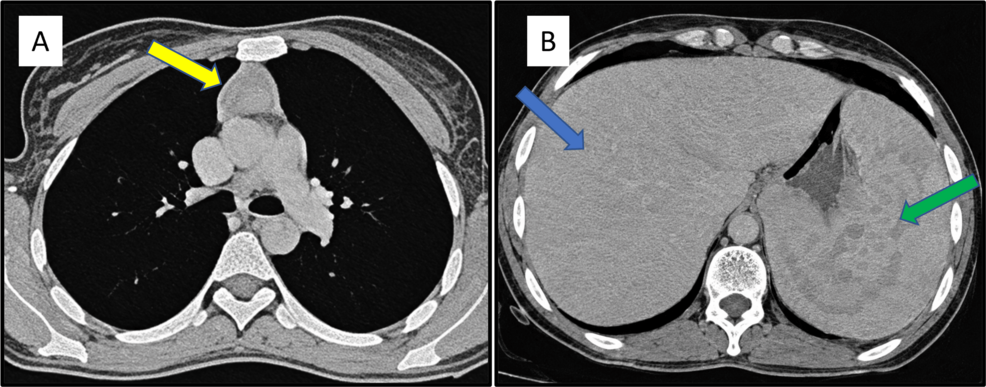
A 28-year-old deaf-mute woman presented with chronic abdominal pain and pancytopenia before a thoraco-abdomino-pelvic CT scan revealed a 32 by 27 millimeter anterior mediastinal mass, Cureus reported. Laboratory tests detailed normochromic normocytic non-regenerative anemia with a hemoglobin level of 9.3 grams per deciliter, neutropenia at 241 cells per cubic millimeter, and a platelet count of 106,000 per cubic millimeter alongside homogeneous hepatosplenomegaly. Plasma protein electrophoresis showed polyclonal hypergammaglobulinemia, while bone marrow examination yielded normal findings and negative viral serologies.
Vascular Thymectomy Results
Surgeons performed a right video-assisted thoracoscopic thymectomy without administering any postoperative immunosuppressive therapy, according to Cureus. Histological examination identified a well-encapsulated type B2 thymoma classified as Masaoka-Koga stage I. Subsequent clinical follow-up showed the patient’s blood counts returning toward reference ranges by three months, with hemoglobin rising to 11.6 grams per deciliter, neutrophils reaching 1,279 cells per cubic millimeter, and platelets climbing to 146,000 per cubic millimeter.
Immunological Recovery Comparisons
Published literature typically indicates that thymectomy alone fails to resolve thymoma-associated pancytopenia, requiring adjunct cyclosporine-based regimens for hematologic remission. Case reviews by Ghazizadeh and other researchers previously concluded that surgical resection rarely suffices for patients suffering from severe aplastic anemia tied to thymic epithelial tumors. Conversely, the successful recovery observed in this patient following surgery alone points toward a peripheral immune destruction mechanism driven by a small, stage I encapsulated tumor rather than established central bone marrow failure.
Patient Medical Inquiries
What caused the patient’s low blood counts?
Cureus reported that the pancytopenia stemmed from thymoma-induced immune dysregulation, where abnormal T lymphocytes targeted blood cells while leaving the bone marrow reactive and normal.
Why did this case differ from prior medical literature?
Unlike previous published cases where patients required cyclosporine or corticosteroids after surgery, this patient achieved complete blood count normalization at two years through thymectomy alone.
How was the mediastinal tumor removed?
Surgeons utilized a right video-assisted thoracoscopic procedure to completely extract the 32 by 27 millimeter encapsulated type B2 thymoma without intraoperative complications.