An 86-year-old woman developed embolic injury across five vascular beds over a two-week hospital stay before medical teams identified the root cause as a cardiac myxoma, Cureus reported.
Primary cardiac tumors occur rarely, showing a prevalence between 0.001% and 0.03% in autopsy series. Cardiac myxomas rank as the second most frequent benign primary cardiac tumor in adults behind papillary fibroelastomas, typically arising in the left atrium from the interatrial septum near the fossa ovalis.
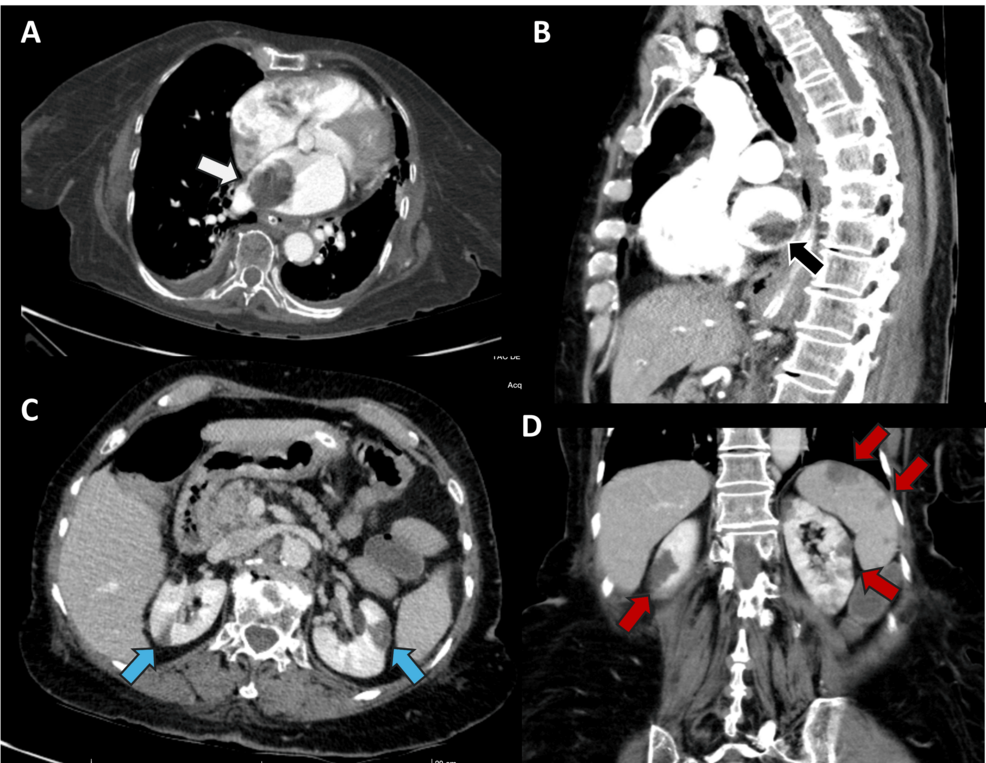
The patient presented to the emergency department following a syncopal fall and a four-month history of a constitutional syndrome that included anorexia, asthenia, five kilograms of weight loss, hypogastric pain, and hematochezia. Contrast-enhanced computed tomography of the chest and abdomen revealed an oval intraluminal mass measuring 45 by 30 millimeters in the left atrium with lobulated contours and heterogeneous enhancement.
Medical staff initially interpreted the mass as an intracavitary thrombus given the patient’s history of arterial hypertension, rheumatoid arthritis, electrocardiographically documented atrial fibrillation, and left atrial enlargement. Initial imaging also showed wedge-shaped hypodense areas in both kidneys and the spleen consistent with established infarcts, prompting the internal medicine team to initiate unfractionated heparin anticoagulation.
Multiterritorial Embolic Injury
Before clinicians could perform an echocardiogram, the patient suffered sudden left hemiparesis, mild dysarthria, and left facial palsy. Brain magnetic resonance imaging demonstrated multiple acute lesions with restricted diffusion across both frontoparietal regions, the right occipital region, and periatrial areas.
Transthoracic echocardiography subsequently revealed a mobile, heterogeneous 50 by 32 millimeter mass in the left atrium attached to the interatrial septum, shifting the leading diagnostic consideration to myxoma. Simultaneously, the patient lost bilateral pulses from the popliteal level down with cold extremities, sensory deficits, and painful compartments.
Computed tomography angiography of the lower limbs confirmed acute embolic occlusion of the P2-P3 popliteal segments and tibioperoneal trunks bilaterally. Abdominal imaging simultaneously displayed segmental hypodensity with absent mucosal enhancement of the cecum and distal ileum, pointing to ischemia in the ileocolic territory alongside the earlier renal and splenic infarcts.
Surgical Interventions and Pathology
Exploratory laparotomy uncovered turbid peritoneal fluid, dilated hypoperfused small bowel loops, and transmural necrosis of the cecum and ileocecal valve with thrombosed ileocolic vessels. Surgeons performed a partial right colectomy with a distal ileostomy and carried out bilateral lower limb embolectomies immediately afterward.
The retrieved material appeared yellowish, friable, and gelatinous, differing from conventional organized thrombus. Histopathologic examination of this material confirmed myxomatous tissue, and distal pulses returned to both lower extremities.
The patient underwent a median sternotomy with cardiopulmonary bypass on the following day for resection of the left atrial mass. Intraoperative findings showed a morular, gelatinous, and hemorrhagic tumor with a pedicle located on the inferior atrial wall below the ostia of the right pulmonary veins.
Postoperative Complications
Complete excision of the mass was achieved with curettage of the implantation site, and histopathologic examination confirmed cardiac myxoma containing spindle and stellate cells within a loose mucopolysaccharide-rich myxoid matrix alongside neovascularization and hemorrhagic foci. Immunohistochemistry testing returned positive results for calretinin and CD31.
Subsequent to heart manipulation, another embolic episode struck the patient’s right leg, necessitating a surgical redo involving segmental popliteal resection paired with an end-to-end anastomosis. Follow-up abdominal computed tomography days later revealed extensive new small bowel ischemia involving the jejunum and ileum, peritonitis, and free intraperitoneal air.
An emergency laparotomy confirmed four-quadrant fecal peritonitis secondary to anastomotic dehiscence. Despite maximal intensive care support featuring dual vasopressor therapy, the patient developed progressive oliguria and multiorgan hypoperfusion, dying two weeks after admission.
Clinical Insights on Misdiagnosis
Retrospective evaluation by a thoracic imaging radiologist indicated that several computed tomography features actually favored myxoma over thrombus from the outset. The mass exhibited oval and lobulated contours, unequivocal heterogeneous enhancement, a non-appendage location related to the interatrial septum, and a size exceeding that typical of left atrial thrombi.
Published literature establishes that size, site of origin, shape, mobility, and prolapse serve as more discriminating factors than attenuation when differentiating myxoma from thrombus. First-pass arterial acquisitions can occur too early to capture tumor enhancement, making the enhancement visible on the patient’s arterial-phase scan a notable clue.
While both computed tomography and echocardiography pointed toward an attachment on the interatrial septum, the actual surgical site was found to be the inferior atrial wall situated beneath the right pulmonary vein ostia. Large, lobulated, and mobile masses in broad contact with the septum can obscure the true attachment site on imaging modalities.
Common Questions Regarding Cardiac Myxoma
What are the primary symptoms of cardiac myxoma?
Cardiac myxoma behavior typically involves a clinical triad of intracavitary obstruction, constitutional symptoms like weight loss and fatigue, and systemic embolization affecting 20% to 45% of patients.
Why are left atrial myxomas frequently mistaken for thrombi?
Patients with atrial fibrillation and left atrial enlargement frequently present with mural thrombi, leading clinicians to suspect blood clots when an intracavitary filling defect appears alongside visceral infarcts.
What imaging features help distinguish myxoma from thrombus?
Myxomas tend to be larger, lobulated, located outside the atrial appendage near the septum, and capable of heterogeneous enhancement, whereas thrombi are typically smaller, avascular, and non-enhancing.
How does multiterritorial embolization occur?
Tumor fragments or surface material can detach from the primary cardiac mass and travel through arterial circulation to occlude vessels in the brain, kidneys, spleen, mesenteric territory, and lower limbs simultaneously.
Worth a look