Sudden Left-Sided Weakness Brought a 22-Year-Old Man to the Hospital
A 22-year-old man from Senegal who had lived in the United Kingdom for several years arrived by ambulance at a hospital with sudden-onset left-sided weakness and numbness that started two days earlier. The patient also experienced difficulty speaking, a headache, and poor balance, recording a National Institutes of Health Stroke Scale score of 5 on admission that improved to 3 after 24 hours. While previously well with no major cardiovascular risk factors, he reported intermittent terminal hematuria over the preceding few months and a history of frequently swimming in freshwater lakes while residing in Senegal.
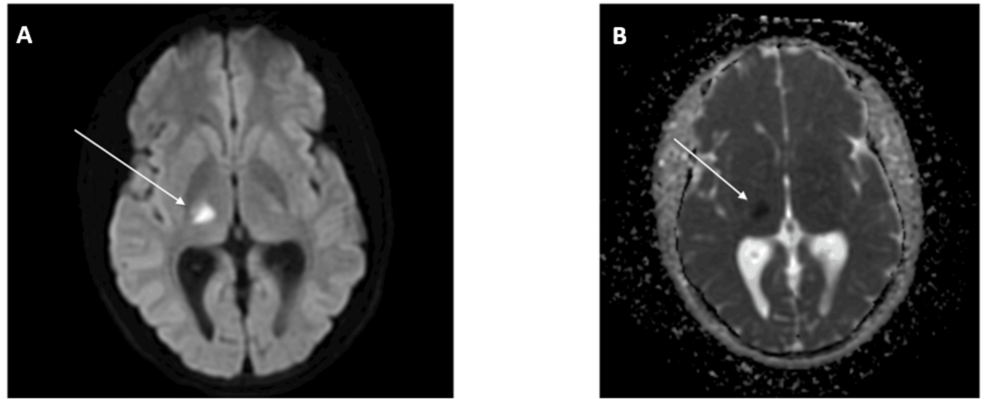
Non-contrast head CT showed a subtle hypodensity involving the right thalamus and posterior limb of the internal capsule. Magnetic resonance imaging confirmed an acute infarct of the right posterior thalamus with true diffusion restriction, while CT angiography revealed multifocal intracranial luminal narrowing affecting the right terminal internal carotid artery, distal right middle cerebral artery, right P2 segment, and proximal right superior cerebellar artery. A comprehensive autoimmune and vasculitis screen returned entirely normal or negative results, though peripheral eosinophilia showed an elevated white blood cell differential of 1.4 ×10⁹/L.
Did you know? Schistosomiasis affects more than 200 million people worldwide, with the World Health Organization estimating that 253.7 million people required preventive treatment globally.
Urine Microscopy and Parasitology Confirm Active Schistosoma haematobium Infection
Urine microscopy revealed the presence of Schistosoma haematobium ova, and serum schistosomal antibody testing via enzyme-linked immunosorbent assay was positive. CT intravenous urography demonstrated calcification of the bladder dome along with an ectopic left kidney lying in the pelvis and splenomegaly measuring 13 centimeters. Flexible cystoscopy identified a classical sandy patch lesion measuring 3 by 2 centimeters on the posterior bladder wall.
Multidisciplinary teams across stroke, infectious diseases, urology, rheumatology, and neuroradiology reviewed the case and recommended prioritizing corticosteroids before administering antiparasitic therapy. Doctors chose this sequence to prevent praziquantel from precipitating a severe, potentially life-threatening inflammatory deterioration in acute neuroschistosomiasis. The patient received an oral prednisolone tapering regimen over six weeks starting at 60 milligrams daily, alongside a single empirical dose of ivermectin to cover potential Strongyloides co-infection while awaiting serology.
Pro Tip: Clinicians evaluating stroke in young patients from endemic regions should maintain a low threshold for considering schistosomiasis, particularly when peripheral eosinophilia or a vasculitic angiographic pattern is present.
Six-Week Follow-Up Reveals Normalised Eosinophil Counts and Functional Recovery
A contrast-enhanced MRI of the brain and whole spine performed before treatment started showed a nodular enhancing lesion in the right thalamus with surrounding edema that had decreased in size and enhancement compared with earlier scans. Follow-up blood tests at six weeks demonstrated that peripheral eosinophilia had normalized to 0.5 ×10⁹/L, and repeat post-treatment urinary microscopy showed no schistosomal ova. A repeat MRI and MRA of the head at six weeks showed no new acute infarct, maturation of the thalamic infarct, and a stable multifocal vasculopathy.
The patient achieved a good functional recovery and remained well with no clinical recurrence over 12 months of follow-up. Medical literature classically associates cerebral neuroschistosomiasis with Schistosoma japonicum, making its presentation here alongside Schistosoma haematobium an unusual manifestation of urinary schistosomiasis presenting as an ischemic stroke.
Doctors administered ivermectin to cover possible Strongyloides co-infection
Why did doctors administer ivermectin before starting antiparasitic therapy?
Physicians administered a single empirical dose of ivermectin alongside the initial corticosteroid regimen to cover possible Strongyloides co-infection, as subsequent immunosuppression carries a recognized risk of triggering life-threatening hyperinfection.
What specific diagnostic findings ruled out a primary systemic autoimmune vasculitis?
Proteinase 3 and myeloperoxidase antibodies were negative on two occasions, while antinuclear antibodies, complement levels, immunoglobulins, serum protein electrophoresis, and an antiphospholipid screen all returned negative or within normal limits.
What imaging evidence confirmed the thalamic infarct?
An axial diffusion-weighted MRI showed an acute infarct in the right posterior thalamus with high signal intensity, while the corresponding apparent diffusion coefficient map confirmed true restricted diffusion with low signal at the same site.
What was the patient’s leukocyte eosinophil count at admission?
The patient presented with a peripheral eosinophil count of 1.4 ×10⁹/L against a normal reference range of 0 to 0.5 ×10⁹/L.
Worth a look