Retrograde Jejunojejunal Intussusception After Bariatric Revision
A 69-year-old woman presented to the Emergency Department at Rambam Health Care Campus with abdominal pain that woke her from sleep and radiated to her back, accompanied by recent diarrhea, Cureus reported. Medical records showed she had undergone a laparoscopic sleeve gastrectomy 10 years prior—losing 20 kg from an initial body mass index of 42 kg/m²—before converting to a Roux-en-Y gastric bypass approximately two years later due to severe reflux symptoms. Laboratory results showed a white blood cell count of 14.5 × 10³/µL, a hemoglobin level of 13.3 g/dL, a lactate concentration of 2.2 mmol/L, and a C-reactive protein level of 0 mg/dL. A plain abdominal radiograph demonstrated air-fluid levels, while a nasogastric tube drained coffee-ground content.
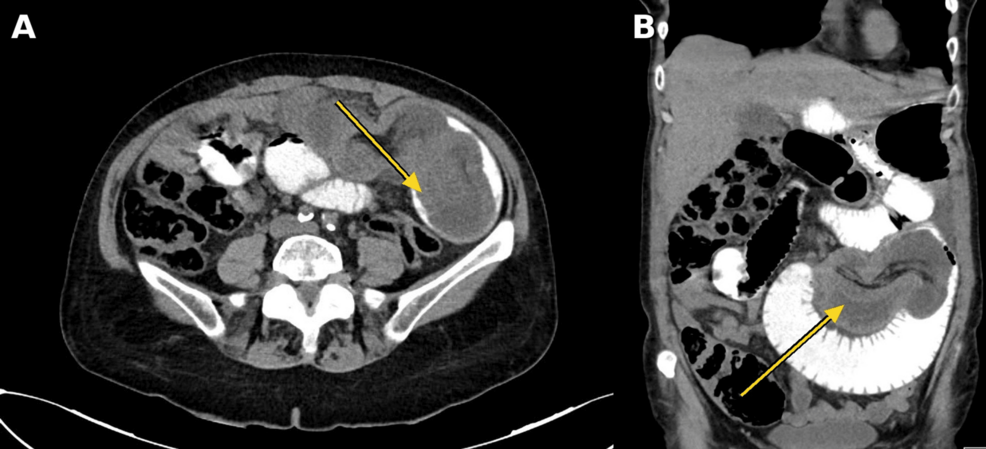
Abdominal computed tomography scans with intravenous and oral contrast revealed dilated proximal small bowel loops up to 5 cm in diameter alongside a suspected intussusception measuring approximately 23 cm in the left upper abdomen involving the jejunojejunal anastomosis. Although diagnostic laparoscopy initially showed a 1 cm perforation of the common channel without peritoneal contamination or enteric leakage, surgeons converted to an exploratory laparotomy because the intussusception could not be reduced laparoscopically. Operative exploration determined that roughly 90 cm of the common channel had telescoped retrogradely into a 30 cm blind segment of the biliopancreatic limb. Surgeons successfully reduced the intussusception, closed the perforation primarily with a 3-0 Vicryl suture, secured the common channel to both the biliopancreatic limb and the mesenteric root, and closed the open Petersen space and jejunojejunal mesenteric defect.
Comparing Surgical Approaches in Bariatric Complications
Historical data from Simper et al. and systematic reviews by Oor et al. previously emphasized high recurrence rates—up to 100%—following simple reduction of intussusception after Roux-en-Y gastric bypass, leading many clinical centers to advocate for segmental resection and revision of the jejunojejunal anastomosis.
The patient recovered without major complications and was discharged home on postoperative day six following an uneventful hospital course. At a two-month follow-up evaluation in the bariatric clinic, she reported no new symptoms, no complaints, and no clinical signs of recurrence. Treating surgical teams recommended annual bariatric clinic evaluations alongside an upper endoscopy scheduled for one year post-discharge to monitor long-term outcomes.
Frequently Asked Questions About Retrograde Jejunojejunal Intussusception
How common is intussusception following a sleeve gastrectomy converted to Roux-en-Y gastric bypass?
Intussusception as a late mechanical complication is generally uncommon in adults, and its occurrence specifically following a conversion from a sleeve gastrectomy to a Roux-en-Y gastric bypass is rarely documented in clinical literature.
What diagnostic imaging is most effective for identifying this condition?
Computed tomography of the abdomen utilizing both intravenous and oral contrast serves as the primary diagnostic modality, reliably demonstrating characteristic bowel-within-bowel configurations and proximal small bowel dilation indicative of mechanical obstruction.
Keep reading