Seventeen-Year-Old Patient Presents With 27-Liter Benign Ovarian Mass
A 17-year-old female patient arrived at an emergency department with a 50-centimeter benign papillary serous cystadenofibroma containing approximately 27 liters of serous fluid. The presentation followed two years of progressive abdominal distension that occurred with minimal associated symptoms. While most pediatric and adolescent ovarian masses are benign, giant epithelial tumors remain rare and often mimic malignant disease. Medical literature generally defines pediatric lesions larger than 15 centimeters as giant cysts, placing this case among the largest benign ovarian tumors reported in adolescents in recent medical literature.
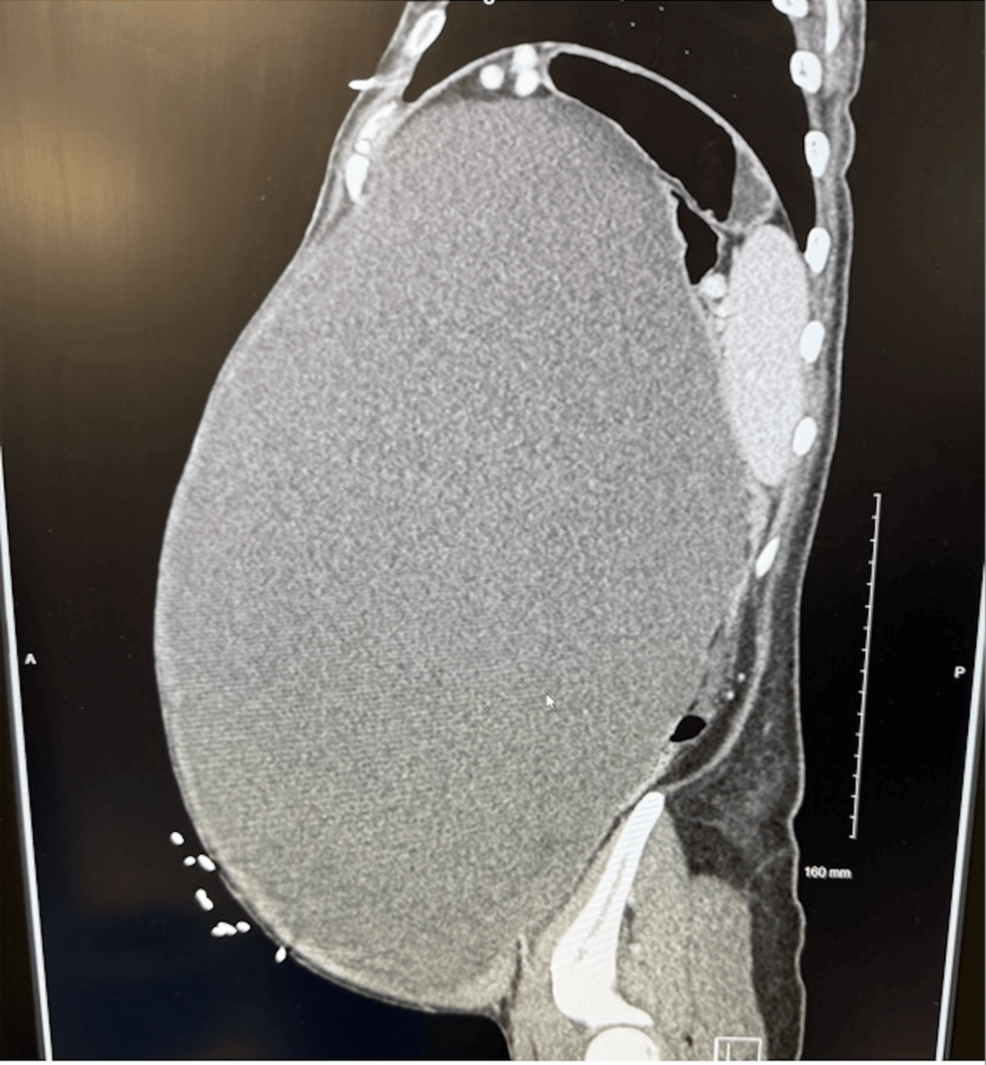
The patient weighed 73.2 kilograms with a body mass index of 27.7 kilograms per meter squared upon presentation. Physical examination revealed temporal wasting and marked abdominal distension without tenderness, guarding, or rebound. Laboratory findings showed a negative serum beta-human chorionic gonadotropin level below 0.60 units per milliliter and an elevated CA-125 level of 120.8 units per milliliter. Computed tomography with intravenous contrast demonstrated a massive cyst replacing most of the peritoneal cavity, extending from the diaphragm to the deep pelvis and measuring approximately 50 by 36 by 26 centimeters.
Surgeons perform exploratory laparotomy to drain massive mass
Obstetrics and gynecology specialists consulted with gynecologic oncology and recommended an open approach because the mass occupied nearly the entire abdominal cavity, which precluded safe laparoscopic entry. The patient underwent an exploratory laparotomy under general anesthesia through a nine-centimeter low vertical midline incision. Surgeons decompressed the large cystic mass using a 14-millimeter suction curette, yielding the 27 liters of serous fluid. Intraoperative assessment revealed that extreme distension and the anatomical location of adnexal structures within the mass made ovarian and fallopian tube conservation impossible, necessitating a right salpingo-oophorectomy.
Estimated blood loss during the procedure totaled 20 milliliters, and the operation proceeded without intraoperative complications. Immediate postoperative physical examination confirmed the complete resolution of the patient’s prior abdominal distension. Histopathologic examination of the excised tissue confirmed a benign papillary serous cystadenofibroma featuring focal calcification, with no evidence of cellular dysplasia or malignancy.
Patient recovers from surgery and experiences asymptomatic bradycardia
During the immediate postoperative recovery period, the patient experienced episodes of asymptomatic bradycardia. A pediatric consultation was obtained, and the treating team attributed these rhythm changes to physiologic adaptations following the removal of the massive tumor and the subsequent relief of vascular compression. Medical staff administered no pharmacologic treatments or procedural interventions for the bradycardia, classifying the event as a Clavien-Dindo Grade I complication. The patient was successfully discharged on postoperative day one following instructions regarding wound care and physical activity restrictions.
| Clinical Metric | Preoperative Measurement | Postoperative Measurement |
|---|---|---|
| Patient Weight | 73.2 kg | 48.8 kg |
| Body Mass Index (BMI) | 27.7 kg/m² | 18.5 kg/m² |
| Abdominal Dimensions | 50 × 36 × 26 cm | Resolved distension |
| Fluid Volume Drained | N/A | 27 Liters |
At the two-week postoperative clinical visit, wound inspection showed an incision that was clean, dry, intact, and well healed. The patient’s total body weight had dropped from 73.2 kilograms preoperatively to 48.8 kilograms postoperatively, reflecting a 24.4-kilogram reduction primarily driven by the evacuation of the cyst fluid and mass. Her body mass index decreased correspondingly from 27.7 to 18.5 kilograms per meter squared. She reported total resolution of her initial symptoms, returned to normal baseline functioning, and presented with no new medical complaints or documented complications.
Frequently Asked Questions About Adolescent Giant Ovarian Cysts
What defines a giant ovarian cyst in pediatric patients?
Medical literature generally classifies any ovarian or adnexal lesion larger than 15 centimeters in diameter as a giant cyst in pediatric and adolescent populations. Some specific case reports apply an even stricter threshold, defining giant tumors as those exceeding 25 centimeters.
Why is CA-125 elevated in benign cystadenofibromas?
CA-125 is less specific for malignancy in premenopausal patients and must be interpreted alongside imaging and other clinical findings.
Why was laparoscopy ruled out for this patient?
Surgeons selected an open exploratory laparotomy via a low vertical midline incision because the massive ovarian cyst occupied the majority of the patient’s abdominal cavity, leaving inadequate working space for safe laparoscopic entry and instrument maneuverability.
What histopathologic features distinguished this tumor?
Histopathologic examination confirmed a benign papillary serous cystadenofibroma consisting of fibrous cyst walls with associated papillary architecture and focal calcification, completely lacking cellular dysplasia or malignant characteristics.
How much weight did the patient lose after surgery?
At the two-week postoperative visit, the patient had lost 24.4 kilograms, dropping from 73.2 kilograms to 48.8 kilograms after the removal of 27 liters of serous fluid and the surrounding cyst wall.