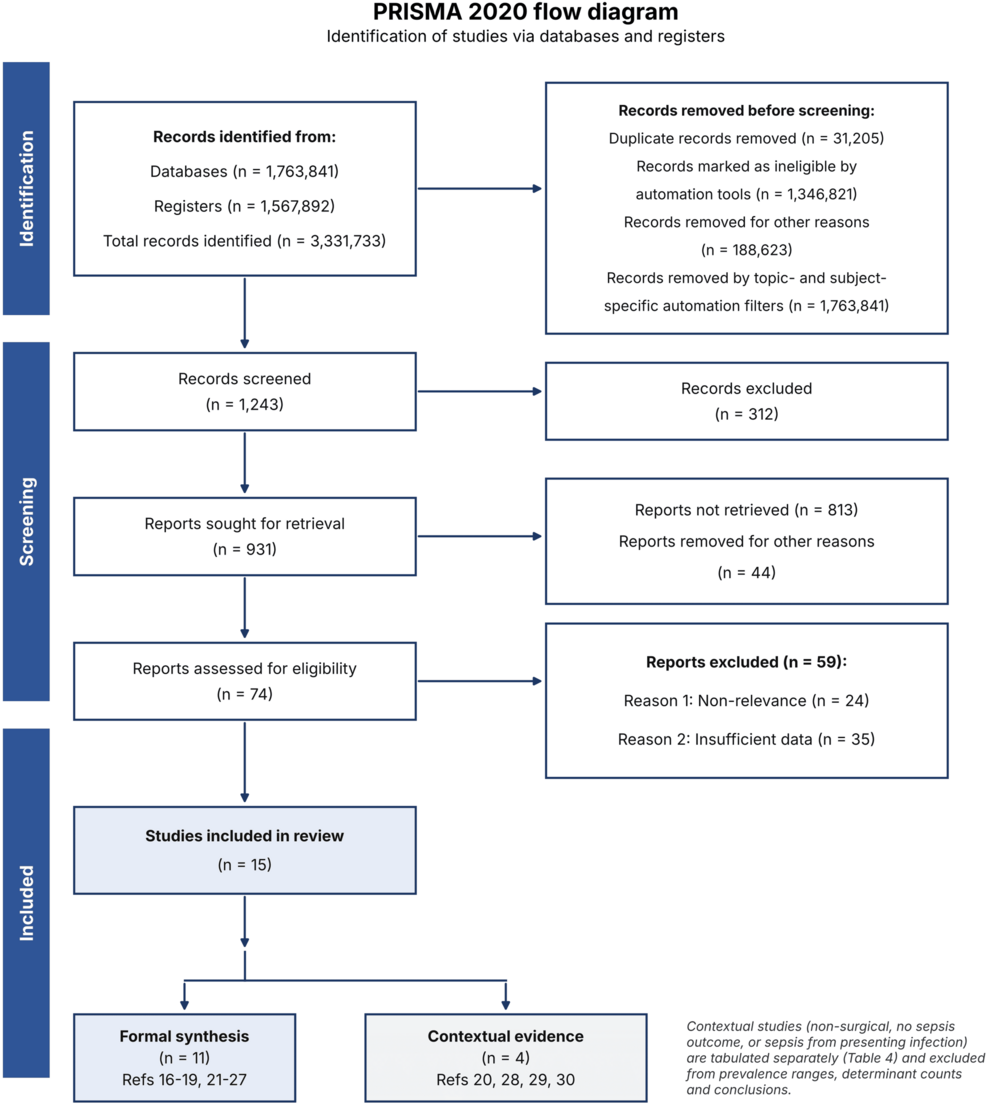
Sepsis remains a critical public health challenge following trauma and emergency surgery, with research indicating that patient outcomes are heavily influenced by surgical urgency and physiological vulnerability.
Global burden estimates from 2017 identified 48.9 million incident cases and 11.0 million deaths, a trend that updated analyses through 2021 confirm continues to impact patient survival, according to a systematic review.
Surgical Urgency Drives Higher Postoperative Sepsis Risk
Emergency surgical interventions frequently involve patients who are physiologically unprepared, often facing ongoing shock, hemorrhage, or significant wound contamination. Data reviewed identify surgical urgency as a consistent determinant for postoperative sepsis in trauma and surgical patient cohorts.
Patients undergoing emergency surgery often lack the time required for medical optimization, which distinguishes their risk profile from elective surgical populations. While elective procedures such as thyroidectomy show sepsis rates as low as 0.1%, trauma-associated sepsis cases have been recorded at rates ranging from 8% to 10.2%.
Determinants of Perioperative Infection
Clinical research highlights several recurring factors that heighten the risk of systemic infection after an operation. Beyond the urgency of the surgery, older age, elevated American Society of Anesthesiologists (ASA) physical status classifications, and the presence of diabetes are frequently cited as primary contributors to poor outcomes.
| Determinant | Observed Impact |
|---|---|
| Emergency Surgery | Higher risk of sepsis |
| Older Age | Higher risk of sepsis |
| Diabetes | Higher risk of sepsis |
| Mechanical Ventilation | Higher risk of sepsis |
Functional dependence and the use of mechanical ventilation also appear consistently across multiple studies as markers for increased vulnerability. Researchers said that these factors represent potential targets for preoperative screening and intervention to mitigate the risk of severe systemic infection.
Screening Tools and Local Resistance Data Guide Early Sepsis Management
Early recognition remains the cornerstone of sepsis management.
Clinicians are encouraged to use established scoring tools to quantify physiological reserve and to rely on local microbiological data to guide antibiotic therapy, as regional resistance patterns in surgical and nosocomial pathogens can complicate empirical treatment.
Common Questions About Surgical Sepsis
How does trauma-associated sepsis differ from postoperative sepsis?
Trauma-associated sepsis arises directly from injury, tissue damage, and post-injury immune dysregulation, whereas postoperative sepsis develops following an operative procedure during the same hospital admission. These scenarios require different surveillance approaches due to their distinct causes and opportunities for prevention.
Why is it difficult to compare sepsis rates between different studies?
The studies analyzed applied inconsistent definitions, including Sepsis-3 criteria, older SIRS-based metrics, and varied administrative coding frameworks. Because these methods are not directly comparable, prevalence estimates across different clinical populations cannot be accurately pooled.
What role does hospital volume play in patient outcomes?
Future research into this field is expected to prioritize prospective, multicenter cohorts that utilize standardized Sepsis-3 criteria and explicit injury-severity stratification. The systematic review identified that the evidence base for trauma patients specifically undergoing emergency surgery remains limited, with most current data extrapolated from broader surgical populations.
Related reading