Quantifying serum free light chains transformed plasma cell disorder diagnostics by replacing many urine studies with a sensitive serum assay. However, recent clinical literature shows that conventional reference intervals often misclassify non-clonal patients as abnormal due to kidney function, assay differences, and age-related changes.
Evaluating Kappa Lambda Ratios in Plasma Cell Disorders
Immunoglobulin light chains are synthesized by plasma cells in slight excess of heavy chains, and surplus proteins enter the circulation as free kappa and free lambda. Because these small proteins undergo almost exclusive glomerular filtration and proximal tubular reabsorption, serum concentrations reflect both plasma cell output and renal handling, according to foundational background data. The clinical utility of the assay relies heavily on the kappa/lambda ratio rather than absolute concentrations. Because a single clone produces only one light-chain isotype, a skewed ratio indicates clonality.
By current International Myeloma Working Group criteria, an abnormal ratio alone does not establish light-chain monoclonal gammopathy of undetermined significance (LC-MGUS). General MGUS cohorts must be distinguished from LC-MGUS populations. For instance, the Shenzhen screening study evaluated MGUS in a general health-check population and found that only 31.1 percent of confirmed cases exhibited an abnormal free light-chain ratio, demonstrating imperfect concordance in unselected populations.
Assessing Reference Interval Limitations Across Clinical Cohorts
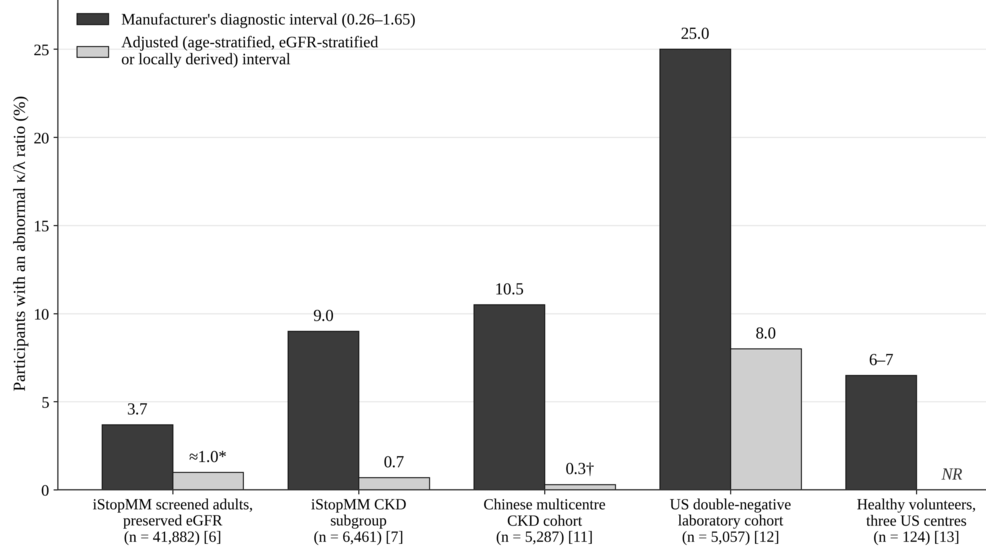
The widely used diagnostic range of 0.26 to 1.65 was derived from a modest cohort of healthy donors and fails to translate smoothly to older, frequently renally impaired, or inflamed clinical populations. Large population screening studies demonstrate that a substantial minority of non-clonal individuals fall outside this standard interval. Revised age-stratified intervals reclassify most of these individuals as normal without missing disease progression events. Kidney function shifts the ratio enough to reclassify approximately ten percent of a chronic kidney disease cohort.
Population screening programs, cross-sectional analyses, and cohort studies published between June 2016 and June 2026 highlight these discrepancies. In the Iceland Screens, Treats, or Prevents Multiple Myeloma (iStopMM) program evaluating 41,882 adults aged 40 and older with preserved kidney function, the free light chain ratio was abnormal in 3.7 percent of participants using standard intervals. Revised age-stratified 99 percent intervals reduced LC-MGUS prevalence from 1.54 percent to 0.27 percent—an 82 percent fall.
Renal function drives ratio variations in kidney disease patients
Renal function remains one of the strongest determinants of ratio variations. In the iStopMM chronic kidney disease subgroup of participants with an estimated glomerular filtration rate below 60 mL/min/1.73 m² and no monoclonality, the ratio fell outside the standard interval in 9.0 percent of cases, but outside the established renal interval of 0.37 to 3.10 in only 0.7 percent. A Chinese multicenter cohort of 5,287 non-dialysis chronic kidney disease patients similarly found a 10.5 percent abnormality rate using standard intervals, which dropped to 0.3 percent using renal intervals and 0.5 percent using iStopMM estimated glomerular filtration rate-banded intervals.
Assay platforms introduce additional variability. In 226 identical sera from patients with chronic kidney disease stages 2 through 5, the median ratio measured 1.50 using Freelite but 0.63 using Kloneus, demonstrating opposite directions of bias. The Freelite ratio correlates inversely with estimated glomerular filtration rate, whereas the N Latex ratio correlates positively, remaining within the healthy reference range across all stages of renal function. Head-to-head comparisons reveal that platform antisera, calibration methods, and analytical drift contribute significantly to whether an individual patient receives an abnormal result.
Clinical Insight: Orthogonal testing and updated age- or renal-adjusted reference intervals help prevent misclassification in patients with chronic kidney disease or systemic inflammation, protecting them from unnecessary bone marrow biopsies and clinical follow-up.
Screen-detected LC-MGUS cases often lack reproducibility on retesting
An abnormal ratio frequently lacks reproducibility. In the population-based Heinz Nixdorf Recall study, 17 of 31 screen-detected LC-MGUS cases with repeat samples—representing 55 percent of that subgroup—could not be confirmed on retesting.
Frequently Asked Questions About Serum Free Light Chain Testing
How do different laboratory assays affect test results?
Different manufacturers raise antisera against hidden epitopes and use non-commutable calibrators. For example, the Freelite ratio correlates inversely with estimated glomerular filtration rate, whereas the N Latex ratio correlates positively, meaning platforms are not directly interchangeable.
What percentage of healthy volunteers fall outside standard reference intervals?
Studies of rigorously screened healthy volunteers at multiple centers show that 6 to 7 percent fall above the standard diagnostic range of 0.26 to 1.65, demonstrating that manufacturer reference intervals cannot always be verified even in healthy populations.
Does an abnormal ratio always predict disease progression?
No. Population screening and longitudinal cohorts demonstrate that many abnormal ratios are transient or driven by renal and inflammatory factors, with 55 percent of repeat-tested screen-detected cases failing to confirm and showing no progression over extended follow-up.
Worth a look