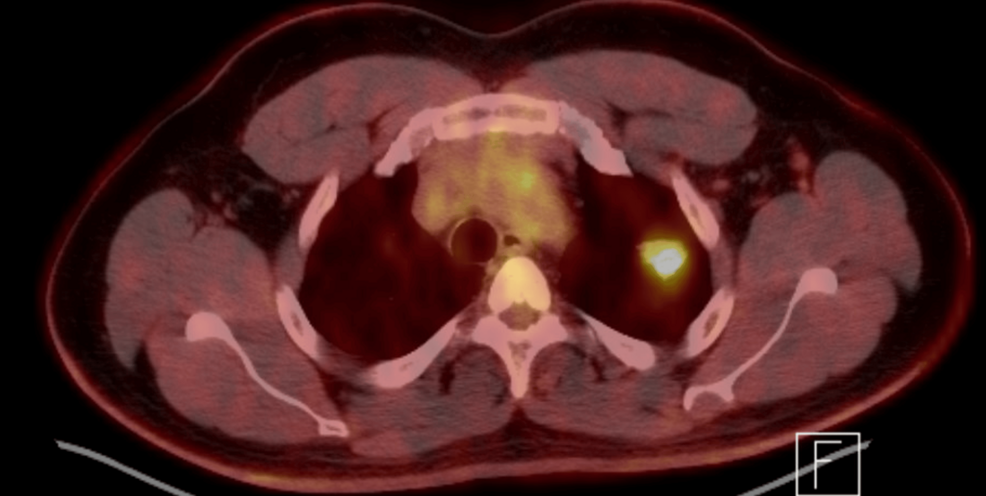
A 41-year-old African American male diagnosed with a histologically verified typical lung carcinoid (G1) presented with multi-station mediastinal lymph node metastasis, lymphovascular invasion, and direct phrenic nerve involvement, Cureus reported. The case challenges standard World Health Organization criteria that classify typical carcinoids as low-grade, indolent tumors with exceptionally high five-year survival rates and a low 5% to 20% rate of metastasis.
Discovery of the Left Upper Lobe Nodule
Initial diagnostic imaging included a gallbladder ultrasound and an abdominal-pelvis MRI, which incidentally revealed a lung nodule. A dedicated chest computed tomography scan subsequently identified a lobulated, pleura-based lesion measuring 2.4 by 2.7 centimeters in the left lung apex. The scan also revealed a 1.4-centimeter enlarged node in the left aortopulmonary window and subcentimeter bilateral mediastinal nodes.
A positron emission tomography scan demonstrated high metabolic activity within the left upper lobe nodule and the aortopulmonary window lymph nodes. The absence of additional hypermetabolic lesions confirmed the disease remained localized to the chest, pointing toward a clinical diagnosis of Stage IIIA carcinoma. To investigate further, clinicians planned a sequence of minimally invasive procedures, including fiberoptic and navigational bronchoscopy, bronchoalveolar lavage, and endobronchial ultrasound-guided transbronchial needle aspiration of the left hilar lymph node.
Surgeon removes lung tumor with clear margins
The patient underwent a robot-assisted video-assisted thoracoscopic surgery, which included biopsies of multiple mediastinal lymph node stations. Intraoperative findings showed markedly enlarged and bulky lymph nodes. Frozen section analysis confirmed neoplastic involvement, prompting the precautionary placement of a venous access port. Final pathology evaluated the primary resected tumor as a 3.8-centimeter typical carcinoid with negative surgical margins, establishing an R0 resection after a left upper lobe segmentectomy was performed to maximize lung preservation for the active weightlifter.
The final pathological staging was confirmed as pT2a N2 M0, representing Stage IIIA disease. Microscopic evaluation revealed multiple adverse prognostic factors, including lymphovascular invasion and significant metastatic involvement in ipsilateral mediastinal lymph node stations 5 and 6. Immunohistochemical and hematoxylin and eosin stains confirmed typical carcinoid features, including a low mitotic rate and the complete absence of necrosis.
Multidisciplinary Tumor Board Recommendations
Following definitive surgery, multidisciplinary tumor board discussions determined that adjuvant chemotherapy was not indicated. This decision aligns with National Comprehensive Cancer Network guidelines, which recommend against postoperative adjuvant cytotoxic therapy for resected bronchial neuroendocrine tumors, even in the presence of positive lymph nodes. The favorable G1 tumor biology confers inherent resistance to cytotoxic agents like capecitabine, temozolomide, and platinum-based regimens.
A follow-up chest CT scan at six months showed no active local or distant disease.
Scans track late recurrence in lung carcinoids
Did you know? While typical lung carcinoids account for roughly 90% of all lung carcinoids and boast five-year survival rates between 87% and 100%, aggressive subsets can present with multi-station N2 lymph node involvement typically seen in intermediate-grade atypical carcinoids.
Long-term management relies on rigorous surveillance to detect late recurrences, a well-documented phenomenon in bronchopulmonary neuroendocrine neoplasms. The primary surveillance tool remains the gallium-68 DOTATATE PET scan, which evaluates somatostatin receptor expression to identify early local recurrence or occult distant metastases.
Frequently Asked Questions About Aggressive Typical Carcinoids
Why did a low-grade typical carcinoid behave aggressively?
Although the tumor exhibited low mitotic rates and no necrosis—meeting G1 criteria—it demonstrated multi-station N2 lymph node metastasis, lymphovascular invasion, and phrenic nerve involvement.
What surgical approach was used for the patient?
Surgeons performed a robot-assisted video-assisted thoracoscopic surgery featuring a left upper lobe segmentectomy and additional nodal sampling. The procedure achieved a 1-centimeter resection margin, classified as an R0 resection, while preserving lung function for the patient.
Did the patient receive postoperative chemotherapy or radiation?
The multidisciplinary tumor board omitted adjuvant chemotherapy and radiation because typical carcinoids demonstrate resistance to cytotoxic drugs, aligning with international consensus guidelines for completely resected node-positive bronchial neuroendocrine tumors.