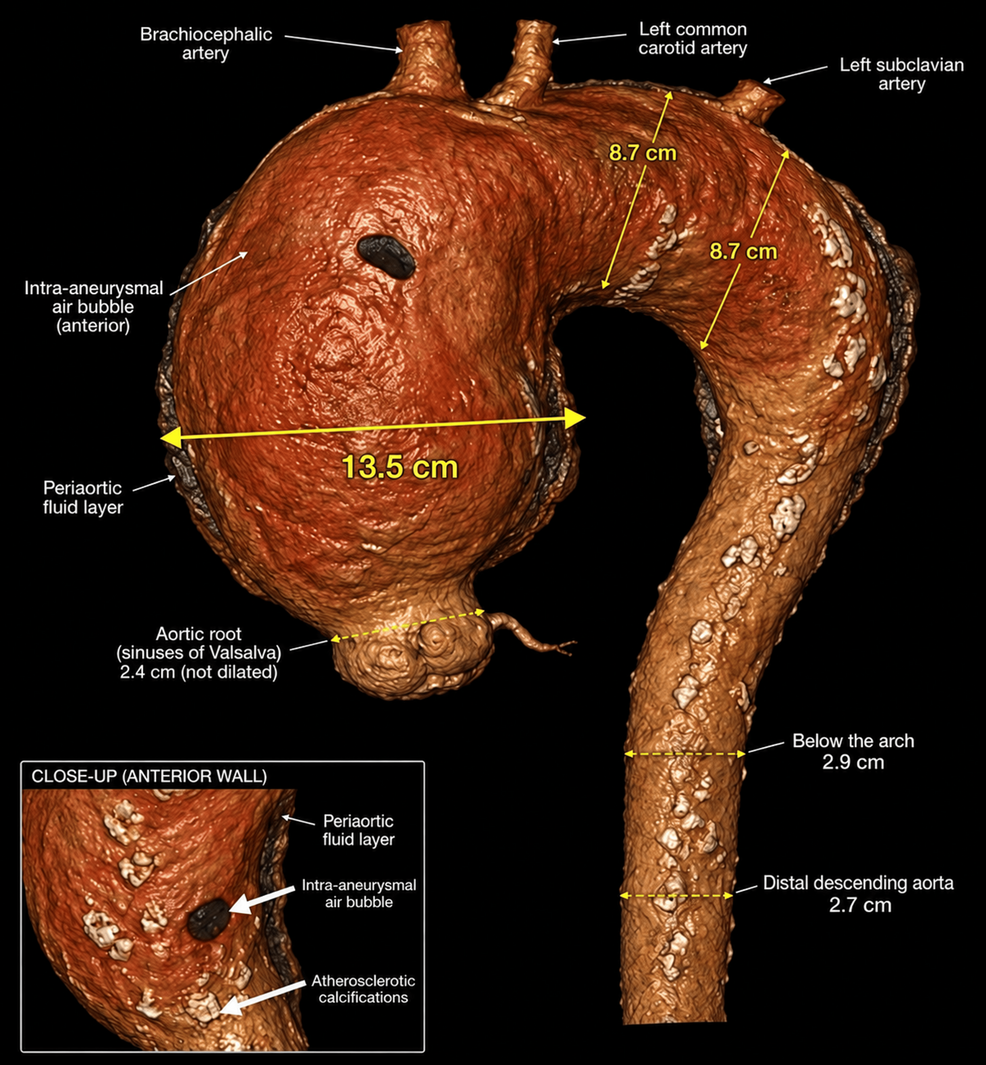
A 70-year-old woman presented with a 13.5-centimeter giant ascending aortic aneurysm, measuring nearly five times the normal female aortic diameter of 2.8 to 3.0 centimeters, cureus.com reported. The pathology, complicated by an 8.7-centimeter aortic arch aneurysm and signs of impending rupture, required emergency open surgical repair to replace the diseased vessels while preserving the native aortic valve.
Emergency Surgery for a 13.5-Centimeter Aneurysm
The patient arrived at the emergency department with severe dyspnea classified as New York Heart Association Class IV, generalized fatigue, anorexia, weight loss, and nocturnal diaphoresis. Her medical history included type 2 diabetes mellitus, a heavy smoking history exceeding 50 pack-years, hypothyroidism following a thyroidectomy, and anxiety with a depressive disorder. Initial laboratory testing showed an elevated C-reactive protein level of 231.3 milligrams per liter and a hemoglobin level of 10.5 grams per deciliter. Computed tomography angiography revealed the massive 13.5-centimeter ascending aortic aneurysm alongside periaortic fluid and an intra-aneurysmal air bubble, indicating a risk of fissuration.
Surgeons performed an emergency operation utilizing cardiopulmonary bypass established through left femoral arterial and venous cannulation. The patient was cooled to 18 degrees Celsius during median sternotomy. The surgical team executed a supracoronary ascending aortic and total arch replacement using a 32-millimeter woven polyester InterGard graft equipped with three pre-anastomosed 8-millimeter branches. The distal graft-to-descending-aorta anastomosis was completed under deep hypothermic circulatory arrest using 3-0 polypropylene sutures reinforced with Teflon felt. Selective antegrade cerebral perfusion supported the individual reconstruction of the left subclavian, left common carotid, and brachiocephalic arteries.
Atherosclerotic Etiology in an Unusual Location
Histopathological analysis confirmed that the aneurysm was of atheromatous origin with thrombotic degeneration, while microbiological studies ruled out infection. While atherosclerosis frequently impacts the descending thoracic and abdominal aorta, the ascending aorta typically resists isolated atherosclerotic degeneration due to distinct embryological and structural properties. International guidelines generally recommend surgical intervention for ascending aortic aneurysms at diameters of 5.5 centimeters or greater to prevent rupture, dissection, and death. Aneurysms exceeding 10 centimeters remain exceptionally rare in contemporary practice because modern imaging surveillance usually catches the pathology much earlier.
The operation yielded a cross-clamp time of 35 minutes, a total circulatory arrest time of 49 minutes, and a cardiopulmonary bypass time of 109 minutes. The patient experienced a favorable postoperative recovery without major complications or neurological deficits, allowing her to be discharged in stable condition six days after the procedure.
Questions About Rare Aortic Aneurysms
What caused the patient to seek emergency care?
The 70-year-old woman sought treatment after experiencing a one-week history of severe dyspnea, generalized fatigue, anorexia, weight loss, and nocturnal diaphoresis. Diagnostic imaging subsequently revealed the 13.5-centimeter ascending aortic aneurysm with features suggestive of impending rupture.
Why was this specific aneurysm considered exceptionally rare?
Aneurysms exceeding 10 centimeters are rarely seen today due to routine imaging surveillance, and the ascending aorta is naturally resistant to isolated atherosclerotic degeneration. In this case, the 13.5-centimeter diameter measured nearly five times the normal female ascending aortic size of 2.8 to 3.0 centimeters.
How did surgeons preserve the patient’s native aortic valve?
The surgical team performed a supracoronary ascending aortic replacement and total arch replacement that spared the aortic root and the native aortic valve. Cardioplegia was administered directly through the coronary ostia during the procedure.
Related reading