1 to 3 Percent of Bladder Cancers
Primary squamous cell carcinoma accounts for just 1 to 3 percent of urinary bladder malignancies in non-endemic regions, according to data published in Cureus. While urothelial carcinoma makes up the vast majority of cases, this rare variant typically presents at an advanced stage and carries an unfavorable prognosis. A 69-year-old male patient recently presented with long-standing irritative lower urinary tract symptoms, recurrent urinary tract infections, and intermittent hematuria, prompting a comprehensive diagnostic evaluation.
7.5 by 4.9 Centimeter Bladder Mass
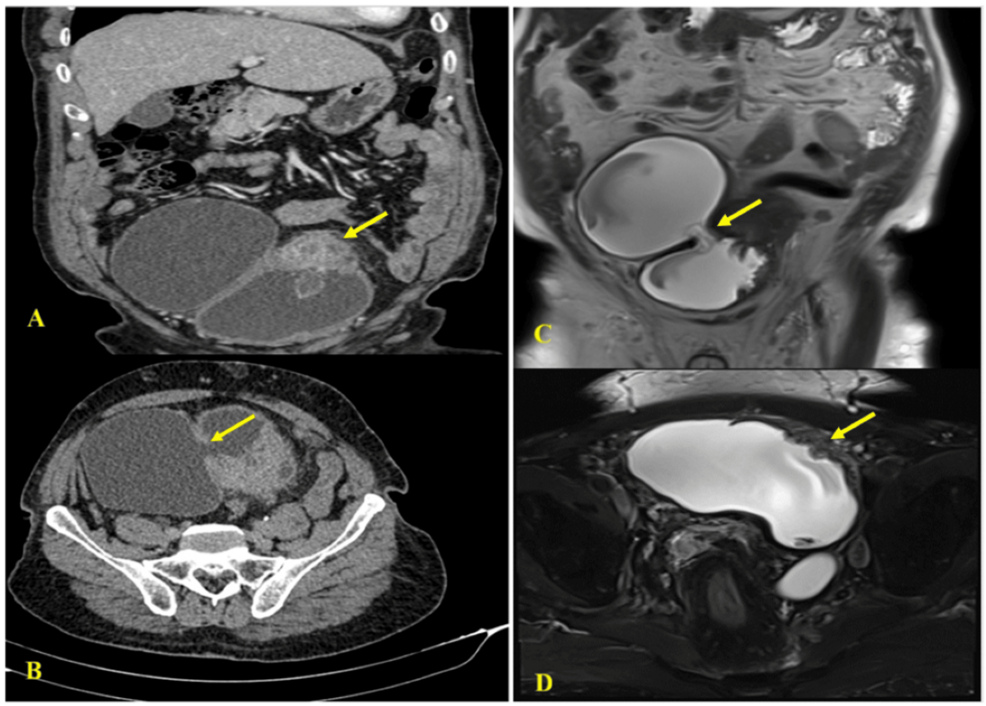
Contrast-enhanced computed tomography of the pelvis revealed an ill-defined, irregular, enhancing mass-like thickening measuring 7.5 by 4.9 centimeters on the superior aspect of the urinary bladder. The lesion extended to the left posterolateral wall. Imaging also showed a large cystic structure measuring 10.5 by 9.6 centimeters along the right lateral wall, communicating with the bladder lumen through a 14-millimeter defect consistent with a large bladder diverticulum. Magnetic resonance imaging later confirmed a lobulated infiltrative soft tissue lesion measuring 6.5 by 6.2 centimeters that involved the left vesicoureteral junction.
Moderately Differentiated Keratinizing Squamous Cell Carcinoma
Cystoscopic evaluation exposed a warty, exophytic mass measuring approximately 6 by 5 centimeters over the left posterolateral wall. Transurethral resection and subsequent biopsy samples revealed nests and sheets of malignant squamous cells featuring keratin pearl formation and intercellular bridges. Immunohistochemical analysis demonstrated focal positivity for p40 and p63, while standard urothelial markers including uroplakin, CK7, CK20, and GATA-3 tested negative. The Ki-67 proliferation index reached 40 to 45 percent, confirming a diagnosis of stage pT1N0M0 moderately differentiated keratinizing squamous cell carcinoma.
Four Cycles of Gemcitabine and Cisplatin
Following multidisciplinary tumor board review, the patient received systemic therapy prior to definitive surgery. He completed four cycles of combination chemotherapy using gemcitabine and cisplatin, administered across eight doses, alongside two cycles of pembrolizumab immunotherapy at 200 milligrams every three weeks. The patient then underwent radical cystectomy with pelvic lymph node dissection. Histopathological examination of the surgical specimen showed residual keratinizing squamous cell carcinoma with significant treatment response, clear surgical margins, and no metastatic involvement in the 17 dissected lymph nodes.
Frequently Asked Questions About Bladder Squamous Cell Carcinoma
What causes primary squamous cell carcinoma of the urinary bladder?
Non-bilharzial squamous cell carcinoma is typically linked to chronic urothelial irritation and inflammation. Contributing risk factors include recurrent urinary tract infections, bladder calculi, long-term catheterization, neurogenic bladder, and bladder diverticula.
How does squamous cell carcinoma differ from standard bladder cancer?
While urothelial carcinoma accounts for approximately 90 to 95 percent of bladder tumors, squamous cell carcinoma represents a rare non-urothelial subtype characterized by aggressive local behavior and advanced stage at presentation.
What is the standard surgical treatment for localized bladder squamous cell carcinoma?
Radical cystectomy with pelvic lymphadenectomy is widely considered the treatment of choice for localized disease. Partial cystectomy is generally avoided due to a high risk of local recurrence.