A patient recovering from dialysis-dependent kidney failure suddenly deteriorated — and the cause was not the kidneys.
The case, published in Cureus, describes a 49-year-old woman whose creatine kinase peaked at 87,696 U/L after an unwitnessed fall led to left thigh cellulitis. She developed anuric stage 3 acute kidney injury requiring intermittent hemodialysis. Heparin exposure then triggered heparin-induced thrombocytopenia with a platelet nadir of 11 × 10³/µL and thromboses in the left peroneal vein and bilateral internal jugular catheter sites.
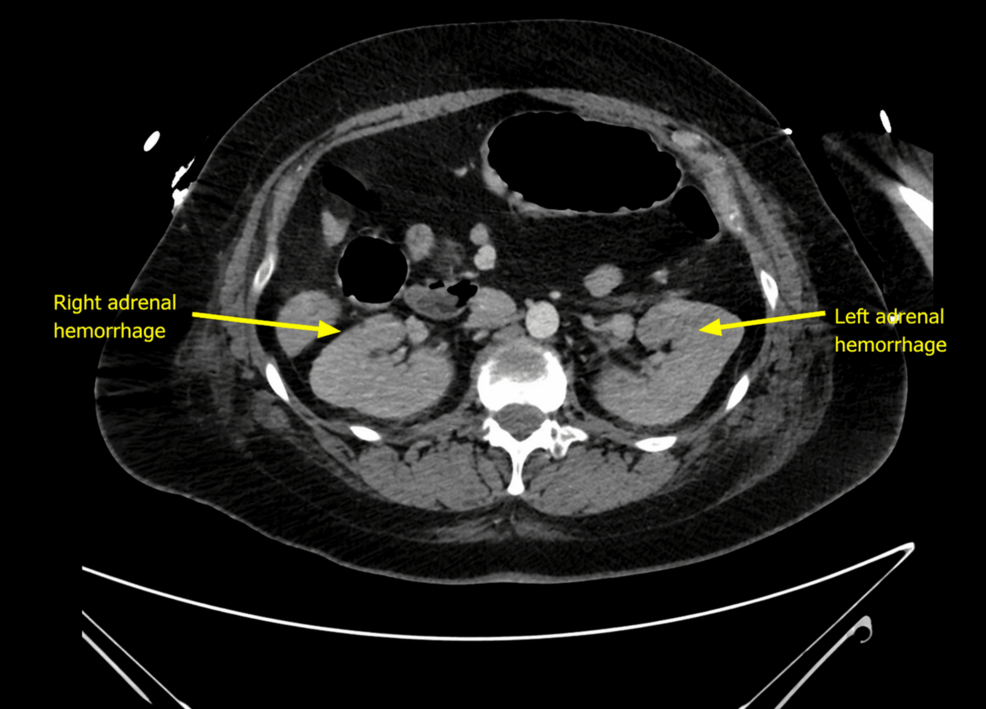
By hospital day 14, urine output had begun to improve. Five days later, she developed abdominal pain, nausea, relative hypotension, and falling urine output. Computed tomography revealed bilateral adrenal hematomas measuring approximately 4 cm on each side. A morning cortisol of 2.08 µg/dL rose only to 2.28 µg/dL after cosyntropin stimulation — far below the traditional 18 µg/dL threshold for adequacy.
Adrenal hemorrhage masquerades as stalled renal recovery
The clinical picture mimicked persistent acute tubular injury. “Increasing urine output complicated the assessment of kidney recovery,” the authors wrote. “Urine volume alone does not establish adequate solute clearance, and serum creatinine changes gradually after alterations in filtration under nonsteady-state conditions.”
Intermittent hemodialysis further obscured creatinine trends. The patient’s serum creatinine hovered near 5 mg/dL during the diuretic phase, yet urine output exceeded 3 L daily after hydrocortisone replacement began on day 21.
HIT creates a prothrombotic state despite thrombocytopenia
Heparin-induced thrombocytopenia generates thrombin through antibody-mediated platelet activation. The patient’s 4Ts score reached 6, indicating high probability. PF4/heparin antibody exceeded 16.0 U/mL (reference 0.0–0.9), and a functional heparin-induced platelet activation assay showed 63 percent activation (reference <20 percent).
Argatroban replaced heparin. The adrenal glands’ rich arterial supply and restricted venous drainage make them vulnerable to congestion and hemorrhagic infarction when venous outflow is impaired — a recognized though uncommon complication of HIT.
Cortisol deficiency impairs vascular tone and volume
Stress-dose hydrocortisone (50 mg IV every six hours) was followed by maintenance hydrocortisone 15 mg morning and 5 mg evening, plus fludrocortisone 0.05 mg daily. Blood pressure stabilized and urine output surged. The authors said that corticosteroid replacement can restore free-water excretion, meaning polyuria after treatment does not necessarily indicate improved glomerular filtration.
Plasma ACTH measured two days after hydrocortisone initiation was low at 5.2 pg/mL, but glucocorticoid suppression prevented distinction between primary and central adrenal insufficiency. Bilateral adrenal hemorrhage strongly favors primary insufficiency.
Dialysis independence achieved but baseline not restored
The final hemodialysis session occurred on hospital day 26. At discharge, serum creatinine was 1.71 mg/dL — substantially improved but still above the pre-admission baseline of 0.77 mg/dL. The patient continued apixaban, hydrocortisone, and fludrocortisone as an outpatient.
The report cannot determine whether adrenal insufficiency prolonged dialysis dependence. Recovery from severe acute tubular injury, improvement in systemic illness, and concurrent supportive treatment could also explain the trajectory.
What remains unanswered
Adrenal vein thrombosis was not demonstrated on imaging. HIT-associated hemorrhagic infarction remains a plausible but unconfirmed mechanism. Whether earlier recognition of adrenal hemorrhage would have shortened the dialysis course is unknown. The association between severe AKI and subsequent chronic kidney disease warrants continued follow-up.
| Hospital Day | Event | Creatinine (mg/dL) | Platelets (×10³/µL) | CK (U/L) |
|---|---|---|---|---|
| 19 | Abdominal pain; hypotension | 5.74 | 95 | 272 |
| 21 | Adrenal insufficiency confirmed; hydrocortisone started | ~5 | 110 | 183 |
| 26 | Final dialysis session | 3.92 | 136 | 123 |
| 31+ | Discharge | 1.71 | 186 | 91 |
Why this case matters for clinicians
New abdominal symptoms or unexplained hypotension during AKI recovery in a patient with HIT should prompt evaluation for bilateral adrenal hemorrhage. The temporal association between hydrocortisone initiation and hemodynamic improvement supported an adrenal contribution, but the effect on dialysis duration could not be established. Declining creatine kinase and rising urine output must be interpreted alongside metabolic stability, solute clearance, and ongoing dialysis requirements.
FAQ: Bilateral adrenal hemorrhage in HIT and AKI recovery
- How common is bilateral adrenal hemorrhage in heparin-induced thrombocytopenia?
- It is an uncommon but recognized complication. The adrenal glands’ restricted venous drainage makes them susceptible to hemorrhagic infarction when HIT causes adrenal vein thrombosis, though direct imaging evidence of thrombosis is often absent.
- What cortisol level confirms adrenal insufficiency after cosyntropin stimulation?
- The traditional threshold is a peak cortisol of approximately 18 µg/dL at 30 or 60 minutes after 250 µg IV cosyntropin. This patient’s cortisol rose from 2.08 to only 2.28 µg/dL, confirming an inadequate response.
- Can polyuria after hydrocortisone prove renal recovery?
- No. Cortisol deficiency impairs free-water excretion; replacement can cause a water diuresis without improved glomerular filtration. Sustained dialysis independence and declining creatinine are stronger evidence of renal recovery.
- Should anticoagulation be held if adrenal hemorrhage is found?
- In this case, anticoagulation was resumed after bleeding stability was established and later transitioned to apixaban. Balancing thrombosis risk against bleeding requires individualized judgment.
Did you know? The 4Ts score for HIT assigns points for Thrombocytopenia, Timing, Thrombosis, and oTher causes. A score of 6 or higher indicates high clinical probability — this patient reached that threshold once thrombotic events were included.
The case illustrates the diagnostic challenge of recognizing a reversible endocrine complication during recovery from severe kidney injury. Whether adrenal insufficiency prolonged dialysis dependence remains an open question.