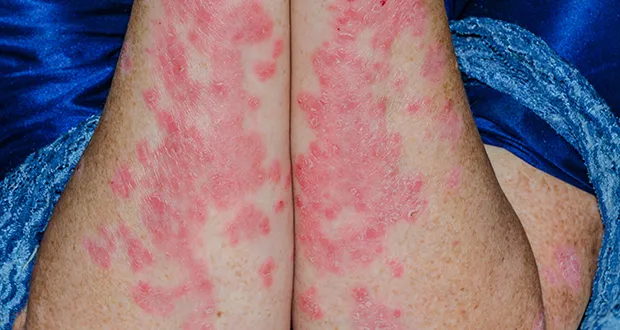
Plaque psoriasis affects roughly 2% of the population and carries substantial systemic burdens, including cardiovascular disease, psoriatic arthritis, metabolic syndrome, non-alcoholic fatty liver disease, and depression. Contemporary reviews and meta-analyses consistently link psoriasis to increased cardiovascular events, leading major medical societies to classify the skin condition as a cardiovascular risk enhancer that requires aggressive risk-factor management. Severity extends beyond simple body surface area measurements, with international guidance elevating special-area involvement and treatment history to trigger systemic therapy or dermatology referral.
Identifying Moderate to Severe Disease Beyond Body Surface Area
Clinicians evaluate disease severity through multiple validated metrics rather than relying solely on body surface area calculations. While a body surface area greater than 10% indicates moderate-to-severe disease, involvement of special areas such as the scalp, face, palms, soles, genitals, and nails warrants similar escalation. Marked quality of life impact, measured by a Dermatology Life Quality Index score of 10 or higher, also triggers therapy changes even when body surface area involvement falls below 10%. As reported, any plaques that are painful, itchy, recurrently infected, fissured, or function-limiting in manual or sexual tasks should be treated as moderate-to-severe regardless of surface area.
The Psoriasis Area and Severity Index remains the gold standard for clinical trials, but it is often cumbersome in primary care. Routine practice finds acceptable utility in combining body surface area, physician global assessment, and the Dermatology Life Quality Index.
Clinical Rule of Thumb: Function-limiting plaques on the hands or painful fissures in intertriginous zones meet thresholds for systemic intervention immediately, bypassing surface area percentage cutoffs.

Examining Familial Aggregation and Paternal Transmission Theories
Genetic heritability plays a major role in plaque psoriasis susceptibility across populations. A cross-sectional study of 640 consecutive, unrelated adult patients with chronic plaque psoriasis, published in Clinical and Experimental Dermatology (Vol. 39, No. 7, 2014, pp. 801–805) by V. Di Lernia, E. Ficarelli, A. Lallas, and C. Ricci, evaluated the degree of familial aggregation and recurrence risk ratios. The authors investigated whether the disease was preferentially transmitted from fathers, a hypothesis that previously circulated in dermatological literature.
Among the 640 patients evaluated in the study, a positive familial history of psoriasis appeared in 380 individuals, representing 59.37% of the cohort. Specifically, 174 patients, or 27.18%, had at least one parent with psoriasis, yielding a recurrence risk ratio of 13.59 under the assumption of a 2% population prevalence. Furthermore, 106 patients had at least one second-degree relative with psoriasis, while 34 patients reported an affected third-degree relative.
When analyzing transmission patterns, the researchers found no parent-of-origin effect in passing psoriasis from an affected parent to their offspring. Clinical profiles, including age of onset and the presence of facial, hand, or foot psoriasis, showed no statistically significant differences between patients grouped by paternal versus maternal transmission. These findings demonstrate a high familial recurrence risk alongside a balanced parental transmission model.
Screening for systemic comorbidities and cardiovascular risks
Primary care providers play an essential role in screening for systemic comorbidities linked to chronic plaque psoriasis. Because the condition acts as a cardiovascular risk enhancer, clinicians must measure blood pressure, lipid profiles, and glycated hemoglobin, while actively addressing smoking cessation and weight management. Depression and anxiety occur frequently and typically improve as skin clearance is achieved. Non-alcoholic fatty liver disease also shows higher prevalence in psoriasis patients, making baseline liver function tests, body mass index checks, and diabetes risk assessments vital before selecting systemic therapies like methotrexate or acitretin.
While awaiting specialist review, primary care management relies on optimized topical therapy. Potent corticosteroids combined with vitamin D analogues provide relief for chronic plaques, while short contact regimens assist with scalp involvement. Routine systemic corticosteroids are strictly avoided due to severe flare and rebound risks upon discontinuation. Dermatology referral becomes necessary when topical therapy fails, body surface area exceeds 10%, special areas or nail disease are involved, or rapid disease escalation occurs.
Achieving skin clearance with modern systemic treatments
Modern systemic treatments allow many patients to achieve near-clear or completely clear skin, measured as PASI90 to PASI100 response rates. Conventional non-biologic agents include methotrexate, which treats both skin and joint disease while requiring liver and blood count monitoring; ciclosporin, utilized for rapid short-term rescue; and acitretin, a keratinization modulator requiring strict contraceptive adherence due to prolonged teratogenicity. Specialist-delivered phototherapy with narrowband ultraviolet B or PUVA offers an effective, steroid-sparing alternative for extensive disease.
Targeted oral small molecules and biologics have transformed therapeutic outcomes. Biological therapies delivered via subcutaneous injection target specific immunological pathways:
- IL-23 Inhibitors (guselkumab, risankizumab, tildrakizumab): Deliver robust skin clearance and durable remission, with head-to-head trials showing risankizumab outperforming adalimumab.
- IL-17 Inhibitors (secukinumab, ixekizumab, bimekizumab): Provide rapid skin clearance, though candidiasis remains a recognized class effect requiring patient counseling.
- IL-12/23 Inhibitor (ustekinumab): Offers convenient dosing intervals and a long-standing safety record.
- TNF Inhibitors (adalimumab, infliximab, etanercept): Effective for both cutaneous and articular symptoms with extensive historical safety data.
Frequently Asked Questions
What is the recurrence risk ratio for first-degree relatives of psoriasis patients?
According to the 2014 study by V. Di Lernia and colleagues published in Clinical and Experimental Dermatology, the recurrence risk ratio for first-degree relatives is 13.59, based on a population prevalence estimate of 2%.
Does parental transmission favor the father or mother in plaque psoriasis?
Research published in Clinical and Experimental Dermatology indicates no parent-of-origin effect in the transmission of psoriasis, showing balanced parental transmission with no significant clinical differences in disease profiles between paternal and maternal inheritance patterns.
What screening tests are required before initiating biologic therapy?
Pre-treatment screening requires infection testing for tuberculosis via IGRA or TST, hepatitis B and C, and HIV, alongside general laboratory evaluations including complete blood counts, liver function tests, and renal function assessments.
Keep reading