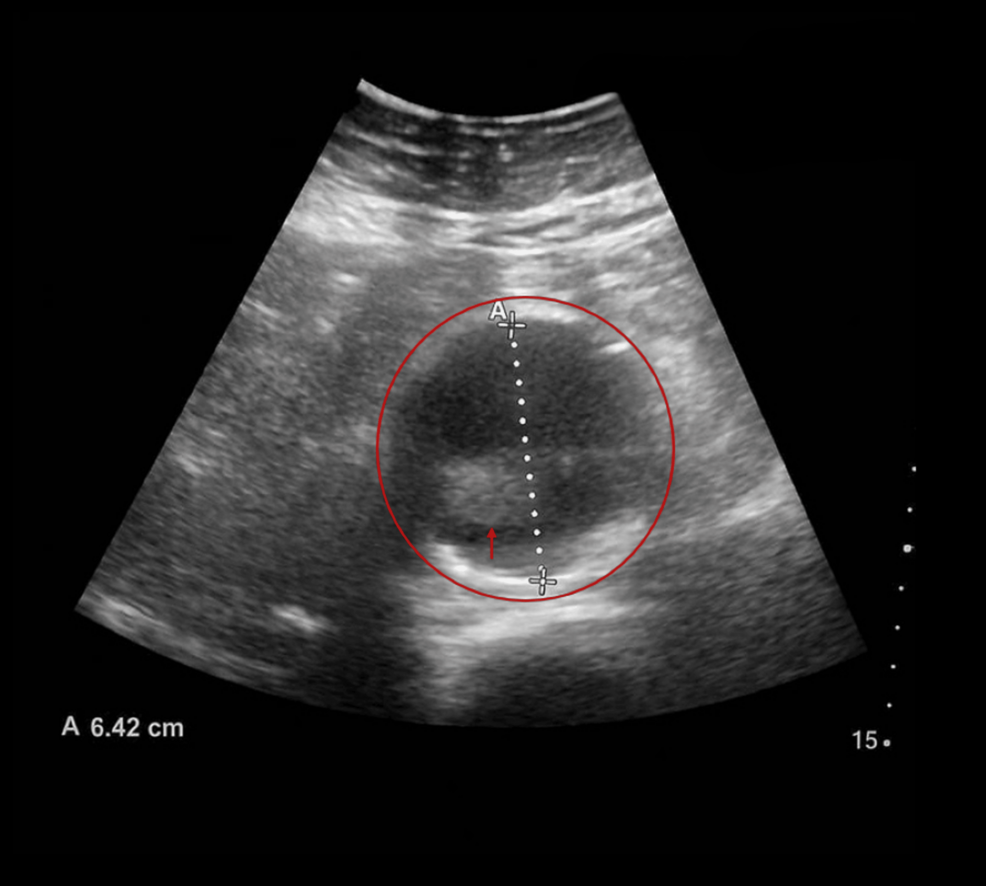
A 73-year-old man arriving with sudden leg weakness and calf pain was found to have a ruptured abdominal aortic aneurysm, a case report from Cureus shows.
The patient’s presentation lacked the classic symptoms of abdominal pain or hypotension, highlighting the diagnostic challenges of a condition that remains fatal in 80-90% of cases.
The patient, a heavy smoker with chronic obstructive pulmonary disease, sought emergency care after falling due to a sudden loss of strength in his right leg.
Physical exams showed manual muscle testing (MMT) grade 3/5 weakness in hip flexion and knee extension, along with localized calf hyperesthesia. Despite these neurological symptoms, the patient remained hemodynamically stable with normal blood pressure, a finding that can sometimes provide "false reassurance" to clinicians, according to Cureus.
While the patient did not report back or abdominal pain, a physical examination identified a prominent, pulsatile abdominal mass. Bedside point-of-care ultrasound (POCUS) quickly revealed an infrarenal abdominal aorta measuring 6.42 cm, confirming an aneurysm. An abdominal aortic aneurysm (AAA) is defined as a focal dilatation measuring at least 1.5 times the expected diameter, or ≥3.0 cm.
The patient’s laboratory results indicated a potential consumptive coagulopathy, characterized by a markedly elevated D-dimer, thrombocytopenia, and prolonged prothrombin time. While the hemoglobin remained normal, these findings prompted further imaging. Contrast-enhanced computed aortography confirmed the presence of an infrarenal AAA with a contained rupture.
The case highlights how atypical symptoms—such as isolated limb pain or weakness—can often lead to misdiagnosis. A study of 455 patients cited by Cureus found that those who were misdiagnosed faced a significantly higher mortality rate of 74.6%, compared to 62.9% for those correctly identified.
The patient was transferred to a tertiary center for urgent vascular surgery because the presenting hospital lacked specialized vascular services. The medical team said that the patient’s calf hyperesthesia and motor deficits likely resulted from the mass effect of the aneurysm on adjacent neural structures, such as the psoas muscle or the femoral nerve.
"Maintaining a high index of suspicion and performing a thorough vascular examination, including point-of-care ultrasound, may expedite diagnosis," the Cureus report stated. The use of POCUS in the emergency department has become increasingly vital, as it offers a sensitivity and specificity of approximately 98-99% for detecting aortic aneurysms.
Why is a ruptured AAA often misdiagnosed?
The classic triad of symptoms—abdominal pain, hypotension, and a pulsatile mass—is present in only 13% to 50% of cases. Many patients present with unrelated complaints like leg pain, renal colic, or bowel obstruction, which can lead clinicians to look for musculoskeletal or neurological causes instead.
Does hemodynamic stability rule out a rupture?
No, hemodynamic stability should not provide false reassurance. A patient can remain stable even while experiencing a contained rupture, as seen in this case where the aneurysm had already begun to compromise surrounding tissues.
What is the role of D-dimer in diagnosing this condition?
Many patients with an AAA have elevated D-dimer levels, reflecting fibrin turnover within the thrombus. While not a diagnostic test for AAA itself, its presence in a patient with unexplained leg pain may serve as an indicator for vascular pathology.
The precise mechanism linking the patient’s specific neural deficits to the localized mass effect of the aortic rupture remains a subject for further clinical investigation.
Worth a look