A 54-year-old man presented with left-sided flank pain during urination, spontaneous lower-extremity bruising, and gingival bleeding that initially pointed toward a common urinary tract infection rather than a hematologic emergency, Cureus reported.
The patient, who has a four-year history of Parkinson’s disease, was transferred from an outside hospital after developing symptoms one week prior. Urine dipstick testing showed positive nitrites and moderate blood, but a computed tomography scan revealed no nephrolithiasis, hydronephrosis, or intra-abdominal inflammation, according to Cureus.
A complete blood count ordered during the evaluation uncovered profound pancytopenia with a white blood cell count of 2.0 × 10³/µL, a hemoglobin level of 7.2 g/dL, and a platelet count of 7,000/µL. PMC.ncbi.nlm.nih.gov noted that acute promyelocytic leukemia accounts for 5 to 20 percent of adult acute myeloid leukemia cases, carrying an annual incidence of 1 to 7.4 cases per 1,000,000 person-years.
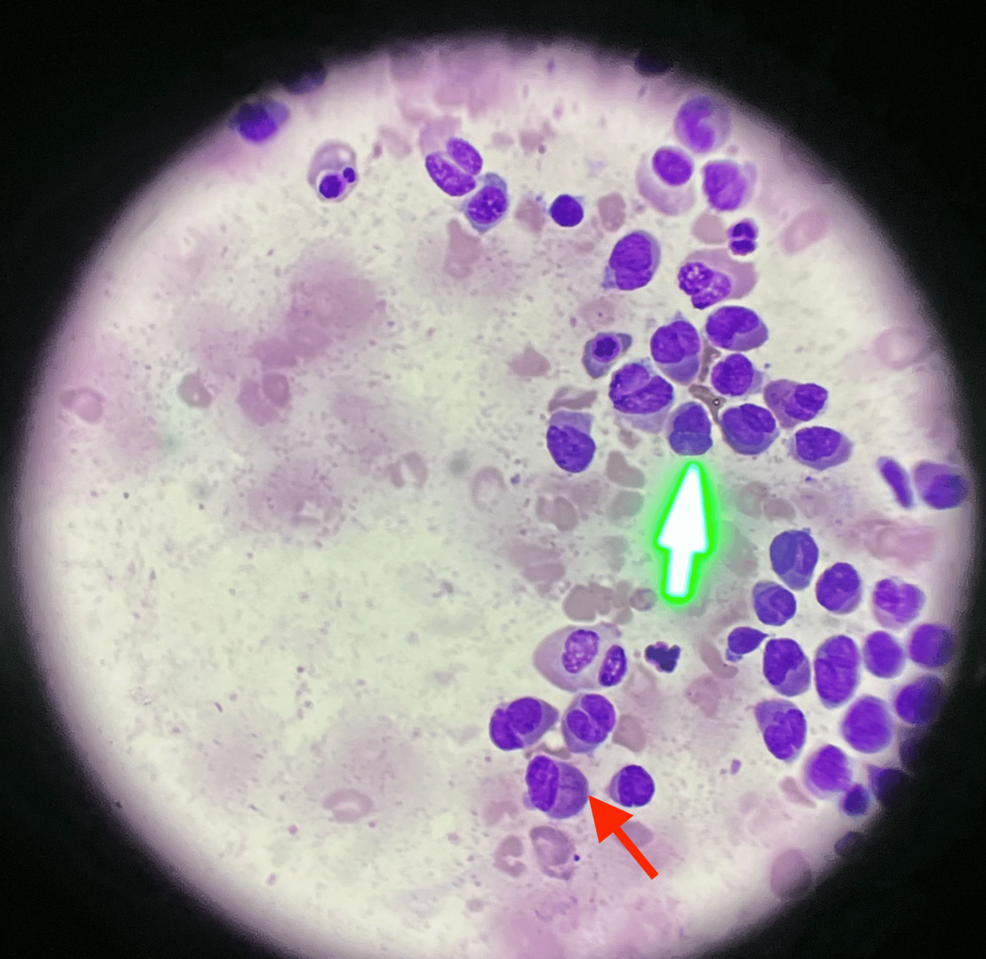
A peripheral blood smear displayed circulating blasts against a background of severe thrombocytopenia and normocytic anemia, prompting an urgent bone marrow examination, Cureus reported. The bone marrow aspirate and core biopsy showed greater than 95% cellularity with near-complete replacement by abnormal promyelocytes.
Fluorescence in situ hybridization subsequently confirmed the diagnosis by detecting the characteristic PML::RARA t(15;17) fusion gene, Cureus reported. PMC.ncbi.nlm.nih.gov stated that this reciprocal translocation between chromosome 15 and chromosome 17 disrupts retinoic acid receptor signaling, which blocks myeloid differentiation and drives leukemogenesis.
Coagulation tests at admission revealed a prothrombin time of 11.9 seconds, an international normalized ratio of 1.1, and an initial fibrinogen level of 528 mg/dL.
By hospital day six, supportive and leukemia-directed treatment produced an increase in hemoglobin to 9.3 g/dL and platelets to 37,000/µL, while the white blood cell count rose to 19.9 × 10³/µL and neutropenia persisted, Cureus reported. PMC.ncbi.nlm.nih.gov emphasized that disseminated intravascular coagulation remains the primary driver of early mortality in acute promyelocytic leukemia, making rapid diagnosis and immediate administration of all-trans retinoic acid critical.
Previous multicenter studies cited by Cureus reported early mortality rates ranging from 11 percent to 13.1 percent, with hemorrhage responsible for the majority of early deaths. Those studies identified delays in ordering all-trans retinoic acid beyond 24 hours from presentation as an independent risk factor for early mortality.
Did you know?
PMC.ncbi.nlm.nih.gov noted that while the classical t(15;17) translocation drives the vast majority of cases, rare variant rearrangements involving RARA such as PLZF::RARA can occur in approximately 1 percent of patients and exhibit different treatment responses.
The patient presented with dysuria-associated flank pain, costovertebral angle tenderness, and a nitrite-positive urinalysis that initially suggested a urinary tract infection or dehydration, Cureus reported.
A complete blood count revealed a white blood cell count of 2.0 × 10³/µL, a hemoglobin level of 7.2 g/dL, and a critical platelet count of 7,000/µL, according to Cureus.
The PML::RARA oncoprotein disrupts nuclear body function and retinoic acid signaling, leading to cellular differentiation arrest and apoptosis resistance, PMC.ncbi.nlm.nih.gov reported.
Induction therapy combining all-trans retinoic acid and arsenic trioxide was initiated on hospital day three following confirmation of the t(15;17) translocation, Cureus reported.