0.06 per Thousand Biopsies Versus Less Than 0.1 Percent Transjugular Risk
Bleeding remains the most clinically significant complication of percutaneous liver biopsy, yet hemobilia occurs in just 0.06 per thousand procedures, according to data cited by Cureus from a multicenter retrospective study of 68,276 percutaneous biopsies. While transjugular liver biopsy is generally considered to have a superior safety profile, hemobilia after that approach is exceedingly uncommon at an estimated incidence of less than 0.1 percent, as reported in separate findings on PMC.
A 55-year-old man with a history of chronic hepatitis B experienced acute symptomatic hemobilia roughly 10 minutes after an ultrasound-guided percutaneous liver biopsy of a 40 by 39 millimeter LI-RADS 4 hepatic lesion, Cureus reported. The patient developed sudden right upper quadrant pain and hematemesis while still in the procedure room. Pre-procedural lab work showed a hemoglobin level of 12.5 grams per deciliter, a platelet count of 280,000 per microliter, and prothrombin activity at 75 percent.
Ultrasound Reveals Echogenic Material Inside Gallbladder Following Biopsy Passes
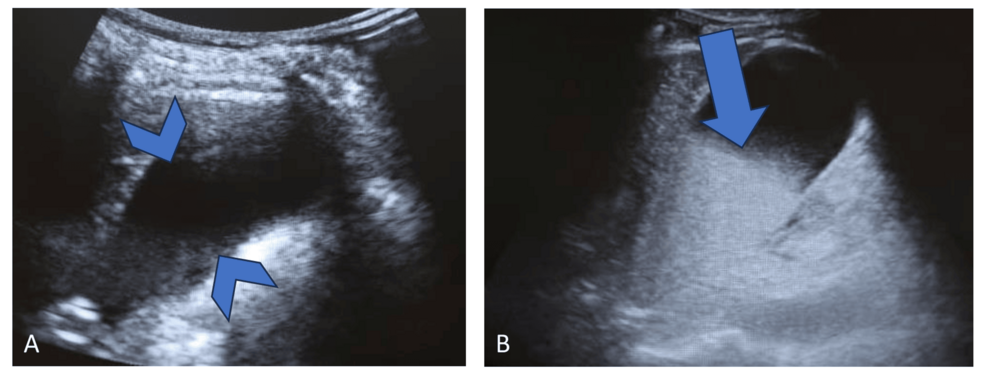
Bedside ultrasound revealed newly developed echogenic material occupying roughly half of the gallbladder lumen just 10 minutes after the biopsy needles were withdrawn. Planning scans immediately prior to the intervention had shown an anechoic, thin-walled gallbladder without sludge. Geotek manufactured the semi-automatic 16-gauge by 15-centimeter Tru-Cut core biopsy needle and 15-gauge by 10-centimeter coaxial introducer used for the three passes through an intercostal approach.
An emergency multiphasic contrast-enhanced computed tomography scan performed about 15 minutes after symptom onset showed hyperattenuating gallbladder contents measuring approximately 52 Hounsfield units. Unenhanced CT images also displayed small foci of gas along the biopsy tract and inside the lesion. Arterial and portal venous phases demonstrated no active contrast extravasation, pseudoaneurysm, or hemoperitoneum.
Contrast With Transjugular Presentations and Pancreatitis Complications
While percutaneous hemobilia typically presents with upper gastrointestinal bleeding and abdominal pain within a mean interval of five days, transjugular liver biopsy complications can manifest quite differently. A PMC report detailed a 49-year-old male with a complex medical history—including asthma, type II diabetes, hypertension, and atrial fibrillation on apixaban—who developed acute pancreatitis and obstructive jaundice following a transjugular biopsy without overt gastrointestinal bleeding.
The patient in the PMC case report had positive anti-smooth muscle antibodies at 1:40 and elevated liver enzymes, including an AST of 71 units per liter and ALT of 124 units per liter. Endoscopic retrograde cholangiopancreatography served as both the diagnostic tool and the treatment, resolving the biliary obstruction. By contrast, the percutaneous patient managed by Cureus investigators experienced neither jaundice nor pancreatic inflammation.
Conservative Management Versus Endoscopic Interventions
Medical teams chose conservative management for the 55-year-old percutaneous biopsy patient because he remained hemodynamically stable without ongoing hemorrhage. His six-hour post-procedure hemoglobin measured 12.3 grams per deciliter and stayed stable the following day. He required no blood transfusions, endoscopic procedures, or angiographic embolization, and left the hospital after three days of observation.
Conversely, the transjugular patient documented on PMC required endoscopic retrograde cholangiopancreatography to achieve complete clinical and biochemical recovery from biliary obstruction. Most hemobilia cases are self-limited, but severe bleeding episodes require transcatheter angiographic embolization or surgical intervention.
Clinical Questions About Post-Biopsy Hemobilia
How soon after a liver biopsy can hemobilia occur?
While symptoms typically appear hours to days later with a mean interval of five days, hyperacute presentations can happen within 10 minutes of the procedure, as documented in Cureus.
Do patients always present with the classical Quincke triad?
No, all three manifestations of the Quincke triad—gastrointestinal bleeding, right upper quadrant pain, and jaundice—occur together in only a minority of patients. The percutaneous patient reported by Cureus presented with pain and hematemesis without jaundice, while the transjugular patient on PMC presented with pancreatitis and jaundice without overt gastrointestinal bleeding.
What imaging modalities confirm intracholecystic blood products?
Bedside ultrasound reveals newly developed echogenic material in the gallbladder, while emergency multiphasic computed tomography demonstrates hyperattenuating blood products measuring approximately 52 Hounsfield units without necessarily identifying an active vascular communication.
When is conservative observation chosen over embolization?
Physicians select conservative management when the patient remains hemodynamically stable, serial hemoglobin levels remain steady, and imaging shows no active contrast extravasation or pseudoaneurysm.
Related reading