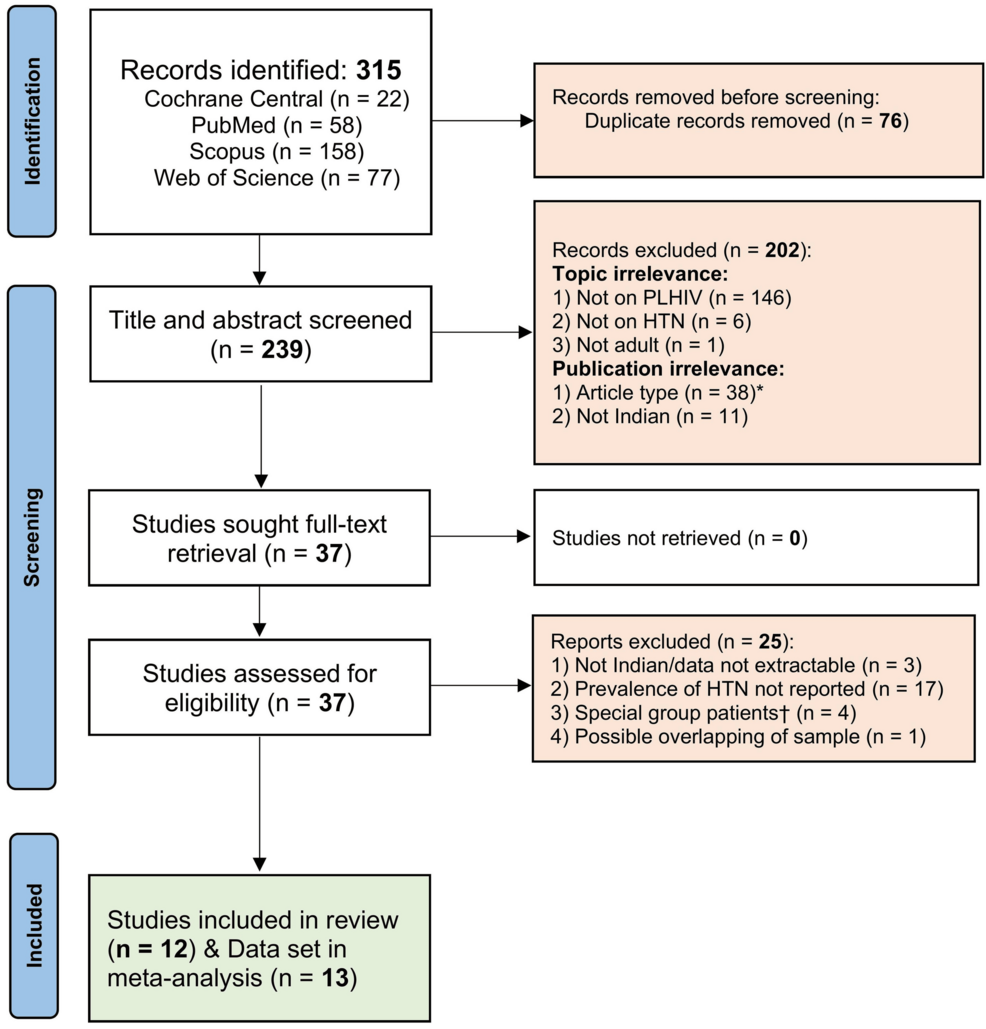
India’s HIV population faces a hypertension burden of 19.37%, Cureus reported, a figure that sits below the national average but masks wide swings between clinics and regions.
The pooled estimate comes from 12 studies covering 39,809 adults on antiretroviral therapy across seven states. Heterogeneity was extreme: I² reached 93.9%, and a prediction interval means the next comparable study could land almost anywhere in that range.
“The coexistence of HIV and hypertension poses additional challenges for clinical management,” the authors wrote, “as it increases the risk of cardiovascular complications and may complicate treatment strategies due to potential drug interactions and adherence issues.”
Diagnostic thresholds drive the spread
Six studies used the standard ≥140/90 mmHg cut-off and yielded a pooled prevalence of 19.0%. Two relied on self-reported history and found just 5.4%. One used a lower 130/85 mmHg threshold. Three did not state a criterion at all and produced the highest pooled estimate, 51.7%.
The difference between subgroups was statistically significant, though the authors cautioned that several subgroups contained only one or two studies.
Two outliers, opposite directions
A 2017 chart review from Karnataka (Madi et al.) reported 77.5% prevalence in 120 elderly patients newly started on ART. A 2017 cross-sectional study from Odisha (Pati et al.) found 2.5% in 197 patients, most with advanced immunodeficiency.
A Baujat plot confirmed Madi et al. as the single largest contributor to both heterogeneity and the pooled effect size. Pati et al. pulled the estimate down while adding moderate heterogeneity. The massive 2025 multicentre study by Acharya et al. anchored the statistical weight but shifted the pooled prevalence minimally.
India's 19.4% prevalence falls between global and regional averages
A 2024 global meta-analysis placed the worldwide pooled prevalence at 25.2%. South Africa reported 21.9%. The Asia-Pacific region averaged 16.5%. India’s 19.4% sits between the regional and global figures.
The authors stressed that direct comparisons are hazardous: age structures, sampling frames, and blood-pressure protocols differ across every estimate.
Mechanisms: virus, drugs, or both
Chronic immune activation, endothelial dysfunction, and ART-driven metabolic changes — especially from protease inhibitors — all push blood pressure up. The review’s pathway diagram (Figure 6) traces HIV inflammation through IL-6 and RAAS activation to arterial stiffening, while ART adds insulin resistance and central obesity.
Evidence gaps the next study must fill
No nationally representative, community-based survey exists. EMBASE was not searched. Grey literature was excluded. Facility-based designs dominate, introducing selection bias toward sicker, older, or more adherent patients.
The trim-and-fill method imputed four missing small studies and raised the adjusted prevalence to 25.5% (95% CI 16.4–37.4%), suggesting publication bias cannot be ruled out despite non-significant Egger (p=0.49) and Begg (p=0.09) tests.
India, the world’s most populous nation with approximately 1.464 billion people in 2025, spans South Asia as the seventh-largest country by area. Its modern borders emerged from the 1947 partition of British India, and the 1950 Constitution established a federal democratic republic. Economic reforms in the 1990s integrated the country into the global economy, driving sustained growth by the 2010s alongside a rising middle class.
What clinicians can use today
Routine BP screening at every ART visit, standardized to ≥140/90 mmHg on two occasions, would make future data comparable.
How was the 19.37% figure calculated?
A random-effects meta-analysis of proportions with logit transformation pooled 13 data sets from 12 Indian studies published between 2011 and 2025, encompassing 39,809 adults living with HIV.
Why does the prediction interval span 2.4% to 70.2%?
Extreme between-study heterogeneity (I² = 93.9%) driven by different diagnostic thresholds, age profiles, ART durations, and clinic types means the true prevalence in a new, similar setting could fall anywhere in that range.
Is hypertension actually lower in people with HIV than in the general Indian population?
The review’s indirect comparison suggests 19.4% versus the national average, but the authors warn that age distribution, sampling methods, and diagnostic criteria differ too much to conclude a genuinely lower burden.
Which study carried the most weight?
Acharya et al. (2025) contributed the vast majority of participants, yet its prevalence barely moved the pooled estimate because the random-effects model down-weights large studies when heterogeneity is high.
What should the next Indian study measure?
Community-based sampling, standardized ≥140/90 mmHg protocol with three readings, age-stratified reporting, and linkage to ART regimen and CD4 count would allow meaningful subgroup analysis and national generalization.
Keep reading
- SAG-AFTRA Forms Task Force to Advocate for Universal Healthcare
- Kayode Akintola Writes Ebola Response in DR Congo Repeats West Africa Failures
- Disney Developing ‘Home Alone’ Sequel With Macaulay Culkin, Reports Say (archyde.com)
- Per Fly to Set ‘Peer Gynt’ in Arms-Dealing World for Nordic Co-Production, VG Reports (archynewsy.com)